support@macsclinic.com
+91 9482202240
Breast Cancer Awareness Month 2026: A Guide to Screening, Symptoms and Prevention

Breast Cancer Awareness Month 2026: A Guide to Screening, Symptoms and Prevention

The presence of a lump, change in the breast contour or nipple discharge could prompt questions not so easy to dismiss. The knowledge of what to look for can help take a significant step forward concerning breast health. Not all changes in the breasts mean a problem, still, learning more about unusual symptoms may help women to make an informed decision on their condition.

Breast Cancer Awareness Month 2026 takes place in October to bring attention to preventing and detecting breast cancer, treatment, and screenings. Moreover, this is an excellent opportunity to dispel any myths about breast cancer and encourage women to undergo regular health check-ups.

Dr. Sandeep Nayak, a world-renowned surgical oncologist in India, stresses the importance of recognizing changes in the breast and consulting a doctor regarding them. The earlier breast cancer is detected, the more opportunities patients have to start treatment and improve outcomes – making awareness an important part of breast cancer care.

Banner promoting Breast Cancer Awareness Month 2026 with a pink ribbon and a woman in pink top.

In this guide, we’ll discuss the purpose of Breast Cancer Awareness Month, signs to recognize, risk factors, screenings, prevention strategies, and necessary steps for those having breast lumps.

What Is Breast Cancer Awareness Month 2026?

The Breast Cancer Awareness Month is observed all over the world in the month of October. The campaign highlights the impact of breast cancer on individuals and their families, as well as promotes education, screening, research and access to appropriate treatment.

It aims at:

* Promoting early detection: Educating women on how to identify changes in their breasts.

* Improving screening awareness: Helping people understand when mammography or other investigations may be appropriate.

* Correcting misconceptions: Addressing myths that may prevent people from seeking care.

* Helping patients: Educating people on the problems faced by breast cancer patients.

Breast cancer affects women across different age groups, although the risk generally increases with age. Awareness is valuable throughout the year, not only during October.

Which breast changes deserve attention? Let’s identify the warning signs that should be medically evaluated.

What Are the Early Signs and Symptoms of Breast Cancer?

Breast cancer does not always cause pain or an obvious lump. Some changes may be subtle, making familiarity with your usual breast appearance and feel particularly helpful.

Look out for:

Infographic showing six breast cancer signs: new lump, shape changes, skin changes, nipple changes, persistent discomfort, and swelling near the collarbone with a pink ribbon motif.

“These symptoms can have non-cancerous causes, too. However, persistent or unusual changes should be assessed rather than dismissed,” advises Dr. Sandeep Nayak, a leading oncologist in Bangalore.

Have you noticed an unusual breast change? Connect with a qualified breast specialist for timely evaluation and guidance on the appropriate next steps.

Does everyone have the same level of risk? Let’s look at the factors that may increase the likelihood of developing breast cancer.

Who Is at Higher Risk of Breast Cancer?

Several factors influence breast cancer risk. The presence of a risk factor does not always result in breast cancer. Even patients who do not have any known risk factors are likely to develop this disease.

Some important things are as follows:

Infographic banner urging breast cancer awareness with a pink ribbon and six risk-factor cards: Age, Family history, Inherited genetic changes, Personal medical history, Hormonal factors, Lifestyle factors.

A person with a family history or inherited risk of breast cancer can get individualised screening. Consult a doctor for that purpose.

Does finding a lump automatically mean cancer? Let’s walk through the steps doctors use to investigate a breast lump.

What Happens If a Breast Lump Is Found?

Discovering a lump can be worrying, but many breast lumps are benign. The important step is to establish the cause through appropriate medical assessment.

A typical evaluation may involve:

Infographic for Breast Cancer Awareness Month 2026 with a central pink ribbon and six pink circular icons for Raise Awareness, Encourage Screening, Support Patients, and Advance Care.

Not every lump requires a biopsy, but imaging alone may not always provide a definitive diagnosis. The recommended investigations depend on the findings.

Uncertainty about a breast lump can be stressful. Get in touch with an experienced specialist to understand the findings and appropriate investigations.

Can everyday choices help lower breast cancer risk? Let’s explore practical steps that support long-term breast health.

Ways to Reduce Your Risk of Breast Cancer

Not every form of breast cancer can be prevented through one strategy. However, there are certain ways that you can employ to reduce the risk of developing this type of cancer.

Infographic titled Healthy Habits for a Stronger You with six tip cards: stay active, maintain weight, limit alcohol, understand family history, follow screening, report changes.

Although breast self-awareness is useful, it cannot replace screening. There are some forms of breast cancer that mammograms may help to detect even before any symptoms arise, while ultrasound and MRI may be advised in particular circumstances.

Are common beliefs about breast cancer always accurate? Let’s separate misconceptions from established medical facts.

Common Breast Cancer Myths and Facts

Myth: Every breast lump is cancer.

Fact: Many breast lumps are benign, but any new or unusual lump should be evaluated.

Myth: Breast cancer only affects older women.

Fact: Risk increases with age, but younger women can also develop breast cancer.

Myth: No family history means no breast cancer risk.

Fact: Breast cancer can occur even without a known family history.

Understanding these facts can help people seek appropriate care without unnecessary fear or false reassurance.

How Can You Support Breast Cancer Awareness Month 2026?

Breast cancer awareness becomes more impactful when information leads to action. This can be done through:

Group of diverse women with pink ribbons embracing, promoting breast cancer awareness and solidarity.

Do not spread misleading information on prevention, screening, or treatments. Reliable information makes healthier health care decisions possible.

Conclusion

Breast Cancer Awareness Month 2026 is a wake-up call to be vigilant about breast health, to be aware of any abnormal developments, and to know one’s risks. While most breast problems are harmless, it is advisable to have an evaluation done to find out if there is a need for treatment.

Dr. Sandeep Nayak is a specialist in cancer treatment who pays attention to proper diagnosis and personalized treatment plans. Patients interested in breast cancer treatment in Bangalore may turn to a professional to get an idea about the appropriate diagnosis and treatment methods.

Frequently Asked Questions

1. When is Breast Cancer Awareness Month 2026?

Breast Cancer Awareness Month is observed throughout October 2026.

2. What is the objective of Breast Cancer Awareness Month?

Raising awareness about breast cancer symptoms, testing, risk factors, treatments, as well as providing assistance to people with such conditions.

3. What are the earliest symptoms of breast cancer?

It may include the presence of a new lump, nipple changes, skin changes, secretion from nipple or changes in breast shape.

4. Can breast cancer occur without a lump?

Yes. There are cases when breast cancer involves only the presence of skin changes, nipple changes or imaging changes without any palpable mass.

5. When should one start the screening for breast cancer?

The timing depends on country of residence and personal circumstances; therefore, consult your doctor to clarify when should one undergo screening procedures.

6. Can younger woman suffer from breast cancer?

Yes. Breast cancer affects mostly older populations but it may appear among women at any adult age.

7. Can men have breast cancer?

Yes. While it is less common among men than women, breast cancer affects men too.

Reference

Disclaimer: The information shared in this content is for educational purposes and not for promotional use.
What Is the Difference Between Oncology and Surgery?

What Is the Difference Between Oncology and Surgery?

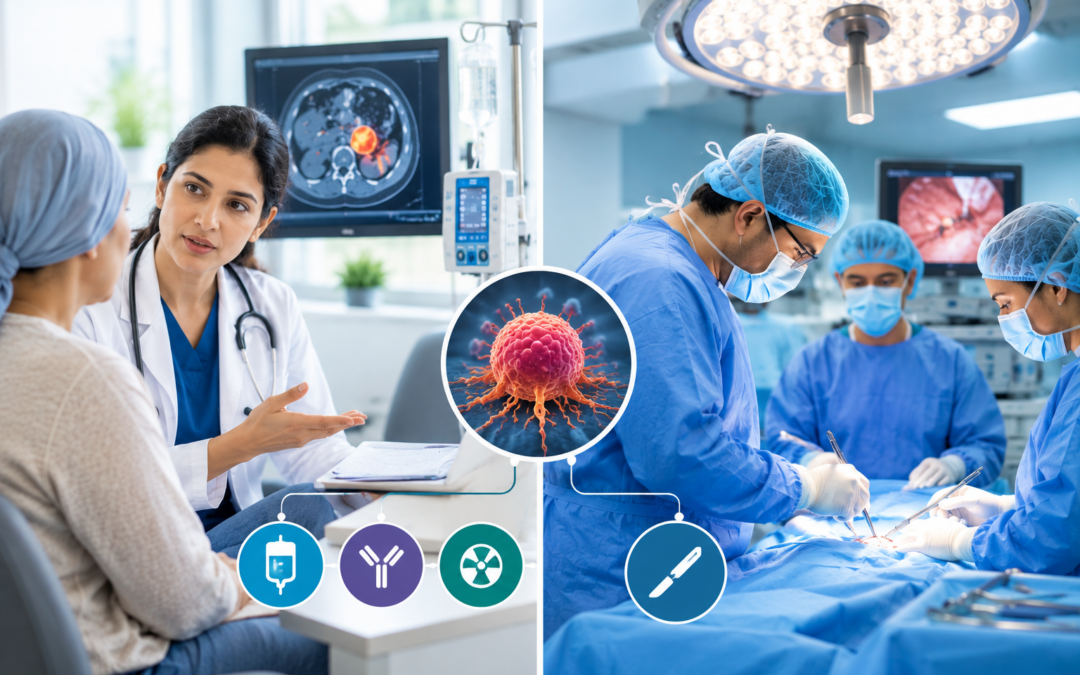
Ask a newly diagnosed patient what is troubling them and one question comes up early: oncology vs surgery, which one do I need? It is a fair question, but it is not a contest. Oncology is the whole subject of cancer care. Surgery is one of the things it uses. What separates them is reach: drugs go round in the blood and find cancer cells wherever they are hiding, while surgery works on one spot, the solid tumour and a little healthy tissue around it. The surgical oncologist sits where the two meet, and that is why oncology and surgical oncology get talked about together.

According to Dr. Sandeep Nayak, a surgical oncologist in Bangalore, nobody is really asked to pick between the two. Many solid tumours need both at some point. What changes from case to case is the sequence, and the cancer type, the stage and the patient’s fitness for surgery decide it.

Have a biopsy report or a scan and unsure what the next step is? You may contact  Clinic on +91 9482202240.

Oncology vs Surgery: The Core Difference

Oncology is the field. Surgery is one tool inside it. At a cancer centre they sit side by side in one team of oncologists.

  • Oncology: All of cancer care, from the first scan to the last follow-up visit. It has three main arms: medical, radiation and surgical.
  • Medical oncology: The drug arm. Chemotherapy, targeted tablets, immunotherapy and hormone treatment go round in the blood, so they reach the main tumour, the lymph nodes and any organ it may have spread to, in one go.
  • Surgery: The operating arm. The surgeon takes the tumour out from where it started, with a rim of normal tissue and the lymph nodes next to it.
  • Radiation oncology: Beams of radiation aimed at one area. Local, like surgery, but with no incision.
  • Why both exist: A drug can reach cells that scans can’t see, but it can’t take out a solid lump. Surgery gets the lump out, but a cell that has already moved on is beyond its reach.

Oncology and Surgical Oncology: Where They Meet?

A surgical oncologist is a surgeon who looks at cancer cases day in and day out. The job is bigger than the operation, and surgical oncology takes in the steps before and after it too.

  • Biopsy: First, a piece of the tumour has to be taken out and looked at under a microscope. Quite often the surgeon does this, with a needle, an endoscope or a small cut.
  • Staging: Once the scans and biopsy are in, the cancer gets a stage. The TNM system looks at three things: how big the tumour is, whether the nodes are involved, and whether it has spread. Every later decision leans on this.
  • The operation: The surgeon wants a clear margin, which means healthy tissue all round the tumour, and the nearby lymph nodes out as well. Leaving cancer behind weakens the benefit of everything that follows.
  • Function: Where it can be done, speech, swallowing and bowel or bladder function are kept safe, and what had to be removed is rebuilt.
  • Relief of symptoms: Sometimes the cancer can’t be removed fully. An operation can still open a blocked bowel or stop a bleed, and the patient feels better for it.

How the Two Work Together in Your Treatment Plan?

So which comes first? There’s no single answer, and the pages under cancer treatment services show how differently each cancer is handled.

  • Staging first: Many illnesses are staged before anyone picks a treatment; the stages of heart failure are a good example from cardiology. Cancer works the same way. The stage decides how much the surgeon will do and how much is left to drugs.
  • Surgery first: Take early colon cancer. The tumour is removed first. Then the pathology report is read. If the nodes show spread, or the tumour looks high-risk, chemotherapy is added.
  • Drugs before surgery: Drugs given first are called neoadjuvant treatment. In locally advanced rectal cancer, chemoradiation is commonly given first. It can shrink a tumour so that it is easier to remove completely.
  • Drugs after surgery: This is called adjuvant treatment. It targets cells that may be left behind after the operation.
  • No surgery at all: Some cancers never reach an operating table. Leukaemia and lymphoma, for example, are treated mainly with drugs. For the rest, the site and the stage decide.

Key Takeaways

  • Oncology vs surgery is not an either-or choice. Surgery is one treatment inside oncology.
  • Drugs go through the whole body; surgery works on one spot.
  • A surgical oncologist is a cancer surgeon who works with the drug and radiation specialists.
  • Cancer type, stage and fitness for surgery decide what comes first.
  • Neoadjuvant means drugs before surgery. Adjuvant means drugs after it.

Frequently Asked Questions

Is oncology the same as surgery?

No. Surgery is one of the treatments oncology uses.

What does a surgical oncologist do?

Confirms the cancer, stages it, and operates when surgery is needed.

Does everyone with cancer need an operation?

No. It depends on where the cancer is and how far it has gone.

Can chemotherapy alone treat a solid tumour?

Sometimes. More often it works alongside surgery or radiation.

References


  1. Recognizing the role of surgical oncology and cancer imaging in the multidisciplinary approach to cancer: an important area of future scholarly growth for BMC Cancer. https://pmc.ncbi.nlm.nih.gov/articles/PMC3724699/
  2. Delivering cancer services: a multi-disciplinary approach. https://pmc.ncbi.nlm.nih.gov/articles/PMC3097621/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Robotic vs Laparoscopic vs Open Surgery for Rectal Cancer: How Do They Compare?

Robotic vs Laparoscopic vs Open Surgery for Rectal Cancer: How Do They Compare?

Rectal cancer surgery can be done robotically, laparoscopically or through an open incision, and the right choice turns on where the tumour sits, how narrow the pelvis is and what kind of recovery the patient is aiming for. All three can cure the cancer in experienced hands, which is why the decision is about what fits the individual patient and not about which technology is newest.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at  Clinic, Bangalore, explains how the three approaches are weighed in rectal cancer surgery. “Patients often come asking which of the three is best. The rectum is hard to reach, down in a narrow pelvis, so how we operate matters a little more here than in other cancers. Whatever the route, the plan is the same: take the whole tumour out, save the nerves and the sphincter if the cancer allows it, and get the patient back on their feet. If one route does that better for you, that’s the one we use.”

 If you’d like to talk through your own options, the clinic can be reached at +91 9482202240.

How Do Robotic, Laparoscopic and Open Rectal Cancer Surgery Differ?

The aim is the same in all three. What changes is how the surgeon gets down to a tumour sitting low in the pelvis.

Open surgery: One longer cut in the abdomen. The surgeon can put their hands in and see the area directly.

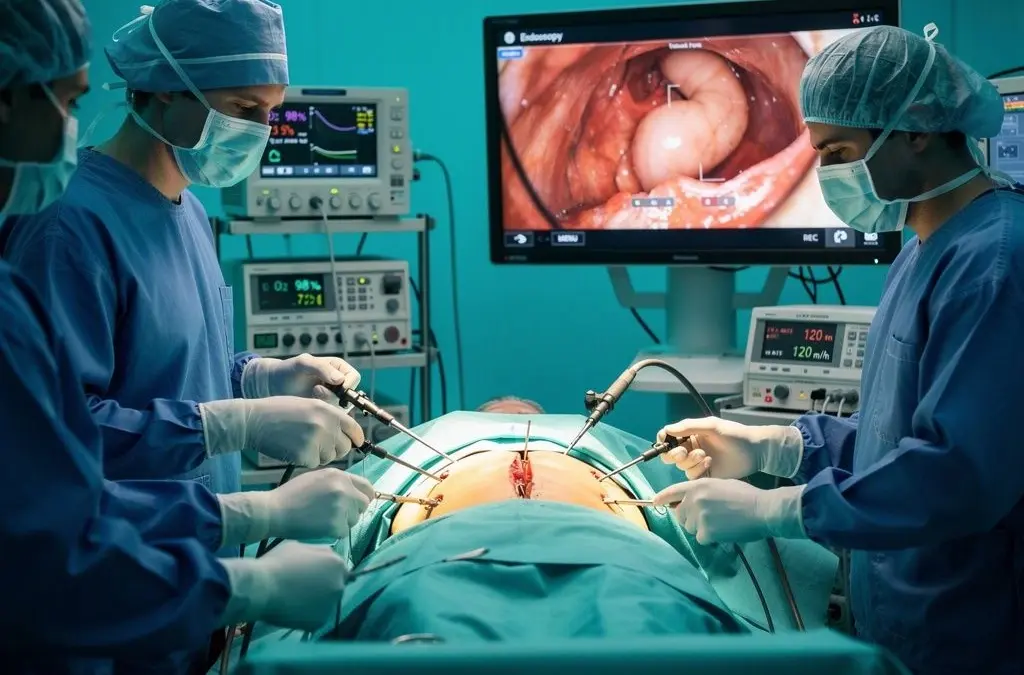
Laparoscopic surgery: Several short cuts take its place. A camera and thin instruments go through them, and the surgeon works by hand while watching a monitor.

Robotic surgery: The cuts are small here too. The surgeon sits at a console a few feet from the patient, the screen is magnified and in 3D, and the instrument tips can turn in ways a straight laparoscopic instrument can’t. The robot decides nothing. Every movement is the surgeon’s own.

What stays constant: In all three, the central step is total mesorectal excision, where the rectum comes out together with the fat and lymph nodes around it as a single package. How cleanly that is done matters more than which instrument did it. Our page on robotic cancer surgery explains how the system works.

Is Minimally Invasive Surgery as Effective as Open Surgery for Rectal Cancer?

For laparoscopic surgery, the evidence is reasonably firm.

The COLOR II trial: Roughly a thousand patients were randomly placed into laparoscopic or open surgery groups. Three years later the cancer had returned in the pelvis in 5% of each group, and survival was close.

Recovery: People who had keyhole surgery tended to bleed less, have less pain and go home sooner.

A caution: Rectal surgery by keyhole is demanding, and the trial results came from surgeons who did it regularly.

For a wider look across other cancers, see our blog on whether minimally invasive cancer surgery gives the same cure rate as open surgery.

What Determines Treatment Choice?

Every patient is assessed individually, and a handful of points steer the decision.

Where the tumour is: Upper, middle or low rectum, and how far it lies from the anal opening.

Stage and what comes before surgery: Many patients have chemotherapy or radiation first, and how the tumour responds can change the plan.

Pelvic anatomy and build: A narrow pelvis, a heavier build or a bulky tumour can make one approach harder than another.

Sphincter and stoma: Whether the sphincter can be saved, and whether a temporary or a permanent stoma will be needed.

General health and old scars: Fitness for a long operation, and what earlier surgery has left behind.

The team’s experience: How often they do this operation, and by which route.

What matters to you: Recovery time, scars and everyday life all count once the options have been laid out. A case study on advanced rectal cancer care shows how that works in practice.

Key Takeaways

  • Any of the three approaches can remove a rectal cancer completely. How cleanly the mesorectum is taken out matters more than which instrument is used.
  • In the large COLOR II trial, laparoscopic and open surgery gave similar recurrence and survival at three years, and keyhole patients recovered faster.
  • Randomised trials haven’t shown that robotic surgery cuts the need to convert to open surgery. It may still help with a narrow pelvis or a low tumour.
  • Open surgery remains the safer route for some tumours, for emergencies and for a pelvis scarred by earlier operations.
  • Tumour position, stage, earlier treatment, pelvic anatomy and the surgeon’s experience decide the approach.
  • To talk through your own case, you can book an appointment or call the clinic on +91 9482202240.

Frequently Asked Questions

Is robotic surgery better than laparoscopic surgery for rectal cancer?

In the trials so far the cancer results look alike, so the surgeon’s skill counts for more than the machine.

Is laparoscopic surgery as good as open surgery for rectal cancer?

In the COLOR II trial, recurrence and survival at three years were alike, and keyhole patients recovered faster.

Will I need a stoma after rectal cancer surgery?

Sometimes, and it may be temporary or permanent, depending on how low the tumour is and how close it comes to the sphincter.

When is open surgery still preferred for rectal cancer?

When the tumour has grown into nearby organs, in an emergency, or when old scar tissue makes keyhole risky.

References


Robotic vs Laparoscopic Surgery for Rectal Cancer: ROLARR Randomized Clinical Trial Compares robotic and laparoscopic rectal cancer surgery, including conversion to open surgery, complications and cancer-related outcomes. Read the study – JAMA / PubMed Central

Robotic-Assisted vs Laparoscopic Resection for Rectal Cancer Reviews clinical outcomes, quality of life and costs associated with robotic and laparoscopic surgery. Read the study – NIHR Journals Library

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Robotic vs Laparoscopic vs Open Surgery for Rectal Cancer: How Do They Compare?

Minimally Invasive vs Open Esophagectomy: How Do Outcomes Compare?

Compared with open esophagectomy, the minimally invasive route puts the body through less surgical trauma. Blood loss is lower and lung complications are fewer, especially in the weeks right after the operation. Long-term cancer outcomes in the trials so far are comparable, so the decision comes down to the tumour, the patient’s overall health and how experienced the surgeon is with the technique.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, explains how the two approaches compare for cancers of the food pipe. “It’s a big operation however you do it. What the keyhole route changes is the chest wall, which isn’t cut open, and you see that in the first few weeks, with fewer chest infections and an easier recovery. None of that counts if the cancer isn’t cleared as well, so that’s the first thing we make sure of.”

If you’d like to know more about tongue cancer surgery, call the clinic on +91 9482202240.

What Is the Difference Between Minimally Invasive and Open Esophagectomy?

Both operations do the same job. The diseased part of the food pipe comes out, and what’s left gets joined to the stomach. How the surgeon reaches it is what differs.

Open: Big cuts, one in the chest and one in the abdomen. The surgeon works through them by hand.

Keyhole: A few small cuts instead. A camera and long, thin instruments go in through openings in the chest and belly.

Hybrid: Part keyhole, part open. Some surgeons do the abdomen by keyhole and the chest the open way.

Robotic: The same small cuts, with a robot holding the instruments and giving the surgeon a magnified 3D view.

What doesn’t change: The tumour and the nearby lymph nodes come out whichever route is used. The stomach is shaped into a tube and lifted up to take the place of the food pipe. If you’re curious how keyhole operations work in general, our page on laparoscopic cancer surgery explains it.

When Is Open Esophagectomy Still the Better Choice?

Keyhole isn’t for everyone.

Large or invasive tumours: A tumour pressing on nearby structures can call for the room and control that open surgery gives.

Earlier surgery: Scarring from a previous chest or abdominal operation can make keyhole surgery harder to do safely.

Changing course: Sometimes the surgeon starts with keyhole and moves to open because carrying on isn’t safe. That’s judgement, not a failed operation.

Experience: It’s a demanding operation to do by keyhole, and results are best where the team does it regularly. You can read about the surgeon’s background on our expertise page.

What Determines Treatment Choice?

It’s decided case by case. A few things steer it.

Stage and site: Where in the food pipe the cancer sits, how deep it goes, and whether the lymph nodes are involved. Esophageal cancer is one of the upper GI cancers, and the stage shapes the whole plan.

Before surgery: Many patients have chemotherapy or chemoradiation first, and how the tumour responds affects the planning.

General health: Heart, lungs and nutrition all count. A lot of people have lost weight because swallowing has been difficult.

Team review: Surgical, medical and radiation oncologists usually go through the case together.

Your priorities: Recovery time, scars, getting back to normal life. Robotic-assisted surgery is one of the keyhole options, and our page on robotic cancer surgery covers it.

Key Takeaways

  • Minimally invasive esophagectomy may reduce blood loss, lung complications, and hospital stay compared with open surgery.

  • Long-term survival outcomes appear similar between the two approaches in available clinical trials.

  • Open surgery may be more suitable for certain tumours, depending on their location and extent.

  • The choice of surgical approach depends on the patient’s condition, tumour characteristics, and the surgeon’s experience.

  • Discuss the benefits and risks of each option with your specialist. To learn more, book an appointment or call +91 9482202240.

Frequently Asked Questions

Is minimally invasive esophagectomy as safe as open surgery?

 So far, yes, with fewer early lung problems, though it depends on the surgeon’s experience.

Does minimally invasive esophagectomy cure cancer as well as open surgery?

Survival looked similar at three years in the main trial.

How long is recovery after minimally invasive esophagectomy?

 You’ll usually leave hospital sooner than after open surgery, but full recovery still takes weeks to months.

When is open esophagectomy still preferred?

For large tumours pressing on nearby structures, or after earlier surgery that makes keyhole unsafe.

References


National Cancer Institute (NCI) – Esophageal Cancer Treatment (PDQ®) Explains treatment options for esophageal cancer, including surgery, and discusses factors that influence treatment decisions. Link: https://www.cancer.gov/types/esophageal/hp/esophageal-treatment-pdq

American Cancer Society – Surgery for Esophageal Cancer Describes esophagectomy, including minimally invasive and open surgical approaches, and outlines potential risks and recovery considerations. Link: https://www.cancer.org/cancer/types/esophagus-cancer/treating/surgery.html

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Total vs Subtotal Gastrectomy: How Is the Extent of Surgery Decided?

Total vs Subtotal Gastrectomy: How Is the Extent of Surgery Decided?

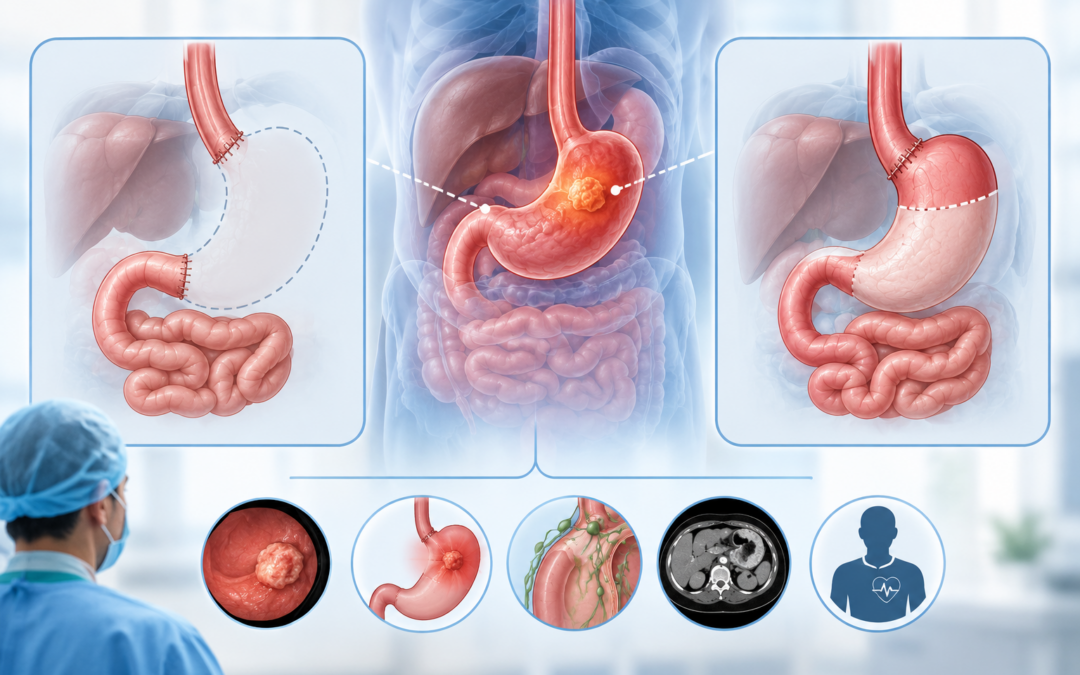
Most patients ask the same thing when surgery is advised for stomach cancer: how much of my stomach will be taken out? Put simply, there are two answers. Either all of it (total gastrectomy) or a part of it, usually the lower part (subtotal gastrectomy). Which one you get depends mostly on where the tumour is, how big it is and how it’s behaving. Doctors would rather save some stomach, because it helps with eating and nutrition later. But removing all the cancer always comes first. This is how total vs subtotal gastrectomy is decided.

According to Dr. Sandeep Nayak, a surgical oncologist in Bangalore, says you can’t name the exact operation from a diagnosis alone. The endoscopy, CT scan and biopsy come first, and even then the plan can still change during surgery, if the cut edge shows cancer.

If you have an endoscopy or biopsy report and want it explained, you may contact MACS Clinic on +91 9482202240.

What Total and Subtotal Gastrectomy Involve?

Surgery is a big part of stomach cancer treatment. Here is what each operation actually takes out.

  • Total gastrectomy: Here the whole stomach goes, top to bottom, cardia and pylorus included. The food pipe is joined directly to the small intestine.
  • Subtotal gastrectomy: A good part of the lower stomach is taken out together with the pylorus. What remains, a small upper pouch, is joined to the intestine.
  • Lymph nodes: Neither operation is only about the stomach. The glands lying along its curves are cleared as well, since that is where the disease tends to travel first.
  • Reconstruction: The intestine has to be reconnected after the stomach is out, otherwise food has nowhere to go. How? That depends on how much stomach is left.
  • Proximal gastrectomy: Ever heard of a proximal gastrectomy? Only the upper stomach is removed. It is rare. Only a few early tumours high up are suitable for it.

Total vs Subtotal Gastrectomy: What Decides the Extent?

What does the oncology team look at? A few things, and always together.

  • Tumour location: Low in the stomach? Then a subtotal gastrectomy is often possible. Middle or upper stomach? You’re more likely to need a total gastrectomy.
  • A clear margin: The cut edge must be free of cancer. If a clear margin cannot be reached by removing only the lower stomach, the surgeon moves to a total gastrectomy. A frozen section, reported while you are still on the table, is sometimes sent to check.
  • Size and depth: Big tumours need a wider cut, and so do tumours that have grown deep into the wall. Sometimes that leaves too little healthy stomach worth keeping.
  • Pattern of spread: Some cancers, the diffuse type for instance, spread along the stomach wall. What you see on the surface may not show how far they have gone. So a larger resection may be needed.
  • Nearby organs: If the tumour has reached the pancreas and surgery needs to remove part of it along with the spleen, a total gastrectomy is advised, wherever the tumour began.

What Determines Recovery and Nutritional Needs After Gastrectomy?

Recovery after gastrectomy depends on how much of the stomach is removed, the patient’s nutritional status and how well the body adapts to changes in digestion.

  • Extent of surgery: After subtotal gastrectomy, some stomach capacity remains. Total gastrectomy requires the digestive system to adapt to food passing directly from the oesophagus into the small intestine.

  • Meal planning: Small, frequent meals may help patients manage reduced food capacity and maintain adequate nutrition.

  • Vitamin and mineral levels: Vitamin B12 replacement is necessary after total gastrectomy. Iron, calcium and other nutritional levels may also need monitoring.

  • Digestive symptoms: Some patients experience dumping syndrome, cramps, sweating or diarrhoea after meals. Dietary adjustments can help manage these symptoms.

  • Follow-up care: Regular medical reviews, blood tests, weight monitoring and nutritional assessment help identify deficiencies and support recovery.

Key Takeaways

  • Total gastrectomy means the whole stomach is removed; subtotal removes only the lower part.
  • Where the tumour is, how big and deep it is, and how it spreads decide total vs subtotal gastrectomy.
  • Removing all the cancer comes before saving stomach.
  • Your surgeon may switch from subtotal to total during the operation if the margin isn’t clear.
  • Eating and vitamin B12 needs change after both operations, so follow-up matters.


Frequently Asked Questions

Is subtotal gastrectomy always safer?

Not always. A clear margin matters more than how much stomach is saved.

Can the surgeon change the plan during the operation?

Yes. If the margin isn’t clear, more is removed

Can I live without a stomach?

Yes, with small meals, diet advice and vitamin B12 replacement.

Is subtotal the same as distal gastrectomy?

Mostly. Both mean the lower stomach is removed.

References


  1. Japanese Gastric Cancer Association. Japanese gastric cancer treatment guidelines 2018 (5th edition). Gastric Cancer. 2021;24(1):1-21. https://pmc.ncbi.nlm.nih.gov/articles/PMC7790804/
  2. Impact of Surgical Margins on Overall Survival after Gastrectomy for Gastric Cancer: A Validation of Japanese Gastric Cancer Association Guidelines on a Western Series. https://pmc.ncbi.nlm.nih.gov/articles/PMC8989928/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

What Is the Peritoneal Cancer Index (PCI), and Who Qualifies for Cytoreductive Surgery with HIPEC?

What Is the Peritoneal Cancer Index (PCI), and Who Qualifies for Cytoreductive Surgery with HIPEC?

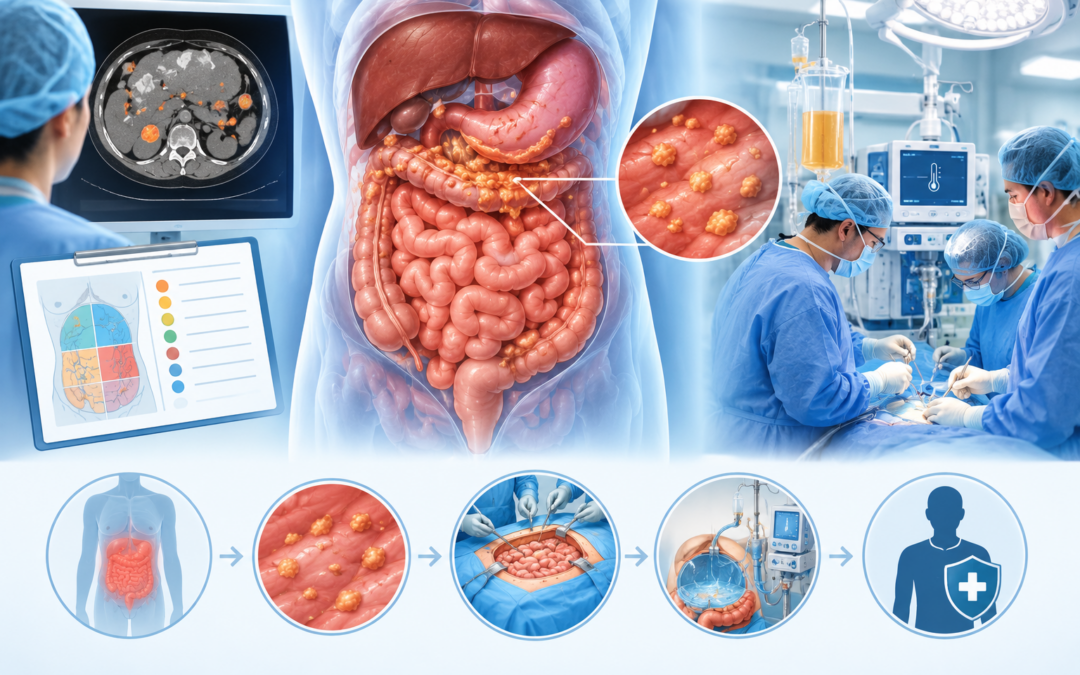
When cancer spreads to the peritoneum, the lining of the abdomen, the surgical team needs an objective way to measure it. The peritoneal cancer index (PCI) does that by scoring how much disease is present and how widely it has spread. It is one of the first things assessed when deciding whether cytoreductive surgery with HIPEC is a realistic option, though it is never the only factor.

According to Dr. Sandeep Nayak, a surgical oncologist in Bangalore, the number alone doesn’t settle anything. The scans, the type of cancer, how fit the patient is and what can actually be removed all go into the decision, and the final score is often confirmed only once the surgeon looks inside.

If you have a scan or biopsy report that shows spread in the abdomen and you’d like it explained, you can contact  Clinic on +91 9482202240.

What the Peritoneal Cancer Index Measure?

Before anyone talks about HIPEC treatment, the first question is how far the disease has gone. The PCI is how that gets answered.

Thirteen regions: The surgeon divides the abdomen into 13 areas. Nine cover the abdomen and pelvis, and four cover the small bowel.

Lesion size score: Each area gets a score from 0 to 3, based on the biggest tumour deposit in it. Zero means nothing visible. A 3 means deposits bigger than 5 cm, or disease that has joined up into one sheet.

Total score: Add the 13 scores together and you land somewhere between 0 and 39. More disease, higher number.

How it’s measured: A scan gives you an estimate. The most reliable PCI is the one the surgeon sees with their own eyes at the start of the operation.

Completeness score: Once the surgery is done, a separate CC score records how much disease was left behind. The aim is CC-0 or CC-1.

Who Qualifies for Cytoreductive Surgery with HIPEC?

No single number decides this. The oncology team looks at several things together.

Where the cancer began: Cancers of the appendix, colon, ovary and the peritoneum itself are the usual ones considered. Stomach cancer comes into it in selected cases.

The PCI range: In colon and rectal cancer, a PCI above about 20 is usually seen as too high for surgery. Other cancers use different cut-offs, and in ovarian cancer the PCI isn’t a fixed rule.

Can it all come out? This is the real question. Can the surgeon remove all the visible disease and finish with a CC-0 or CC-1 result? If not, the operation usually doesn’t go ahead.

Fitness: It’s a long, major operation. How active you are day to day matters, and so do your heart, lungs, kidneys and liver.

Spread outside the abdomen: Disease that stays within the peritoneum is the ideal. Spread to distant organs, or deposits in places that can’t be removed, can rule surgery out even when the PCI is low.

Beyond the PCI Score: Assessment and What to Expect?

Scans can miss small deposits, so the team sometimes wants a direct look inside the abdomen. A staging laparoscopy, which falls under laparoscopic cancer surgery, does exactly that.

Scans first: A CT or PET-CT of the abdomen and pelvis gives an early estimate of the PCI. Small deposits, especially on the surface of the bowel, are easy to miss.

Staging laparoscopy: A few small cuts and a camera, so the surgeon can see all 13 regions. They can score the PCI and judge whether complete removal is possible.

The plan can change: The score in the operating theatre may differ from the scan estimate, and the plan shifts with it.

The operation: Cytoreductive surgery removes all the visible disease. HIPEC follows, with heated chemotherapy circulated inside the abdomen for a set time to treat whatever can’t be seen.

Recovery: It’s a major operation, so expect a hospital stay, nutrition support and regular follow-up scans. Your team will explain what applies to you.

Key Takeaways

  • Cytoreductive surgery: Removes all visible cancer deposits where complete removal is feasible.

  • HIPEC: Heated chemotherapy is circulated inside the abdomen for a set period to treat remaining microscopic cancer cells.

  • Recovery: Recovery may involve a hospital stay, nutritional support and regular follow-up scans. The care team will guide patients based on their individual needs.

Frequently Asked Questions

Is a high PCI always a reason to avoid surgery?

Not always, since the cut-off depends on the type of cancer.

What is the range of the PCI score?

From 0, meaning no visible disease, up to 39.

Can the PCI be worked out from a scan alone?

Only roughly, because the surgeon’s direct view is more accurate.

Is HIPEC given on its own?

Usually not. It follows cytoreductive surgery that removes the visible disease.

References


Peritoneal Cancer Index and Patient Selection for CRS and HIPEC Explains how PCI measures the extent and distribution of peritoneal disease and how it helps assess suitability for cytoreductive surgery. Read the reference – PubMed Central

 Indications for Cytoreductive Surgery and HIPEC: Clinical Practice Guideline Reviews evidence and recommendations for CRS with HIPEC across ovarian, colorectal, gastric and other peritoneal cancers. Read the reference – Current Oncology / PMC

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Call Now Button