

support@macsclinic.com
+91 9482202240
What Is Enhanced Recovery After Surgery?

What Is Enhanced Recovery After Surgery?

Enhanced Recovery After Surgery, usually shortened to ERAS, is a set of evidence based steps that help patients recover faster after major surgery. It isn’t one treatment. It’s a whole pathway, covering the days before, during and after the operation. The aim is simple: less stress on the body, fewer complications, and home sooner. It’s now standard for major cancer operations.

According to Dr. Sandeep Nayak, Surgical Oncologist in India, “ERAS changed how we think about recovery. The old way kept patients fasting for ages and flat in bed for days. We now know that’s actually worse. Letting people eat sooner, walk the same day, and managing pain without leaning on heavy opioids, all of it helps the body bounce back. The science behind each step is solid.”

Curious how recovery from cancer surgery has changed?

What Does ERAS Involve?

It’s a coordinated set of steps across the whole surgical journey, each one backed by evidence.

  • Before surgery : Proper counselling, good nutrition and shorter fasting. Some patients even get a carbohydrate drink before, which eases the stress of surgery.
  • Smarter pain control : Pain is managed with a mix of methods that lean away from heavy opioids. Less grogginess, fewer side effects, quicker movement.
  • Early eating : Food returns within hours, not days. The gut wakes up faster when it’s used, and that speeds the whole recovery along.
  • Early walking : Getting up the same day matters more than people expect. It cuts clot risk, helps the lungs and gets the body moving again.

These principles work hand in hand with minimally invasive techniques, and robotic cancer surgery makes the smaller incisions that let ERAS deliver its full benefit.

Why Does It Work So Well?

ERAS works because it treats recovery as something to actively manage, not just wait out.

  • Less surgical stress : Every step is designed to reduce the body’s stress response to surgery. Lower stress means a faster, smoother recovery.
  • Fewer complications : Early movement and eating cut the rate of chest infections, clots and gut problems. The data on this is consistent.
  • Shorter stays : Patients go home days earlier than with old style care. That’s not rushing them, it’s that they’re genuinely ready sooner.
  • Better cancer care : Recovering faster means starting any needed chemotherapy sooner. For cancer patients, that timing genuinely matters.

It pairs perfectly with laparoscopic cancer surgery, where the smaller incisions and faster healing amplify everything ERAS is trying to achieve.

Why Choose Dr. Sandeep Nayak for Cancer Surgery?

Dr. Sandeep Nayak is a surgical oncologist with 24 years behind him and a fellowship in laparoscopic and robotic onco-surgery. His practice combines minimally invasive surgery with structured recovery pathways, so patients heal faster and with fewer setbacks. The whole approach is built around reducing the toll surgery takes, since a smoother recovery isn’t a luxury, it’s part of good cancer care.

Recovery is where minimally invasive surgery and ERAS reinforce each other. Smaller incisions mean less pain and trauma, which makes early eating and walking far easier to achieve. Patients spend less time in hospital, face fewer complications, and get back to their lives, and any further treatment, sooner. That combination is what modern surgical recovery is built on.

Frequently Asked Questions

What is Enhanced Recovery After Surgery?

It’s a set of evidence based steps that speed recovery after major surgery.

What does the ERAS protocol involve?

Careful preparation, less fasting, early eating, early walking and opioid sparing pain control.

Does ERAS shorten hospital stay?

Yes. ERAS consistently reduces hospital stay and lowers postoperative complications across major surgeries.

Is ERAS used in cancer surgery?

Yes. It’s widely used in colorectal, liver and other major cancer operations.

References

  1. ERAS protocol in colorectal cancer resections — National Library of Medicine
  2. Enhanced recovery after surgery systematic review — National Library of Medicine

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
What Is Organ-Sparing Cancer Surgery?

What Is Organ-Sparing Cancer Surgery?

Organ-sparing cancer surgery removes the tumour while keeping as much of the organ, and its function, as safely possible. The older approach often meant taking the whole organ to be sure. This one aims narrower: clear the cancer, save the rest. It only works when the tumour’s size, location and stage allow it, but when they do, the difference to a patient’s life is real.

According to Dr. Sandeep Nayak, Surgical Oncologist in India, “The goal has shifted. We used to remove the whole organ to be certain the cancer was gone. Now, in the right cases, we can take the tumour with a clear margin and leave the function intact. A breast, a working sphincter, a kidney. But it’s never function over cure. The cancer control has to be equal first. Only then does preservation come in.”

Wondering if your cancer can be treated without losing the organ?

How Does It Work?

The principle is precision: take exactly what’s diseased and protect what isn’t.

  • Clear margins first : The tumour comes out with a rim of healthy tissue around it. That clearance is non negotiable, function comes after.
  • Sparing the rest : Surrounding nerves, muscle and healthy organ tissue are carefully preserved. What stays is what keeps the organ working.
  • Right patient : It isn’t for everyone. Tumour size, position and stage decide whether sparing is safe or whether full removal is wiser.
  • Better tools help : Robotic and minimally invasive techniques make the fine dissection possible, getting close to structures without damaging them.

This kind of precision is the backbone of modern robotic cancer surgery, where the technology exists specifically to spare what doesn’t need removing.

Where Is It Used?

Organ-sparing approaches now exist across many cancer types, each with its own version.

  • Breast : Breast conserving surgery removes the lump, not the whole breast. For early disease, outcomes match mastectomy with far less loss.
  • Rectum : Sphincter preserving surgery lets many patients avoid a permanent stoma. The bowel keeps working the way it should.
  • Kidney : Partial nephrectomy takes the tumour and leaves the rest of the kidney. Preserving kidney function matters enormously long term.
  • Testis and bladder : Selected cases allow part of the organ to be saved, protecting fertility, hormones or urinary function where possible.

A clear example is avoiding a permanent stoma in rectal cancer, where preserving the sphincter changes daily life entirely.

Why Choose Dr. Sandeep Nayak for Cancer Surgery?

Dr. Sandeep Nayak is a surgical oncologist with 24 years behind him and a fellowship in laparoscopic and robotic onco-surgery. His work centres on removing cancer completely while preserving function wherever the tumour allows, across breast, colorectal, kidney and other cancers. The approach always puts cancer control first, then asks how much can safely be saved. That order is what makes organ preservation responsible rather than risky.

Organ sparing only works in skilled, high volume hands. Judging exactly how much can be safely preserved, and executing that dissection precisely, takes experience built over years. Done well, it means a patient beats their cancer and keeps a breast, a kidney or normal bowel function. That balance, full cure with minimal loss, is the whole point of modern surgical oncology.

Frequently Asked Questions

What is organ-sparing cancer surgery?

It removes a tumour while preserving as much of the organ’s function as possible.

Is organ-sparing surgery as safe as full removal?

In suitable cases, yes. Cancer control stays equivalent when patients are selected carefully.

Which cancers allow organ-sparing surgery?

Breast, rectal, kidney, bladder and testicular cancers often allow organ preserving approaches.

Who qualifies for organ-sparing surgery?

It depends on tumour size, location and stage, decided after careful imaging and assessment.

References

  1. Organ preservation in cancer surgery review — National Library of Medicine
  2. Organ preservation for rectal cancer — National Library of Medicine

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
What Is Intraoperative Ultrasound in Surgery?

What Is Intraoperative Ultrasound in Surgery?

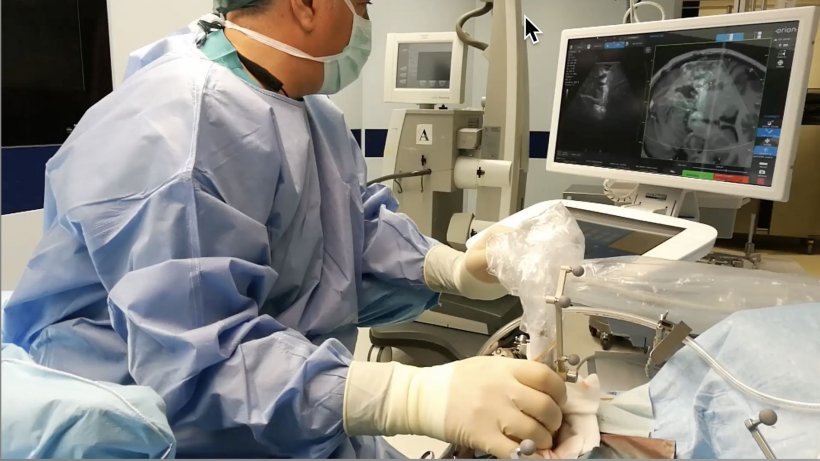
Intraoperative ultrasound is imaging done live, during the operation itself. The surgeon places an ultrasound probe directly on the organ to see inside it in real time. It shows tumours, blood vessels and structures that scans before surgery can’t fully map. The point is simple: see exactly what’s there, right when it matters most.

According to Dr. Sandeep Nayak, Surgical Oncologist in India, “Scans done before surgery are a plan, not a live map. Once we’re operating, things shift, and a small tumour deep in the liver can be impossible to feel. Intraoperative ultrasound lets us look inside the organ as we work. It finds what the hands can’t, and it keeps us off the vessels we need to protect.”

Want to understand how modern cancer surgery achieves its precision?

How Does It Work?

A probe goes straight onto the organ, and the surgeon reads the picture as the operation unfolds.

  • Direct contact : The sterile probe touches the organ itself, not the skin. That closeness gives far sharper images than a scan from outside.
  • Real time : The picture updates live as the surgeon moves. No waiting, no guessing from an image taken hours earlier.
  • No radiation : It uses sound waves, not X-rays. So it can be used freely during surgery without any radiation worry for anyone in the room.
  • Finds the hidden : A small tumour buried deep in tissue, invisible and impossible to feel, shows up clearly on the screen.

This kind of precision underpins modern robotic cancer surgery, where seeing inside the organ in real time changes what the surgeon can safely do.

Where Is It Most Useful?

Some operations lean on intraoperative ultrasound far more than others, usually where tumours hide.

  • Liver surgery : The biggest user. The liver hides tumours deep in its substance, and the probe finds every one before the surgeon cuts.
  • Pancreas : Small tumours and the vessels around them are mapped precisely, which matters enormously in such a delicate area.
  • Brain : Surgeons use it to locate tumours and judge how much has been removed, all without moving the patient for a scan.
  • Protecting margins : By showing the tumour edge in real time, it helps the surgeon take enough tissue without taking too much.

This is exactly how a clean surgical margin gets achieved in practice, by seeing the tumour boundary rather than estimating it.

Why Choose Dr. Sandeep Nayak for Cancer Surgery?

Dr. Sandeep Nayak is a surgical oncologist with 24 years behind him and a fellowship in laparoscopic and robotic onco-surgery. He uses real time imaging tools like intraoperative ultrasound where they genuinely improve precision, particularly in liver and complex abdominal cancer surgery. The approach is built on seeing clearly before cutting, since a tumour you can locate exactly is one you can remove completely. That clarity is what separates a good resection from an incomplete one.

Precision tools only matter in trained hands. Reading an ultrasound image mid surgery and acting on it instantly takes experience that comes from volume. Used well, it means smaller margins of error, better protection of healthy tissue, and a cleaner removal of the cancer. That combination of skill and the right technology is what drives a good surgical outcome.

Frequently Asked Questions

What is intraoperative ultrasound?

It’s real time ultrasound imaging used during surgery to locate tumours and guide the operation.

Why is intraoperative ultrasound used?

It finds tumours, maps blood vessels and helps the surgeon achieve clear margins.

Where is intraoperative ultrasound most useful?

It’s especially valuable in liver, pancreas and brain surgery where tumours sit hidden.

Does intraoperative ultrasound use radiation?

No. Ultrasound uses sound waves, so it adds no radiation during the operation.

References

  1. Intraoperative ultrasound applications and value — National Library of Medicine
  2. Intraoperative ultrasound implementation guide — National Library of Medicine

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
 Does a Cancer Vaccine Exist in India?

 Does a Cancer Vaccine Exist in India?

Cancer vaccines do exist in India, and they’re already in everyday use. The catch is what kind. The ones available now are preventive, they stop the infections that lead to certain cancers, rather than treating cancer that’s already there. The HPV vaccine and the Hepatitis B vaccine are the two big examples, both widely available.

According to Dr. Sandeep Nayak, Surgical Oncologist in India, “People hear cancer vaccine and picture a shot that cures cancer. That’s not what these are, at least not yet. The HPV and Hepatitis B vaccines prevent the viral infections that cause cervical and liver cancer. They work brilliantly, but only before exposure. The vaccines that treat existing cancer are still mostly in trials.”

Want to understand cancer prevention options for your family?

Which Cancer Vaccines Are Available?

India has preventive vaccines that genuinely stop certain cancers from ever starting.

  • HPV vaccine : Prevents the high risk HPV strains behind most cervical cancer. Given to girls before exposure, it’s a true cancer preventer.
  • CERVAVAC : India’s own HPV vaccine, made by the Serum Institute. Affordable and indigenous, it’s now part of a national rollout.
  • Hepatitis B vaccine : Long part of routine immunisation. By preventing chronic Hepatitis B, it cuts the risk of liver cancer down the line.
  • The catch : All of these are preventive. They work before the infection takes hold, which is why timing and age matter so much.

This is why prevention starts young, and proper cervical cancer treatment becomes far less likely in populations where HPV coverage is high.

What About Vaccines That Treat Cancer?

This is where the science is moving fast, but the everyday reality lags behind.

  • Therapeutic vaccines : These aim to train the immune system to attack an existing tumour. Different goal entirely from prevention.
  • Still in trials : Most therapeutic cancer vaccines remain investigational worldwide. Promising results, but not yet routine care.
  • Personalised approaches : Some newer vaccines are built around a patient’s own tumour mutations. Cutting edge, but far from widely available.
  • The honest position : For now, treating cancer still rests on surgery, chemotherapy, radiation and immunotherapy. Vaccines treating cancer are coming, not here.

Prevention remains the proven path, which is why the HPV vaccine matters so much as a tool that stops cancer at the source.

Why Choose Dr. Sandeep Nayak for Cancer Care?

Dr. Sandeep Nayak is a surgical oncologist with 24 years behind him and a fellowship in laparoscopic and robotic onco-surgery. He treats HPV related cancers, including cervical and head and neck disease, where prevention and early detection shape outcomes long before surgery enters the picture. The approach starts with separating what vaccines can actually do from the hype, since clear information is what lets families make sound decisions.

The distinction matters more than people realise. A preventive vaccine given at the right age can stop a cancer that would otherwise need major surgery years later. That’s a genuine win. Understanding which vaccines exist, what they do, and when they work is part of giving patients an honest, complete picture of their options.

Frequently Asked Questions

Does a cancer vaccine exist in India?

Yes. Preventive vaccines like HPV and Hepatitis B that prevent cancer are available in India.

Which vaccines prevent cancer?

HPV vaccines prevent cervical and related cancers, and Hepatitis B vaccine lowers liver cancer risk.

What is CERVAVAC?

CERVAVAC is India’s indigenous HPV vaccine, made affordable for cervical cancer prevention.

Is there a vaccine that treats existing cancer?

Therapeutic cancer vaccines exist in trials, but they aren’t yet standard routine treatment.

References

  1. HPV vaccination and cervical cancer in India — National Library of Medicine
  2. Cervical cancer prevention overview — National Cancer Institute

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Why Is Gallbladder Cancer Caught Late?

Why Is Gallbladder Cancer Caught Late?

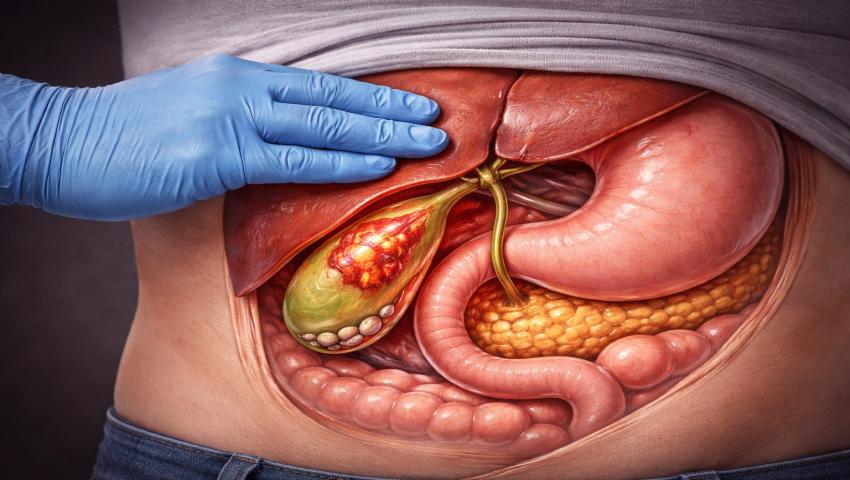
Gallbladder cancer is caught late mostly because it hides in plain sight. Its early symptoms look exactly like gallstones, which are far more common, so the cancer gets overlooked. The gallbladder also sits tucked under the liver, out of easy reach. Often the cancer is only found by chance, during surgery for something else.

According to Dr. Sandeep Nayak, Surgical Oncologist in India, “Gallbladder cancer is one of the most quietly deceptive cancers. The early signs, vague upper abdominal pain, nausea, are identical to ordinary gallstone trouble. So it’s treated as that. By the time clearer signs appear, the disease has usually advanced. A surprising number of cases are only picked up when a gallbladder removed for stones turns out to contain cancer.”

Have ongoing gallbladder symptoms that won’t settle?

Why Does It Stay Hidden So Long?

Several things conspire to keep this cancer out of sight until it’s advanced.

  • Gallstone disguise : Early symptoms copy gallstones almost exactly. Pain and nausea get blamed on stones, and the cancer slips through.
  • Hidden location : The gallbladder sits under the liver, hard to feel and easy to miss on a quick scan. Small tumours stay invisible.
  • No early signs : In its earliest stage the cancer often causes nothing at all. By the time it speaks up, it’s already grown.
  • No screening : There’s no routine test for gallbladder cancer like there is for some others. Nobody goes looking until symptoms force it.

This is why imaging matters so much, and the right gallbladder cancer assessment depends on not dismissing persistent symptoms as simple stones.

How Is It Often Discovered?

When gallbladder cancer is found, it’s frequently through routes nobody planned.

  • Incidental finding : A common route. The gallbladder is removed for stones, and the lab report comes back with cancer nobody expected.
  • Late symptoms : Jaundice, a hard lump, real weight loss. These bring people in, but they tend to signal advanced disease.
  • Imaging by chance : Sometimes a scan done for an unrelated complaint spots a thickened gallbladder wall or a mass. A lucky catch.
  • Risk based vigilance : People with long standing gallstones or a calcified gallbladder warrant closer watching. That’s where earlier catches happen.

Recognising which cancer testing applies when symptoms persist is what occasionally turns a late diagnosis into an earlier one.

Why Choose Dr. Sandeep Nayak for Gallbladder Cancer Care?

Dr. Sandeep Nayak is a surgical oncologist with 24 years behind him and a fellowship in laparoscopic and robotic onco-surgery. He treats hepatobiliary cancers, including gallbladder and bile duct disease, where recognising the deceptive early picture makes all the difference. The approach starts with taking persistent gallbladder symptoms seriously rather than assuming stones. That scrutiny is what catches the occasional cancer hiding among them.

Incidental gallbladder cancer needs particular expertise. When cancer turns up unexpectedly in a removed gallbladder, what happens next, proper staging and often a second, more extensive operation, decides the outcome. Handled by an experienced hepatobiliary surgeon, even a late or unexpected diagnosis can still be managed with a clear, structured plan.

Frequently Asked Questions

Why is gallbladder cancer found so late?

Early symptoms mimic gallstones and the gallbladder sits hidden, so cancer goes unnoticed.

Can gallbladder cancer be found by accident?

Yes. Many cases are found incidentally after gallbladder removal for suspected gallstones.

Do gallstones raise gallbladder cancer risk?

Yes. Long standing gallstones and chronic inflammation are major risk factors for it.

What are late symptoms of gallbladder cancer?

Jaundice, persistent right upper abdominal pain, weight loss and a palpable mass.

References

  1. Gallbladder carcinoma diagnostic challenge — National Library of Medicine
  2. Incidental gallbladder carcinoma after cholecystectomy — National Library of Medicine

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Call Now Button