
This website is being reviewed and updated in line with the National Medical Commission (NMC) guidelines on ethical advertising and public communication by registered medical practitioners.
support@macsclinic.com
+91 9482202240
VATS vs RATS vs Open Thoracotomy: What Are the Differences?

VATS vs RATS vs Open Thoracotomy: What Are the Differences?

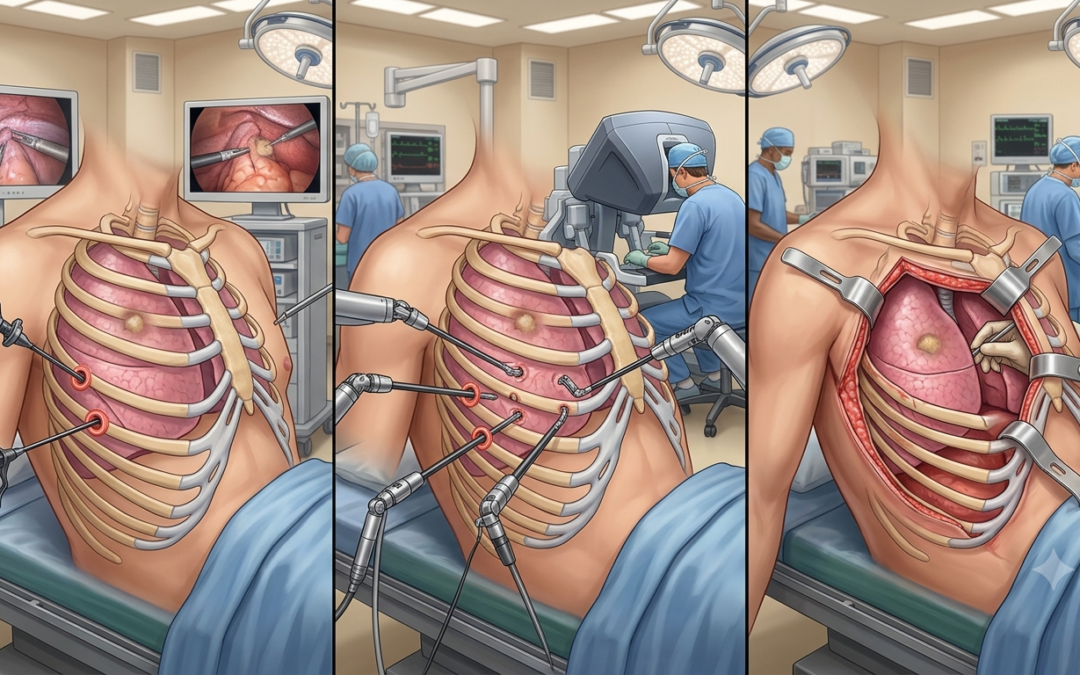
The three approaches differ mainly in the size of the cut and in how the surgeon sees and works inside the chest. Open thoracotomy uses one larger incision. VATS uses small cuts, a camera and long instruments, and RATS adds a robotic console with a three dimensional view. All three are used for lung cancer resections, including lobectomy. The right choice depends on the tumour, the patient’s health and the team’s experience.

According to Dr. Sandeep Nayak, a surgical oncologist in India, the choice between VATS vs RATS and open thoracotomy for lung cancer surgery depends on the tumour. “The approach is chosen to suit the tumour. Each one can remove a lung cancer completely when it is used in the right patient. Smaller cuts usually mean less pain and a quicker recovery. Some tumours still need an open operation to be removed safely. The route is only a means to the goal, and the goal is complete removal 

For information about lung surgery options, you can contact the clinic at +91 9482202240.

What Are Open Thoracotomy, VATS and RATS?

All three reach the lung through the chest wall, but the access and the tools differ.

Open thoracotomy: One larger incision between the ribs, with the ribs spread for access. The surgeon works looking directly at the lung.

VATS: A few small cuts between the ribs. A camera and long instruments are used, and the surgeon works from a screen. The full name is video-assisted thoracoscopic surgery.

RATS: Small cuts again, this time with a robotic console. The surgeon controls the instruments from the console and sees a magnified three dimensional view. The instruments bend and rotate more freely than straight VATS tools.

What they can treat: All three can be used for lobectomy, segmentectomy and wedge resection, depending on the tumour.

The same operation by a different route: In principle the tumour and the lymph nodes are removed in each case. Only the way in changes. Our page on lung cancer treatment covers the operations used.

How Do the Three Approaches Compare?

The table sets out the main differences side by side.

Feature

Open thoracotomy

VATS

RATS

Incision

One larger incision

A few small incisions

A few small incisions

View

Direct view

Camera view on a screen

Magnified three dimensional view

Instruments

Handheld

Long handheld instruments

Robotic arms with bending wrists

Pain and recovery

More pain, slower recovery

Less pain, quicker recovery than open surgery

Similar to VATS

Lymph nodes removed

Standard

Standard

Slightly more in some studies

VATS vs open: Trials found less pain and better quality of life after VATS, and long term survival wasn’t significantly different. Our blog on VATS surgery for lung cancer explains how it works.

RATS vs VATS: A pooled analysis of randomised trials found equivalent cancer and complication outcomes. RATS showed less blood loss and more lymph nodes removed, but that hasn’t translated into better survival.

Cost: Robotic systems generally cost more to buy and run, so RATS usually costs more.

Switching during surgery: Any keyhole operation can be changed to open surgery if it isn’t safe to continue. It’s a safety step, not a failure.

What Determines Treatment Choice?

The choice is made case by case, using a few clear points.

Tumour size and position: Small tumours away from the main blood vessels suit keyhole surgery. Large tumours, or those close to the main vessels or airway, can make open surgery safer.

Spread: Tumours growing into the chest wall or nearby structures, or heavily involved lymph nodes, may need an open operation.

Earlier chest surgery or infection: Heavy scarring inside the chest can make keyhole access difficult.

Lung function and general health: Fitness for anaesthesia and surgery shapes how much lung can be removed and by which route. Our blog on whether lung cancer surgery removes the whole lung explains how much may come out.

Team experience and availability: Results depend on how often the team performs the chosen approach. Robotic surgery is available only at some centres.

Key Takeaways

  • Open thoracotomy uses one larger incision. VATS and RATS use small cuts with a camera, and RATS adds a robotic console.
  • Compared with open surgery, VATS usually means less pain and a quicker recovery, without worse cancer outcomes in suitable patients.
  • Pooled randomised trials found RATS and VATS to be equivalent for cancer and complication outcomes, and RATS usually costs more.
  • Some tumours still need open surgery. The right approach depends on the tumour, the patient’s health and the team’s experience, and is best discussed with a specialist.

Frequently Asked Questions

What is the main difference between VATS and RATS?

RATS uses a robotic console with a three dimensional view. VATS uses handheld instruments.

Is VATS as effective as open surgery for lung cancer?

Trials show similar cancer outcomes in suitable patients, with less pain and quicker recovery.

Does robotic surgery give better results than VATS?

Not clearly. Pooled randomised trials found equivalent cancer outcomes and complication rates.

When is open thoracotomy still needed?

For some large, central or advanced tumours, or when keyhole surgery isn’t safe.

References


  1. PubMed — Long-term survival from a randomized controlled trial of lobectomy by video-assisted thoracoscopic surgery versus thoracotomy for early-stage lung cancer: https://pubmed.ncbi.nlm.nih.gov/39873729/
  2. National Center for Biotechnology Information — Robotic vs. video-assisted thoracoscopic surgery for resectable non-small cell lung cancer: a systematic review and meta-analysis of randomized controlled trials: https://pmc.ncbi.nlm.nih.gov/articles/PMC13460117/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Lobectomy vs Segmentectomy vs Wedge Resection for Lung Cancer: How the Surgical Options Differ

Lobectomy vs Segmentectomy vs Wedge Resection for Lung Cancer: How the Surgical Options Differ

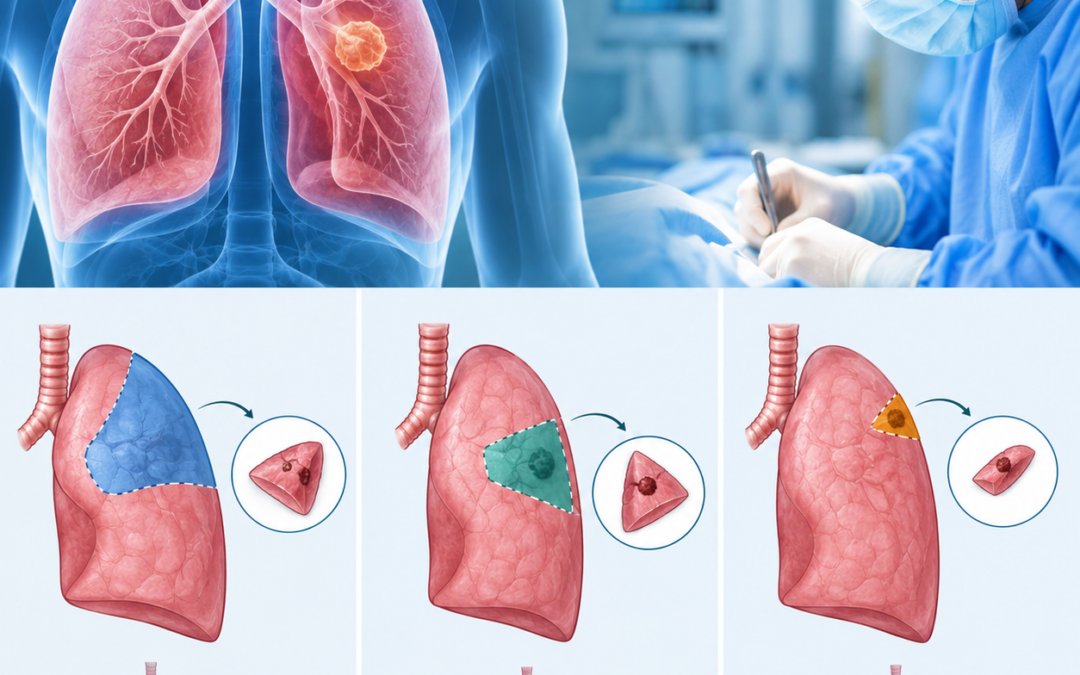
Most people hear “lung cancer surgery” and picture one operation. There are really three common ones, and what separates them is simple: how much lung leaves the body. A lobectomy takes a whole lobe. A segmentectomy takes a smaller piece of a lobe, a self-contained section with its own airway and blood supply. A wedge resection takes a small chunk around the tumour and doesn’t follow any of the lung’s natural lines.

Dr. Sandeep Nayak, a surgical oncologist in India, puts it this way: the operation should be cut to fit the tumour and the lungs, not the other way round. He won’t suggest a plan until the scans, the lymph node findings and the breathing tests are all on the table together.”

Confused by your scan or biopsy report? Call  Clinic on +91 9482202240.

What Lobectomy, Segmentectomy and Wedge Resection Remove?

When the cancer hasn’t left the lung, surgery is usually the first option on the table in lung cancer treatment. Think of the lung as a tree. A lobectomy takes off a whole major branch. A segmentectomy prunes a smaller limb at the point where it joins. A wedge resection just cuts out the damaged part without worrying about where the branches split.

A lobectomy is the long-standing standard. The right lung has three lobes and the left has two, and the surgeon removes the one that holds the tumour. It’s the biggest of the three, and for years it was the default for any operable early cancer.

A segmentectomy is trickier to perform. The surgeon has to find that segment’s own bronchus, artery and vein, divide them one by one, and lift the segment out cleanly. The reward is that more healthy lung stays behind.

A wedge resection is the quickest and smallest. A stapling device cuts a wedge out and seals the edge as it goes. The catch is that nothing guarantees a generous rim of healthy tissue, so it depends heavily on where the tumour sits.

In all three, nearby lymph nodes are usually sampled or removed. What they show can change what happens next, so the surgeon doesn’t skip them.

And the technique is a separate question from the extent. Open surgery, VATS keyhole surgery or a robot can be used for any of the three.

Lobectomy vs Segmentectomy: What Guides the Choice?

Picture a typical case. A patient in their sixties has a 1.5 cm nodule near the outer edge of one lung, the lymph nodes look clear, and breathing tests are on the weak side after years of smoking. For that person, a segmentectomy often makes more sense than a lobectomy. Change one detail, say the nodule is 3.5 cm and close to the main airway, and the answer flips.

So what actually tips the decision?

Size and position matter most. Small tumours of around 2 cm or less in the outer lung are the best candidates for a smaller operation. Large ones, or ones near the centre of the chest, usually aren’t.

Lymph nodes come next. If they look involved on a scan, or turn out to be involved during surgery, the surgeon will often move to a lobectomy and clear the nodes more thoroughly.

The look of the tumour on CT counts too. A hazy “ground glass” appearance often means slow growth, which can justify taking less lung.

Then there’s the patient. Weak breathing reserve, heart trouble or other illness can make a smaller operation the safer choice, even when a lobectomy would otherwise be on the cards.

The research backs this up for carefully chosen cases. A large randomised trial looked at tumours up to 2 cm in the outer lung with clear nodes, and patients who had a smaller resection did about as well on disease-free survival as those who had a lobectomy.

Whether surgery can cure the cancer at all depends on stage, which our guide on whether lung cancer can be cured explains.

Where Wedge Resection Fits and What to Expect After Surgery?

How you recover depends on two things: how much lung came out, and how it was done. Robotic surgery and other keyhole methods mean smaller cuts and usually an easier few weeks than an open chest operation.

Wedge resection has a narrow but real role. It works for very small nodules near the edge of the lung, for cases where the surgeon needs tissue to confirm what the nodule actually is, and for patients too frail for anything bigger.

The margin is the whole story here. Take less tissue and you need a clear rim of healthy lung around the tumour. If that rim comes back too thin, the surgeon may extend the operation to a segmentectomy or lobectomy on the spot, which is why you’ll be asked to consent to that possibility beforehand.

When researchers went back to the data from the same North American trial, wedge resection came out worse on survival than either segmentectomy or lobectomy. The two bigger operations weren’t meaningfully different from each other. That’s a big reason surgeons lean toward segmentectomy over a wedge when a smaller operation is on the table and the patient can handle it.

Key Takeaways

  • Lobectomy takes a whole lobe, segmentectomy takes one defined section of it, and wedge resection cuts out a small piece without following the lung’s structure.
  • Size, position, lymph nodes and breathing ability do most of the work when choosing between lobectomy vs segmentectomy.
  • For small tumours in the outer lung with clear nodes, smaller operations have held up well in trials.
  • Wedge resection is only as good as its margin, so it’s reserved for carefully chosen patients.
  • No one decides this from a single scan. The oncology team looks at the scans, the biopsy and the breathing tests together.

Frequently Asked Questions

Is segmentectomy as effective as lobectomy for lung cancer?

For the right patient, yes. That means a small tumour in the outer lung with clear lymph nodes. Outside that group, lobectomy is still usually the safer bet.

When is wedge resection used for lung cancer?

Mostly for very small nodules near the edge of the lung, or when a bigger operation simply wouldn’t be safe for the patient.

Does segmentectomy also remove lymph nodes?

Usually it does. The surgeon samples or removes the nearby nodes during the operation, since what they show helps decide the next step.

Can the planned lung surgery change during the operation?

It can. If the margin turns out too close, or the nodes look involved once the surgeon is inside, the operation may be extended. You’ll normally discuss this before you go in.

References


  1. NHS. Treatment for lung cancer (NHS Health A to Z). https://www.nhs.uk/conditions/lung-cancer/treatment
  2. Altorki N, Wang X, Kozono D, et al. Lobar or Sublobar Resection for Peripheral Stage IA Non-Small-Cell Lung Cancer. N Engl J Med. 2023;388(6):489-498. https://pubmed.ncbi.nlm.nih.gov/36780674/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Oral Cancer: Should Treatment Start with Surgery or Radiation?

Oral Cancer: Should Treatment Start with Surgery or Radiation?

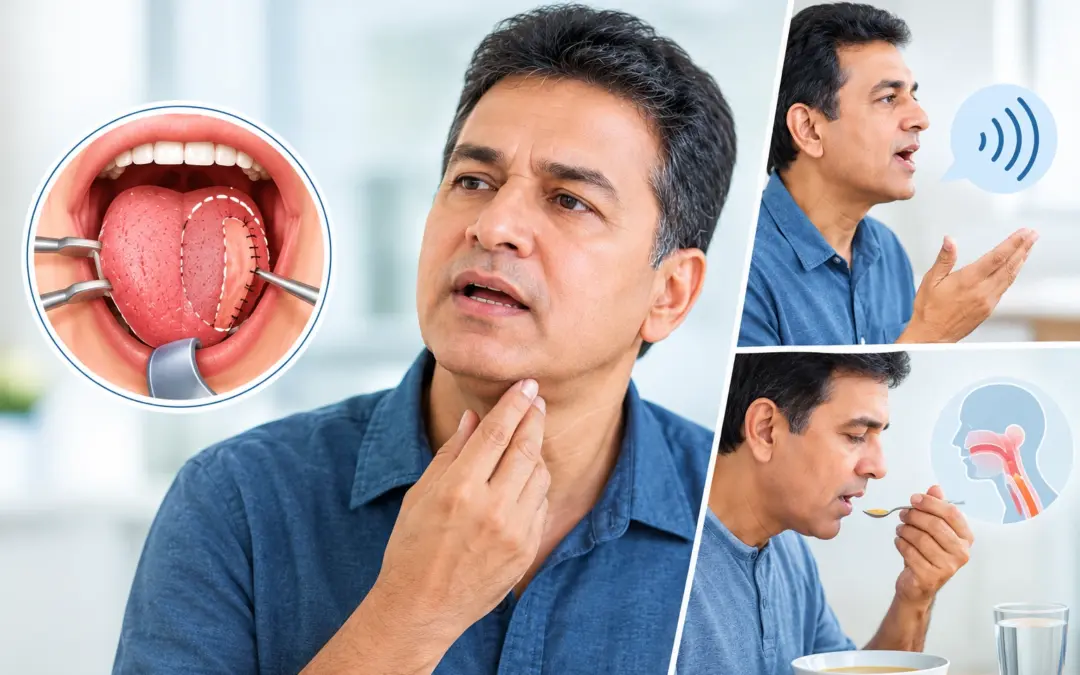
Surgery is the first and main treatment for most oral cavity cancers, including cancer of the tongue. Radiation usually comes later, after the operation, if the pathology report points to a higher risk, and it takes the lead only when surgery isn’t an option. Speech and swallowing are affected because the tongue is central to both. How much changes depends on how much of it is removed, which part, and whether it’s rebuilt.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, talks patients through what to expect after a glossectomy. “The first question I get before tongue surgery is almost always the same: will I be able to talk and eat afterwards? With a small tumour, usually yes, with only a mild and brief change. If a bigger part has to go, the road is longer and rehab matters a lot. We plan the surgery and the recovery together.”


If you’d like to know more about tongue cancer surgery, call the clinic on +91 9482202240.

How Much of the Tongue Is Removed in Tongue Cancer Surgery?

That depends on the tumour: how big it is, how deep, and where it sits. The surgeon takes the cancer plus a small rim of healthy tissue around it, and tries not to take more than that.

Partial glossectomy: Most people with a small tumour on the side of the tongue need only this. A piece comes out and the rest of the tongue stays. Some of these small tumours can be reached through the mouth with robotic help, and our page on trans oral robotic surgery covers where that’s used.

Hemiglossectomy: Half the tongue. This is for larger or deeper tumours.

Total glossectomy: The whole tongue, or nearly all of it. Rare, and kept for advanced cancers.

The neck: Tongue cancer often spreads to the lymph nodes in the neck, so the surgeon usually clears those during the same operation.

Rebuilding: If a big part is taken, skin and tissue from the forearm or thigh can be used to build the tongue back up.

How Does Tongue Cancer Surgery Affect Speech?

Almost every sound you make involves the tongue. So yes, speech changes. How much is the real question.

Small removals: Many people notice very little. Some are a bit slurred for a short while, and then it settles.

Bigger removals: Clarity can drop. Sounds like t, d, l and s need the tip of the tongue to touch the roof of the mouth, so those suffer first.

Straight after surgery: Swelling makes everyone sound muffled for the first few days. It passes.

A rebuilt tongue: The tissue used to rebuild it gives the tongue enough bulk to reach the palate, and that helps with clearer sounds.

Speech therapy: This starts early. Exercises, practice, patience. Over weeks and months most people get clearer, even if it doesn’t sound exactly as it once did. Speech is a large part of head and neck cancer care, and our page on head and neck cancer treatment covers that.

What Determines Speech and Swallowing Outcomes After Tongue Cancer Surgery?

No two people recover alike. These are the things that shape it.

How big the tumour was: The more tongue that has to come out, the bigger the change.

Where it was: The tip and front mostly change how clearly you speak. The back mostly changes swallowing.

Whether it was rebuilt: And how.

Radiation afterwards: If you need it, it can leave you with a dry mouth and some stiffness, and that makes both speaking and swallowing harder.

The neck operation: In suitable cases, Dr. Nayak’s RIA-MIND approach to neck dissection is designed to cut complications and help function. You can read more on our expertise page.

Rehab: Early therapy and daily practice at home count for a great deal, and they’re as much your job as the surgeon’s.

Where you started from: Your age, your general health, and how you were speaking and eating before.

Key Takeaways

  • The tongue plays a vital role in both speech and swallowing, so surgery can affect these functions.

  • Smaller tissue removals usually cause milder changes, while larger surgeries may require longer recovery and therapy.

  • Surgical planning, reconstruction and rehabilitation help improve speech and swallowing after surgery.

  • Ask your care team what to expect based on your tumour and planned surgery.

  • To discuss your treatment options, book an appointment or call the clinic at +91 9482202240.

Frequently Asked Questions

How does tongue cancer surgery affect speech?

A small removal often changes little, while a bigger one can leave speech less clear for a time.

Can you swallow normally after tongue cancer surgery?

Many people do, though after bigger surgery you may need therapy and softer food at first.

Do you need speech therapy after a glossectomy?

Often, especially after bigger removals, and the earlier it starts the better.

Will I need a feeding tube after tongue cancer surgery?

Sometimes, briefly, after larger operations while the mouth heals.

References


National Cancer Institute (NCI) – Head and Neck Cancers: Side Effects and Rehabilitation https://www.cancer.gov/types/head-and-neck/head-neck-fact-sheet

 PubMed – Voice Rehabilitation After Tongue Cancer Surgery: A Cohort Study in Indian Population https://pubmed.ncbi.nlm.nih.gov/39559020/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Does Minimally Invasive Cancer Surgery Give the Same Cure Rate as Open Surgery?

Does Minimally Invasive Cancer Surgery Give the Same Cure Rate as Open Surgery?

For most common cancers, minimally invasive surgery cures about as many patients as open surgery does. In colon and rectal cancer, laparoscopic vs open cancer surgery studies show the same survival and recurrence, and patients go home sooner with less pain. Early cervical cancer is the exception. Open radical hysterectomy gave better survival there. So the cancer type, its stage and the surgeon’s experience all matter.

Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, explains how minimally invasive oncology and open surgery are weighed against each other. “Keyhole and robotic surgery suit many cancers. For some, open surgery is still the better operation. Newer doesn’t mean better. What counts is which approach clears that cancer best at that stage. Where results are equal, the gentler approach is usually chosen. Where they aren’t, the better approach is used.” 

For information about keyhole and open surgery options for cancer, you can contact the clinic at +91 9482202240.

Where Is Minimally Invasive Surgery as Effective as Open Surgery?

For several common cancers, large studies show the two approaches control cancer equally well.

Colon and rectal cancer: Pooled reviews find no significant difference in disease free survival, local recurrence or spread. Short term recovery is better after laparoscopic and robotic surgery.

Surgeon experience: Equal results come from experienced teams. Both laparoscopic and robotic surgery have a steep learning curve, so volume matters.

Recovery: Smaller cuts mean less blood loss, less pain, fewer wound problems and a shorter hospital stay.

Complicated cases: Open surgery is still preferred when the colon is perforated, blocked or bleeding.

Case by case: Which cancers suit the keyhole route is worked out case by case. Our page on laparoscopic cancer surgery covers where it’s used.

When Is Open Surgery Still the Better Choice?

Equal results can’t be assumed for every cancer. Early cervical cancer is the clearest example.

Early cervical cancer: In the LACC trial, disease free survival at 4.5 years was 86.0% after minimally invasive radical hysterectomy and 96.5% after open surgery. Overall survival was lower too.

What changed afterwards: Open radical hysterectomy is now widely recommended for early stage cervical cancer.

Difficult tumours: Very bulky tumours, or those pressing on nearby organs, can make an open operation the safer one.

Switching mid operation: A surgeon may convert from keyhole to open if it isn’t safe to continue. That’s sound judgment, not a failed operation.

Further reading: For a wider overview of how these operations are done, see our blog on minimally invasive cancer surgery in India.

What Determines Treatment Choice?

The choice is made case by case, using a few clear points.

Stage of the cancer: The stage shapes how much has to be removed, and that decides which approach can do it safely. Our blog on cancer staging and how it determines surgery explains this.

Earlier operations: Scar tissue from previous surgery can make keyhole surgery harder. Sometimes open surgery is the safer route.

General health: Fitness for anaesthesia and a long operation affects which approach is safe.

Team review: Surgical, medical and radiation oncologists often review the case together before the plan is set.

The patient’s priorities: Once the options are explained, recovery time and scars are part of the decision too.

Key Takeaways

  • Minimally invasive surgery gives comparable cure rates to open surgery for many common cancers, such as colon and rectal cancer.
  • Early cervical cancer is the main exception, where open surgery gave better survival.
  • The right approach depends on the cancer, its stage and the surgeon’s experience, so it’s worth asking which option the evidence supports for your case.

To discuss your case, you can contact the clinic at +91 9482202240.

Frequently Asked Questions

Which cancer does better with open surgery?

Early cervical cancer. Open radical hysterectomy gave better survival in the LACC trial.

Does minimally invasive surgery cure cancer as well as open surgery?

For many cancers, yes, with comparable survival. Cervical cancer is a key exception.

Is robotic surgery better than laparoscopic for cure rates?

Cancer outcomes look similar. Robotic surgery may lower the need to convert to open.

What do patients gain from minimally invasive cancer surgery?

Less blood loss, less pain, fewer wound problems and a shorter hospital stay.

References

  1. National Center for Biotechnology Information — Comparing the Perioperative and Oncological Outcomes of Open Versus Minimally Invasive Inguinal Lymphadenectomy in Penile Cancer: A Systematic Review and Meta-Analysis: https://pmc.ncbi.nlm.nih.gov/articles/PMC12468625/
  2. National Center for Biotechnology Information — Video Endoscopic Inguinal Lymphadenectomy for Radical Management of Inguinal Nodes in Patients With Penile Squamous Cell Carcinoma: https://pmc.ncbi.nlm.nih.gov/articles/PMC4944619/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Hemithyroidectomy vs Total Thyroidectomy for Papillary Thyroid Cancer

Hemithyroidectomy vs Total Thyroidectomy for Papillary Thyroid Cancer

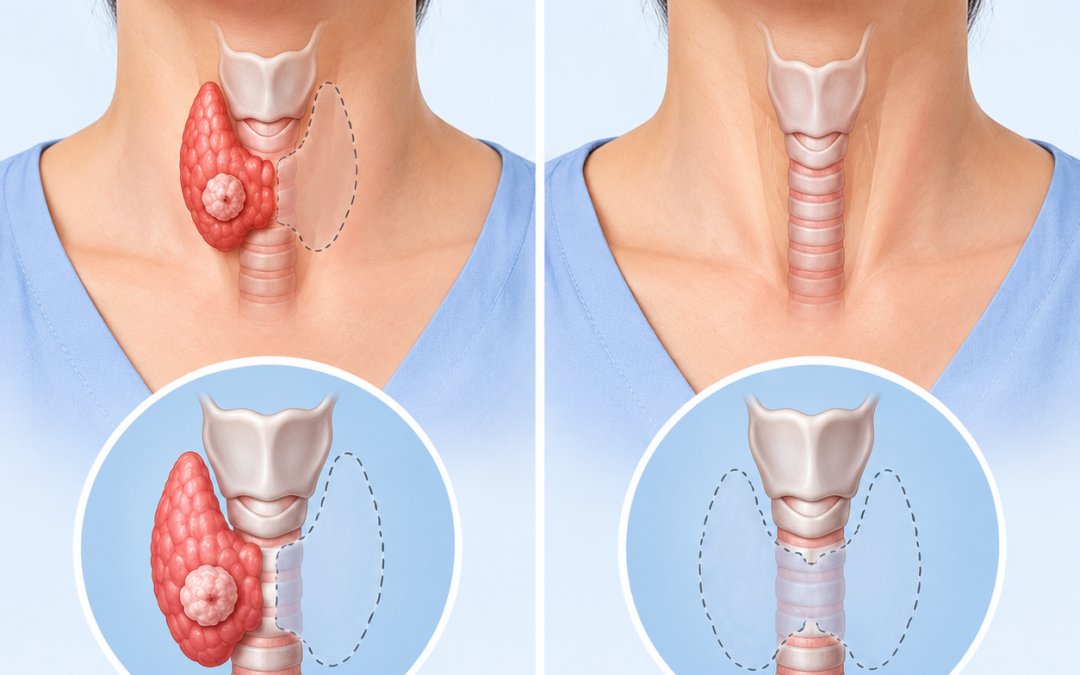
Which operation is needed depends mainly on the size of the tumour, the risk level and whether it has spread. Hemithyroidectomy removes one lobe of the thyroid, and total thyroidectomy removes the whole gland. Small, low risk papillary thyroid cancers often need only the lobe with the tumour. Larger tumours, spread beyond the thyroid or involved lymph nodes usually call for total thyroidectomy. The final advice is made case by case.

Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, explains how the extent of thyroidectomy is decided for papillary thyroid cancer. “The operation is matched to the cancer. Tumour size, spread beyond the thyroid and lymph node findings guide the extent of surgery. A smaller operation suits some low risk tumours. A larger one suits others. Neither is the better choice in every case.”

For information about keyhole and open surgery options for cancer, you can contact the clinic at +91 9482202240.

What Is the Difference Between Hemithyroidectomy and Total Thyroidectomy?

Both remove thyroid tissue. What differs is how much, and what follows.

Hemithyroidectomy: One lobe, and sometimes the narrow bridge of tissue joining the lobes, is removed. The other lobe stays and often keeps making enough thyroid hormone.

Total thyroidectomy: The whole gland is removed. Daily thyroid hormone tablets are needed for life afterwards.

Radioactive iodine: This treatment is given after total thyroidectomy when it’s needed. It generally isn’t given after hemithyroidectomy alone.

Second operation: If the final pathology report shows higher risk features, the other lobe may be removed in a second operation, called completion thyroidectomy. For low risk findings it’s not always needed.

Risks: Low calcium and voice changes are more likely after total thyroidectomy than after removing one lobe. These risks are part of the planning. Our page on thyroid cancer treatment covers the options.

How Do the Two Operations Compare?

The table sets out the main differences side by side.

Feature

Hemithyroidectomy

Total thyroidectomy

Thyroid removed

One lobe, sometimes with the isthmus

The whole gland

Usually considered for

Small, low risk tumours confined to the thyroid, with no node spread

Larger tumours, spread beyond the thyroid, involved nodes or tumours in both lobes

Thyroid hormone tablets afterwards

Sometimes

Always

Radioactive iodine afterwards

Generally not given

Can be given when needed

Risk of low calcium and voice changes

Lower

Higher

Under 1 cm: For a small tumour confined to the thyroid, with no node spread, guidelines advise removing one lobe unless there’s a clear reason to remove both.

Between 1 and 4 cm: Either operation can be appropriate when the tumour hasn’t spread beyond the thyroid and no nodes are involved. Other risk factors and patient preference decide the choice.

Over 4 cm, or spread: A tumour over 4 cm, visible spread beyond the thyroid, involved lymph nodes or distant spread usually means total thyroidectomy.

Evidence: Studies of carefully selected low risk patients found limited surgery to be an equivalent strategy. Our blog on whether thyroid cancer is curable with surgery covers the outlook after treatment.

What Determines the Extent of Thyroid Surgery?

Several findings are weighed together before one operation is advised.

Tumour size and extent: Size, and whether the tumour has grown beyond the thyroid, are the main starting points.

Lymph nodes: Nodes that look involved on ultrasound or scans point toward total thyroidectomy.

Both lobes: Papillary cancer is often present in more than one spot. Tumours in both lobes, or nodules in the other lobe, make removing the whole gland more likely.

Other risk factors: Earlier radiation to the head or neck, a family history of thyroid cancer, or concerning findings on final pathology can change the advice. Patient preference counts too.

Surgical route: Robotic vs open thyroidectomy is a separate choice from the extent of surgery. Either route can be used for a lobe or the whole gland. Robotic surgery uses remote access, may take longer and suits selected patients. Our blog on robotic thyroidectomy covers this route.

Key Takeaways

  • Hemithyroidectomy removes one lobe, and total thyroidectomy removes the whole gland.
  • Small, low risk papillary thyroid cancers often need only the lobe with the tumour. Larger tumours, spread beyond the thyroid or involved nodes usually need total thyroidectomy.
  • Total thyroidectomy needs lifelong thyroid hormone tablets and allows radioactive iodine when it’s needed.
  • The right operation depends on the individual case, so it’s worth discussing the options with a specialist.

Frequently Asked Questions

Is hemithyroidectomy enough for papillary thyroid cancer?

Sometimes. It can be enough for small, low risk tumours confined to the thyroid.

When is total thyroidectomy advised for papillary thyroid cancer?

For tumours over 4 cm, spread beyond the thyroid, or involved lymph nodes.

Will I need thyroid hormone tablets after hemithyroidectomy?

Some people do. After total thyroidectomy, tablets are always needed.

Can a second operation be needed after hemithyroidectomy?

Yes, if final pathology shows higher risk features, the other lobe may be removed.

References


  1. National Center for Biotechnology Information — 2015 American Thyroid Association Management Guidelines for Adult Patients with Thyroid Nodules and Differentiated Thyroid Cancer: https://pmc.ncbi.nlm.nih.gov/articles/PMC4739132/
  2. National Center for Biotechnology Information — New Recommendations for Extent of Thyroidectomy and Active Surveillance for the Treatment of Differentiated Thyroid Cancer: https://pmc.ncbi.nlm.nih.gov/articles/PMC5538727/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Robotic vs Endoscopic vs Open Thyroidectomy: What’s the Difference?

Robotic vs Endoscopic vs Open Thyroidectomy: What’s the Difference?

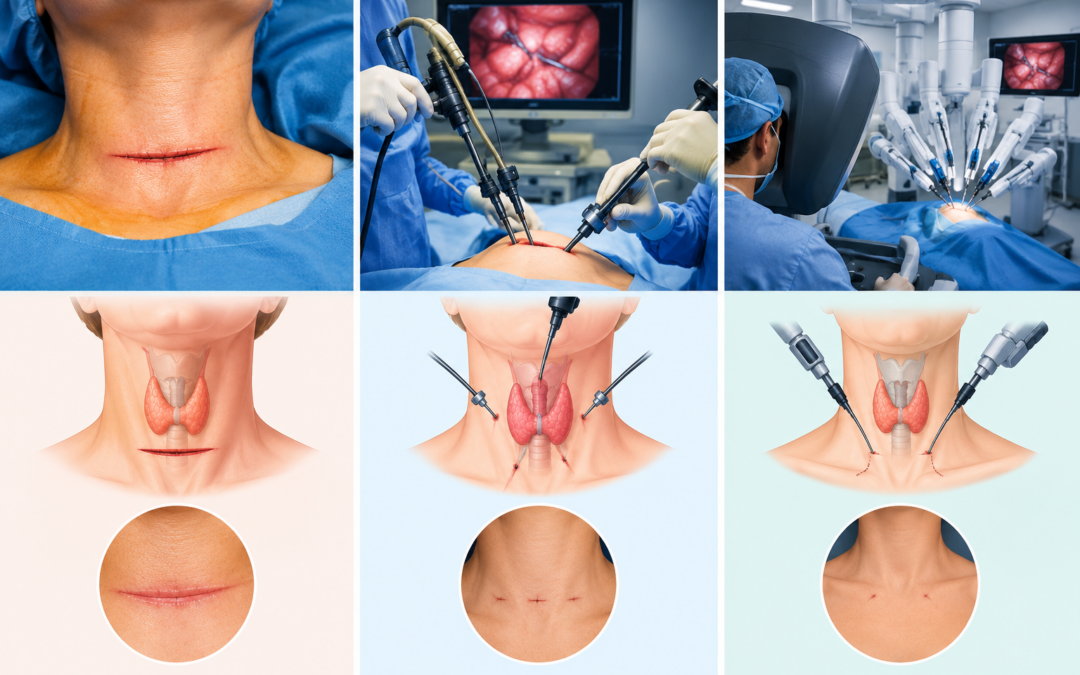
All three remove the thyroid, either part of it or the whole gland. What changes is how the surgeon gets in, what they see while working, and how they move the instruments. Open surgery goes through a cut on the front of the neck. Endoscopic and robotic thyroid surgery reach the gland from somewhere else, like the armpit, the breast or the mouth, so the neck stays clear of a scar.

Prof. Dr. Sandeep Nayak, surgical oncologist in Bangalore with over 24 years of experience, says it’s less about which one is “best” and more about which one fits the person on the table: “Patients usually walk in having already picked a favourite, mostly based on the scar. The scar matters, and I take it seriously. But tumour size, the thyroid itself, and what the neck looks like on imaging have to lead to the decision, and the technique follows from that.”

Not sure which thyroid surgery suits your case?

Which Approach Suits Which Patient?

There’s no single winner here. A few things usually push the decision one way or the other:

  • A larger tumour, or one that has spread to nearby tissue, often points toward open surgery
  • Suspicious lymph nodes in the neck can make open access the safer route
  • A small, well-contained nodule is where robotic thyroid surgery tends to work best
  • Someone who is very concerned about a visible neck scar may lean toward a remote access approach
  • A very large thyroid gland can make remote access harder to do safely
  • Budget and hospital availability matter too, and it’s fair to bring them up in the consultation

Whichever way it goes, cure comes first and cosmetic outcome second. If you’d like to understand how surgery fits into the bigger picture of thyroid cancer care, our post on whether thyroid cancer is curable with surgery is a good place to start.

How Do the Three Types of Thyroidectomy Compare?

Here’s the side by side view of the thyroidectomy types, so you can see where they actually differ.

Feature

Open Thyroidectomy

Endoscopic Thyroidectomy

Robotic Thyroidectomy

Incision and access

Direct cut on the front of the neck

Remote access through the armpit, breast or mouth

Remote access through the armpit, breast or face and mouth, using a console

View

Direct view with the naked eye or surgical loupes

2D video monitor

High definition 3D magnified view

Instruments

Standard handheld tools

Rigid, straight endoscopic tools

Robotic wrists that bend and rotate, with tremor filtering

Operative time

Shortest, usually 1 to 2 hours

Longer, since handling is more restricted

Longest, often 2 to 3 hours or more

Cost

Lowest

Moderate

Highest, because of the system setup and upkeep

Neck scar

Yes, on the front of the neck

No

No

The extra operating time with remote approaches isn’t a flaw. It’s the price of working through a small, hidden entry point. If you want to see how these options fit into a full treatment plan, our thyroid cancer treatment page walks through them.

What Should You Ask Before Choosing a Thyroid Surgery?

What Should You Ask Before Choosing a Thyroid Surgery?

Most people only think of these questions after the decision is made, so it helps to have them ready beforehand. Dr. Nayak’s own technique, RABIT, goes in through the breast and armpit and has been used for removing thyroid tumours under about 4 cm, which is exactly the kind of detail worth asking any surgeon about their own method.

  • Do my tumour size and scan findings actually allow a remote approach, or is open surgery the safer fit?
  • How many of these specific surgeries do you do in a year? Volume matters more than the title here.
  • Under what circumstances would you switch to open surgery during the operation?
  • How long is the usual hospital stay, and what should the neck and shoulder feel like in the first few weeks?
  • When are the follow-up scans and blood tests, and who explains the results?
  • What is the total cost, including the facility, and what might change it?

What Determines the Choice of Thyroid Surgery?

The choice between open, endoscopic and robotic thyroidectomy depends on the patient’s diagnosis, tumour size, thyroid anatomy and imaging findings. The extent of the disease and whether nearby lymph nodes are involved may also influence the surgical approach. Other considerations include the feasibility of each technique, potential risks, recovery expectations and cost. The final decision should be made after discussing the available options with the treating surgeon, prioritising appropriate cancer treatment and patient safety.

Frequently Asked Questions

What's the main difference between selective and modified radical neck dissection?

Selective dissection removes specific node levels, modified radical clears all five with structures spared.

Is shoulder dysfunction the same after both procedures?

No, shoulder dysfunction is more common and more severe after modified radical dissection.

What decides which type of neck dissection a patient needs?

Tumour location, nodal involvement on imaging, and disease extent decide which one applies.

Does modified radical dissection work as well as classical radical dissection?

Yes, studies show comparable oncological outcomes between modified radical and classical radical dissection.

References

  1. National Center for Biotechnology Information — Shoulder Dysfunction and Quality of Life Following Modified Radical and Selective Neck Dissection: A Prospective Comparative Study: https://pmc.ncbi.nlm.nih.gov/articles/PMC11306493/
  2. National Center for Biotechnology Information — Impact of Modified Radical Neck Dissections on the Number of Retrieved Nodes, Recurrence and Survival: https://pmc.ncbi.nlm.nih.gov/articles/PMC9442232/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Call Now Button