
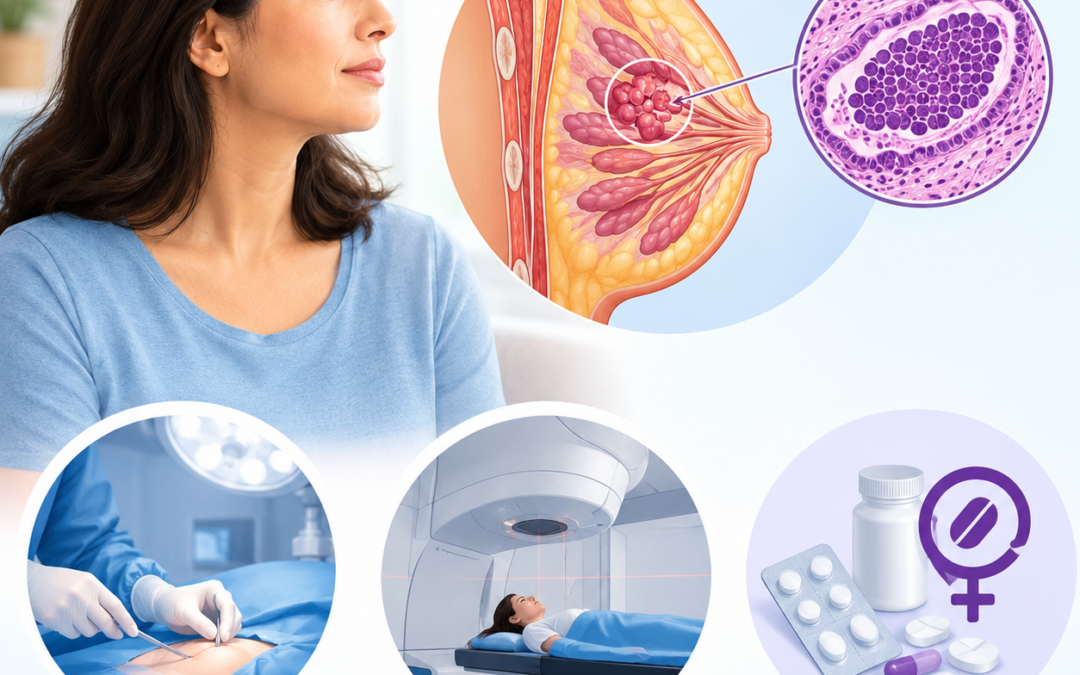
Surgery remains the standard and primary DCIS treatment, though it isn’t compulsory in every single situation.
Most patients are advised lumpectomy with radiation or a mastectomy, because DCIS can occasionally progress into invasive breast cancer.
For a carefully selected group with low-risk disease, clinical trials are now studying close monitoring instead of immediate surgery.
That approach is still being tested, so it isn’t yet a routine option outside a structured plan.
According to Prof. Dr. Sandeep Nayak, a surgical oncologist who guides patients through DCIS treatment decisions, “DCIS isn’t an emergency, but it isn’t something to ignore either. We can’t yet tell which cases will turn invasive and which will stay put. That’s why surgery stays the standard. Monitoring is a promising idea for the right patient, and it belongs in a proper study or a carefully supervised plan, not a casual decision.”
Diagnosed with DCIS and unsure whether surgery is your only route?
Why Is Surgery the Standard Treatment for DCIS?
DCIS sits inside the milk ducts and hasn’t spread into surrounding tissue. Even so, removal is the usual advice.
Unpredictable behaviour: There’s no reliable way yet to tell which DCIS will become invasive. Removing it takes the guesswork out.
Lumpectomy with radiation: The area is removed with a margin of healthy tissue, and radiation afterward roughly halves the chance of local recurrence.
Mastectomy: Advised when DCIS is widespread, sits in more than one area, or is large for the size of the breast. Radiation usually isn’t needed after it.
Hormone therapy: If the DCIS is hormone receptor positive, tamoxifen or an aromatase inhibitor may follow surgery to lower the risk of it returning.
Which route fits depends on how far the DCIS extends on imaging and what the biopsy shows. Our page on breast cancer treatment explains how that assessment is made.
Can Some Patients With DCIS Avoid Surgery?
In a small, selected group, possibly. The evidence is still building.
Active monitoring: Regular mammograms and clinical exams in place of an immediate operation. This is being tested in the COMET, LORIS, LORD and LORETTA trials.
Who qualifies: Low risk disease only. Low or intermediate grade, found on screening, no sign of invasion, and usually hormone receptor positive in a woman over 40.
What early results show: In COMET, women who chose monitoring didn’t have more invasive cancer at two years. Longer follow up is still awaited.
Why caution remains: A biopsy can miss a hidden invasive area. In some studies, a minority of women who looked suitable for monitoring had invasive cancer found at surgery.
Drug treatment is a related question for hormone positive disease. Our blog on hormone therapy vs surgery in HR positive breast cancer covers where each one fits.
Why Choose Prof. Dr. Sandeep Nayak for DCIS Treatment in Bangalore?
Prof. Dr. Sandeep Nayak has over 24 years in surgical oncology, with deep experience in breast cancer surgery, both breast conserving and mastectomy. DNB in Surgical Oncology and General Surgery. MRCS from the UK. A fellowship in Laparoscopic and Robotic Onco Surgery too. He chairs Oncology Services across Karnataka and serves as Executive Director of Surgical Oncology and Robotic Surgery at KIMS Hospital, Bangalore. Every case is reviewed at the tumour board, where imaging, biopsy grade and receptor status are weighed together before a plan is set.
DCIS decisions are rarely one size fits all. The extent on imaging, the grade and the patient’s own priorities all shape the advice. Call +91 9482202240 to book your consultation.
Frequently Asked Questions
Is surgery always required for DCIS?
Not always, but it’s the standard. Monitoring is studied only in selected low-risk cases.
Can DCIS turn into invasive cancer?
DCIS itself is non-invasive. Left untreated, some cases can progress to invasive cancer.
Is chemotherapy needed for DCIS?
Generally no. Treatment is surgery, sometimes with radiation or hormone therapy.
Who can be considered for active monitoring?
Selected low-risk patients, usually within clinical trials, with close imaging follow-up.
References
- National Center for Biotechnology Information — Ductal Carcinoma In Situ of the Breast: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3407624/
- National Center for Biotechnology Information — Active Monitoring With or Without Endocrine Therapy for Low-Risk Ductal Carcinoma In Situ: The COMET Randomized Clinical Trial: https://pmc.ncbi.nlm.nih.gov/articles/PMC11920841/
Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
