
This website is being reviewed and updated in line with the National Medical Commission (NMC) guidelines on ethical advertising and public communication by registered medical practitioners.
support@macsclinic.com
+91 9482202240
How Does Tongue Cancer Surgery Affect Speech and Swallowing?

How Does Tongue Cancer Surgery Affect Speech and Swallowing?

Surgery is the first and main treatment for most oral cavity cancers, including cancer of the tongue. Radiation usually comes later, after the operation, if the pathology report points to a higher risk, and it takes the lead only when surgery isn’t an option. Speech and swallowing are affected because the tongue is central to both. How much changes depends on how much of it is removed, which part, and whether it’s rebuilt.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, talks patients through what to expect after a glossectomy. “The first question I get before tongue surgery is almost always the same: will I be able to talk and eat afterwards? With a small tumour, usually yes, with only a mild and brief change. If a bigger part has to go, the road is longer and rehab matters a lot. We plan the surgery and the recovery together.

 If you’d like to know more about tongue cancer surgery

How Much of the Tongue Is Removed in Tongue Cancer Surgery?

That depends on the tumour: how big it is, how deep, and where it sits. The surgeon takes the cancer plus a small rim of healthy tissue around it, and tries not to take more than that.

Partial glossectomy: Most people with a small tumour on the side of the tongue need only this. A piece comes out and the rest of the tongue stays. Some of these small tumours can be reached through the mouth with robotic help, and our page on trans oral robotic surgery covers where that’s used.

Hemiglossectomy: Half the tongue. This is for larger or deeper tumours.

Total glossectomy: The whole tongue, or nearly all of it. Rare, and kept for advanced cancers.

The neck: Tongue cancer often spreads to the lymph nodes in the neck, so the surgeon usually clears those during the same operation.

Rebuilding: If a big part is taken, skin and tissue from the forearm or thigh can be used to build the tongue back up.

How Does Tongue Cancer Surgery Affect Speech?

Almost every sound you make involves the tongue. So yes, speech changes. How much is the real question.

Small removals: Many people notice very little. Some are a bit slurred for a short while, and then it settles.

Bigger removals: Clarity can drop. Sounds like t, d, l and s need the tip of the tongue to touch the roof of the mouth, so those suffer first.

Straight after surgery: Swelling makes everyone sound muffled for the first few days. It passes.

A rebuilt tongue: The tissue used to rebuild it gives the tongue enough bulk to reach the palate, and that helps with clearer sounds.

Speech therapy: This starts early. Exercises, practice, patience. Over weeks and months most people get clearer, even if it doesn’t sound exactly as it once did. Speech is a large part of head and neck cancer care, and our page on head and neck cancer treatment covers that.

How Does Tongue Cancer Surgery Affect Swallowing?

Swallowing begins in the mouth, with the tongue gathering food and pushing it back. When that part of the job changes, eating can get harder before it gets easier.

Moving food: It can feel awkward to gather food and send it to the back of the mouth.

Coughing: Food or drink sometimes goes down the wrong way, especially after bigger operations or when the back of the tongue is involved. The team keeps a close eye on this.

A feeding tube: After a larger operation, a tube may be used for a short time so you’re properly fed while you heal.

Easing back into food: Liquids first, then soft foods, then normal meals when you’re ready.

Swallowing therapy: A therapist teaches exercises and ways of swallowing that make it safer. A gentler operation can also make the early days easier, and our blog on whether minimally invasive cancer surgery gives the same cure rate as open surgery compares the approaches.

What Determines Speech and Swallowing Outcomes After Tongue Cancer Surgery?

No two people recover alike. These are the things that shape it.

How big the tumour was: The more tongue that has to come out, the bigger the change.

Where it was: The tip and front mostly change how clearly you speak. The back mostly changes swallowing.

Whether it was rebuilt: And how.

Radiation afterwards: If you need it, it can leave you with a dry mouth and some stiffness, and that makes both speaking and swallowing harder.

The neck operation: In suitable cases, Dr. Nayak’s RIA-MIND approach to neck dissection is designed to cut complications and help function. You can read more on our expertise page.

Rehab: Early therapy and daily practice at home count for a great deal, and they’re as much your job as the surgeon’s.

Where you started from: Your age, your general health, and how you were speaking and eating before.

Key Takeaways

  • The tongue does two big jobs, speaking and swallowing, so surgery on it affects both.
  • A small removal usually means a mild change that doesn’t last.
  • A bigger one takes more time and needs therapy.
  • Planning, rebuilding and rehab together decide how well things come back.
  • Before surgery, ask your team what to expect for your tumour.
  • If you’d like to talk it through, you can book an appointment or call the clinic on +91 9482202240.

Frequently Asked Questions

How does tongue cancer surgery affect speech?

A small removal often changes little, while a bigger one can leave speech less clear for a time.

Can you swallow normally after tongue cancer surgery?

Many people do, though after bigger surgery you may need therapy and softer food at first.

Do you need speech therapy after a glossectomy?

Often, especially after bigger removals, and the earlier it starts the better.

Will I need a feeding tube after tongue cancer surgery?

Sometimes, briefly, after larger operations while the mouth heals.

References

  1. Functional and quality of life outcomes after partial glossectomy: a multi-institutional longitudinal study of the Head and Neck Research Network (PMC, NIH)
    This study follows how speech, swallowing and quality of life change over the first year after tongue cancer surgery.
  2. Long-term functional outcomes and quality of life after partial glossectomy for T2 squamous cell carcinomas (PMC, NIH)
    This study looks at how the type of reconstruction and tongue movement shape long-term speech and swallowing after partial tongue removal.


Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Can You Get Cancer More Than Once?

Can You Get Cancer More Than Once?

Yes, you can. Sometimes the original cancer returns after treatment, which is called a recurrence. Other times a completely separate cancer shows up later in life, known as a second primary cancer. They start differently and they’re treated differently, so the first job is figuring out which one you’re dealing with.

Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, explains how this is worked out. “Nobody finishes treatment and stops thinking about it. Every new ache, every scan, there’s a quiet question: is it back? Mostly the answer is no. When there is something, our first job isn’t to treat it. It’s to find out what it is, the old cancer or a new one, because the plan is different for each.” To discuss follow-up or treatment options, you can contact the clinic at +91 9482202240.

Worried about a recurrence or a new symptom after treatment? Visit the clinic to talk through your follow-up plan.

What Is the Difference Between Cancer Recurrence and a Second Primary Cancer?

Picture someone treated for colon cancer five years ago who now has a spot on the liver. Is it the colon cancer that travelled, or something new? That’s exactly what these two terms help answer.

A recurrence means the original cancer has come back. It could be in the same place, in nearby lymph nodes, or far away in the liver or lungs. Distance doesn’t change what it is: colon cancer in the liver is still colon cancer, not liver cancer.

A second primary is a brand-new cancer that starts from different cells. It can appear in another organ or even in the same one.

The distinction matters because a recurrence is handled as the original disease, while a second primary is a fresh diagnosis judged on its own. Timing differs too. Recurrences mostly appear in the first few years, but a second primary can turn up at any point, even decades later. Our case study section includes a patient who dealt with two primary cancers.

Why Does Cancer Come Back After Treatment?

Surgery removes what can be seen. It can’t remove what’s too small to see.

A few cells can be left behind, too tiny for any scan to detect, and they may slowly grow back. Bigger, deeper and faster-growing tumours return more often, and so do those that had already reached the lymph nodes by the time of surgery.

Timing is fairly predictable. In a combined analysis of colorectal cancer trials, recurrences levelled off at around three years, although some cancers return much later. In cancers of the colon, ovary and appendix, the lining of the abdomen is one place they can come back, and HIPEC is among the options there.

Why Do Some People Get a Second Primary Cancer?

Having cancer once doesn’t mean another is certain. The risk is a little higher, though, and there are a few reasons for that.

The first is shared exposure. Tobacco and alcohol, which often help cause the first cancer, keep acting on the same tissues. After a mouth cancer, a new one can appear in the mouth, throat, food pipe or lung. Doctors call this field cancerization, and our page on oral cancer treatment covers how these cancers are managed.

Then there’s inheritance and past treatment. Conditions like Lynch syndrome raise the lifetime risk of several cancers, and radiation or certain chemotherapy drugs can, rarely, do the same years afterward.


What Determines Treatment and Follow-up After a Recurrence or Second Cancer?

It all starts with working out which one it is.

Usually a biopsy, compared against the report on the original tumour, settles it. Scans such as CT, MRI or PET-CT show where the growth sits and how far it has gone, and in some cancers a blood marker like CEA (in colorectal cancer) adds another clue. A growth in the same spot a few years on points toward recurrence. A different organ many years later points toward a new primary.

From there, the plan depends on the type of cancer, where it is and how far it has spread. What’s already been given matters too. Radiation usually can’t be repeated at full dose in the same area, so earlier treatment narrows the choices. Where surgery is the right call, a minimally invasive route may still be possible, as our page on robotic cancer surgery explains. Overall fitness for an operation counts as well, and if the pattern suggests an inherited condition, genetic counselling can help the whole family.

Once treatment is done, follow-up means regular visits, scans and blood tests on a schedule that suits the cancer. Report anything new quickly. Staying tobacco-free, keeping alcohol low, staying active and keeping up with screening all help.

Key Takeaways

  • Yes, cancer can occur more than once, either as a recurrence of the original cancer or as a new second primary.
  • A recurrence is the same cancer returning, near or far. A second primary starts from different cells and is treated as a new diagnosis.
  • Recurrences tend to appear in the first few years, while a second primary can occur at any time.
  • A biopsy compared against earlier reports tells the two apart, and the treatment plan follows from that.
  • Regular follow-up, prompt reporting of new symptoms and healthy habits all matter.

Frequently Asked Questions

Can you get cancer more than once?

 Yes. The original cancer can return, or a new, unrelated one can appear.

What is the difference between cancer recurrence and a second primary cancer?

A recurrence is the old cancer coming back. A second primary is a new cancer from different cells.

How long after treatment can cancer come back?

Mostly in the first few years, though some come back much later.

Does having cancer once mean I will get it again?

 Not necessarily. The risk is slightly higher, though, which is why follow-up matters.

References

1.American Cancer Society – Second Cancers
https://www.cancer.org/cancer/survivorship/second-cancers-in-adults.html

2. National Cancer Institute – Second Primary Cancer
https://www.cancer.gov/publications/dictionaries/cancer-terms/def/second-primary-cancer


Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

What Is the Difference Between Oncology and Surgery?

What Is the Difference Between Oncology and Surgery?

Ask a newly diagnosed patient what is troubling them and one question comes up early: oncology vs surgery, which one do I need? It is a fair question, but it is not a contest. Oncology is the whole subject of cancer care. Surgery is one of the things it uses. What separates them is reach: drugs go round in the blood and find cancer cells wherever they are hiding, while surgery works on one spot, the solid tumour and a little healthy tissue around it. The surgical oncologist sits where the two meet, and that is why oncology and surgical oncology get talked about together.

According to Dr. Sandeep Nayak, a surgical oncologist in Bangalore, nobody is really asked to pick between the two. Many solid tumours need both at some point. What changes from case to case is the sequence, and the cancer type, the stage and the patient’s fitness for surgery decide it.

Have a biopsy report or a scan and unsure what the next step is? You may contact  Clinic on +91 9482202240.

Oncology vs Surgery: The Core Difference

Oncology is the field. Surgery is one tool inside it. At a cancer centre they sit side by side in one team of oncologists.

  • Oncology: All of cancer care, from the first scan to the last follow-up visit. It has three main arms: medical, radiation and surgical.
  • Medical oncology: The drug arm. Chemotherapy, targeted tablets, immunotherapy and hormone treatment go round in the blood, so they reach the main tumour, the lymph nodes and any organ it may have spread to, in one go.
  • Surgery: The operating arm. The surgeon takes the tumour out from where it started, with a rim of normal tissue and the lymph nodes next to it.
  • Radiation oncology: Beams of radiation aimed at one area. Local, like surgery, but with no incision.
  • Why both exist: A drug can reach cells that scans can’t see, but it can’t take out a solid lump. Surgery gets the lump out, but a cell that has already moved on is beyond its reach.

Oncology and Surgical Oncology: Where They Meet?

A surgical oncologist is a surgeon who looks at cancer cases day in and day out. The job is bigger than the operation, and surgical oncology takes in the steps before and after it too.

  • Biopsy: First, a piece of the tumour has to be taken out and looked at under a microscope. Quite often the surgeon does this, with a needle, an endoscope or a small cut.
  • Staging: Once the scans and biopsy are in, the cancer gets a stage. The TNM system looks at three things: how big the tumour is, whether the nodes are involved, and whether it has spread. Every later decision leans on this.
  • The operation: The surgeon wants a clear margin, which means healthy tissue all round the tumour, and the nearby lymph nodes out as well. Leaving cancer behind weakens the benefit of everything that follows.
  • Function: Where it can be done, speech, swallowing and bowel or bladder function are kept safe, and what had to be removed is rebuilt.
  • Relief of symptoms: Sometimes the cancer can’t be removed fully. An operation can still open a blocked bowel or stop a bleed, and the patient feels better for it.

How the Two Work Together in Your Treatment Plan?

So which comes first? There’s no single answer, and the pages under cancer treatment services show how differently each cancer is handled.

  • Staging first: Many illnesses are staged before anyone picks a treatment; the stages of heart failure are a good example from cardiology. Cancer works the same way. The stage decides how much the surgeon will do and how much is left to drugs.
  • Surgery first: Take early colon cancer. The tumour is removed first. Then the pathology report is read. If the nodes show spread, or the tumour looks high-risk, chemotherapy is added.
  • Drugs before surgery: Drugs given first are called neoadjuvant treatment. In locally advanced rectal cancer, chemoradiation is commonly given first. It can shrink a tumour so that it is easier to remove completely.
  • Drugs after surgery: This is called adjuvant treatment. It targets cells that may be left behind after the operation.
  • No surgery at all: Some cancers never reach an operating table. Leukaemia and lymphoma, for example, are treated mainly with drugs. For the rest, the site and the stage decide.

Key Takeaways

  • Oncology vs surgery is not an either-or choice. Surgery is one treatment inside oncology.
  • Drugs go through the whole body; surgery works on one spot.
  • A surgical oncologist is a cancer surgeon who works with the drug and radiation specialists.
  • Cancer type, stage and fitness for surgery decide what comes first.
  • Neoadjuvant means drugs before surgery. Adjuvant means drugs after it.

Frequently Asked Questions

Is oncology the same as surgery?

No. Surgery is one of the treatments oncology uses.

What does a surgical oncologist do?

Confirms the cancer, stages it, and operates when surgery is needed.

Does everyone with cancer need an operation?

No. It depends on where the cancer is and how far it has gone.

Can chemotherapy alone treat a solid tumour?

Sometimes. More often it works alongside surgery or radiation.

References


  1. Recognizing the role of surgical oncology and cancer imaging in the multidisciplinary approach to cancer: an important area of future scholarly growth for BMC Cancer. https://pmc.ncbi.nlm.nih.gov/articles/PMC3724699/
  2. Delivering cancer services: a multi-disciplinary approach. https://pmc.ncbi.nlm.nih.gov/articles/PMC3097621/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Robotic vs Laparoscopic vs Open Surgery for Rectal Cancer: How Do They Compare?

Robotic vs Laparoscopic vs Open Surgery for Rectal Cancer: How Do They Compare?

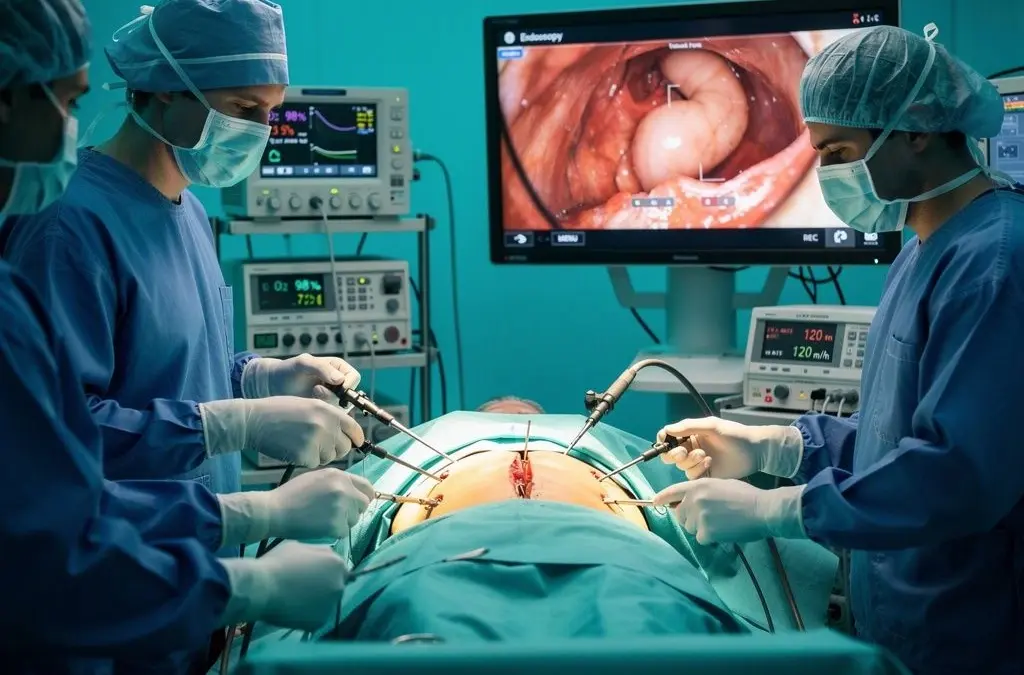
Rectal cancer surgery can be done robotically, laparoscopically or through an open incision, and the right choice turns on where the tumour sits, how narrow the pelvis is and what kind of recovery the patient is aiming for. All three can cure the cancer in experienced hands, which is why the decision is about what fits the individual patient and not about which technology is newest.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at  Clinic, Bangalore, explains how the three approaches are weighed in rectal cancer surgery. “Patients often come asking which of the three is best. The rectum is hard to reach, down in a narrow pelvis, so how we operate matters a little more here than in other cancers. Whatever the route, the plan is the same: take the whole tumour out, save the nerves and the sphincter if the cancer allows it, and get the patient back on their feet. If one route does that better for you, that’s the one we use.”

 If you’d like to talk through your own options, the clinic can be reached at +91 9482202240.

How Do Robotic, Laparoscopic and Open Rectal Cancer Surgery Differ?

The aim is the same in all three. What changes is how the surgeon gets down to a tumour sitting low in the pelvis.

Open surgery: One longer cut in the abdomen. The surgeon can put their hands in and see the area directly.

Laparoscopic surgery: Several short cuts take its place. A camera and thin instruments go through them, and the surgeon works by hand while watching a monitor.

Robotic surgery: The cuts are small here too. The surgeon sits at a console a few feet from the patient, the screen is magnified and in 3D, and the instrument tips can turn in ways a straight laparoscopic instrument can’t. The robot decides nothing. Every movement is the surgeon’s own.

What stays constant: In all three, the central step is total mesorectal excision, where the rectum comes out together with the fat and lymph nodes around it as a single package. How cleanly that is done matters more than which instrument did it. Our page on robotic cancer surgery explains how the system works.

Is Minimally Invasive Surgery as Effective as Open Surgery for Rectal Cancer?

For laparoscopic surgery, the evidence is reasonably firm.

The COLOR II trial: Roughly a thousand patients were randomly placed into laparoscopic or open surgery groups. Three years later the cancer had returned in the pelvis in 5% of each group, and survival was close.

Recovery: People who had keyhole surgery tended to bleed less, have less pain and go home sooner.

A caution: Rectal surgery by keyhole is demanding, and the trial results came from surgeons who did it regularly.

For a wider look across other cancers, see our blog on whether minimally invasive cancer surgery gives the same cure rate as open surgery.

What Determines Treatment Choice?

Every patient is assessed individually, and a handful of points steer the decision.

Where the tumour is: Upper, middle or low rectum, and how far it lies from the anal opening.

Stage and what comes before surgery: Many patients have chemotherapy or radiation first, and how the tumour responds can change the plan.

Pelvic anatomy and build: A narrow pelvis, a heavier build or a bulky tumour can make one approach harder than another.

Sphincter and stoma: Whether the sphincter can be saved, and whether a temporary or a permanent stoma will be needed.

General health and old scars: Fitness for a long operation, and what earlier surgery has left behind.

The team’s experience: How often they do this operation, and by which route.

What matters to you: Recovery time, scars and everyday life all count once the options have been laid out. A case study on advanced rectal cancer care shows how that works in practice.

Key Takeaways

  • Any of the three approaches can remove a rectal cancer completely. How cleanly the mesorectum is taken out matters more than which instrument is used.
  • In the large COLOR II trial, laparoscopic and open surgery gave similar recurrence and survival at three years, and keyhole patients recovered faster.
  • Randomised trials haven’t shown that robotic surgery cuts the need to convert to open surgery. It may still help with a narrow pelvis or a low tumour.
  • Open surgery remains the safer route for some tumours, for emergencies and for a pelvis scarred by earlier operations.
  • Tumour position, stage, earlier treatment, pelvic anatomy and the surgeon’s experience decide the approach.
  • To talk through your own case, you can book an appointment or call the clinic on +91 9482202240.

Frequently Asked Questions

Is robotic surgery better than laparoscopic surgery for rectal cancer?

In the trials so far the cancer results look alike, so the surgeon’s skill counts for more than the machine.

Is laparoscopic surgery as good as open surgery for rectal cancer?

In the COLOR II trial, recurrence and survival at three years were alike, and keyhole patients recovered faster.

Will I need a stoma after rectal cancer surgery?

Sometimes, and it may be temporary or permanent, depending on how low the tumour is and how close it comes to the sphincter.

When is open surgery still preferred for rectal cancer?

When the tumour has grown into nearby organs, in an emergency, or when old scar tissue makes keyhole risky.

References


Robotic vs Laparoscopic Surgery for Rectal Cancer: ROLARR Randomized Clinical Trial Compares robotic and laparoscopic rectal cancer surgery, including conversion to open surgery, complications and cancer-related outcomes. Read the study – JAMA / PubMed Central

Robotic-Assisted vs Laparoscopic Resection for Rectal Cancer Reviews clinical outcomes, quality of life and costs associated with robotic and laparoscopic surgery. Read the study – NIHR Journals Library

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Minimally Invasive vs Open Esophagectomy: How Do Outcomes Compare?

Minimally Invasive vs Open Esophagectomy: How Do Outcomes Compare?

Compared with open esophagectomy, the minimally invasive route puts the body through less surgical trauma. Blood loss is lower and lung complications are fewer, especially in the weeks right after the operation. Long-term cancer outcomes in the trials so far are comparable, so the decision comes down to the tumour, the patient’s overall health and how experienced the surgeon is with the technique.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, explains how the two approaches compare for cancers of the food pipe. “It’s a big operation however you do it. What the keyhole route changes is the chest wall, which isn’t cut open, and you see that in the first few weeks, with fewer chest infections and an easier recovery. None of that counts if the cancer isn’t cleared as well, so that’s the first thing we make sure of.”

If you’d like to know more about tongue cancer surgery, call the clinic on +91 9482202240.

What Is the Difference Between Minimally Invasive and Open Esophagectomy?

Both operations do the same job. The diseased part of the food pipe comes out, and what’s left gets joined to the stomach. How the surgeon reaches it is what differs.

Open: Big cuts, one in the chest and one in the abdomen. The surgeon works through them by hand.

Keyhole: A few small cuts instead. A camera and long, thin instruments go in through openings in the chest and belly.

Hybrid: Part keyhole, part open. Some surgeons do the abdomen by keyhole and the chest the open way.

Robotic: The same small cuts, with a robot holding the instruments and giving the surgeon a magnified 3D view.

What doesn’t change: The tumour and the nearby lymph nodes come out whichever route is used. The stomach is shaped into a tube and lifted up to take the place of the food pipe. If you’re curious how keyhole operations work in general, our page on laparoscopic cancer surgery explains it.

When Is Open Esophagectomy Still the Better Choice?

Keyhole isn’t for everyone.

Large or invasive tumours: A tumour pressing on nearby structures can call for the room and control that open surgery gives.

Earlier surgery: Scarring from a previous chest or abdominal operation can make keyhole surgery harder to do safely.

Changing course: Sometimes the surgeon starts with keyhole and moves to open because carrying on isn’t safe. That’s judgement, not a failed operation.

Experience: It’s a demanding operation to do by keyhole, and results are best where the team does it regularly. You can read about the surgeon’s background on our expertise page.

What Determines Treatment Choice?

It’s decided case by case. A few things steer it.

Stage and site: Where in the food pipe the cancer sits, how deep it goes, and whether the lymph nodes are involved. Esophageal cancer is one of the upper GI cancers, and the stage shapes the whole plan.

Before surgery: Many patients have chemotherapy or chemoradiation first, and how the tumour responds affects the planning.

General health: Heart, lungs and nutrition all count. A lot of people have lost weight because swallowing has been difficult.

Team review: Surgical, medical and radiation oncologists usually go through the case together.

Your priorities: Recovery time, scars, getting back to normal life. Robotic-assisted surgery is one of the keyhole options, and our page on robotic cancer surgery covers it.

Key Takeaways

  • Minimally invasive esophagectomy may reduce blood loss, lung complications, and hospital stay compared with open surgery.

  • Long-term survival outcomes appear similar between the two approaches in available clinical trials.

  • Open surgery may be more suitable for certain tumours, depending on their location and extent.

  • The choice of surgical approach depends on the patient’s condition, tumour characteristics, and the surgeon’s experience.

  • Discuss the benefits and risks of each option with your specialist. To learn more, book an appointment or call +91 9482202240.

Frequently Asked Questions

Is minimally invasive esophagectomy as safe as open surgery?

 So far, yes, with fewer early lung problems, though it depends on the surgeon’s experience.

Does minimally invasive esophagectomy cure cancer as well as open surgery?

Survival looked similar at three years in the main trial.

How long is recovery after minimally invasive esophagectomy?

 You’ll usually leave hospital sooner than after open surgery, but full recovery still takes weeks to months.

When is open esophagectomy still preferred?

For large tumours pressing on nearby structures, or after earlier surgery that makes keyhole unsafe.

References


National Cancer Institute (NCI) – Esophageal Cancer Treatment (PDQ®) Explains treatment options for esophageal cancer, including surgery, and discusses factors that influence treatment decisions. Link: https://www.cancer.gov/types/esophageal/hp/esophageal-treatment-pdq

American Cancer Society – Surgery for Esophageal Cancer Describes esophagectomy, including minimally invasive and open surgical approaches, and outlines potential risks and recovery considerations. Link: https://www.cancer.org/cancer/types/esophagus-cancer/treating/surgery.html

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Call Now Button