
This website is being reviewed and updated in line with the National Medical Commission (NMC) guidelines on ethical advertising and public communication by registered medical practitioners.
support@macsclinic.com
+91 9482202240
What Is Robotic Kidney Cancer Surgery Recovery Like?

What Is Robotic Kidney Cancer Surgery Recovery Like?

After robotic kidney cancer surgery, most patients recover faster and with less pain than they would after an open operation. A few small keyhole cuts replace one long incision, and many patients are on their feet the next day. Healing deeper down takes longer, though. How long robotic kidney surgery recovery time lasts depends on the operation, the tumour and the patient’s general health.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in Bengaluru at MACS Clinic, patients tend to focus on the operation itself and are caught off guard by the tiredness afterwards. “The operation is the shorter part of it. Pain settles within days, but the body takes weeks to catch up. Walking early, resting properly and not lifting too soon matter more than most people expect.”

Have questions about recovering from robotic kidney cancer surgery? Speak to your surgical oncologist.

How Do the First Days in Hospital Go After Robotic Kidney Cancer Surgery?

Waking up. It starts in the recovery area, where nurses check blood pressure, breathing and pain for a few hours. After that the patient goes to the ward, usually with a urinary catheter and sometimes a thin drain by the wound. Both are generally removed in a day or two.

Pain. It is mostly mild to moderate, and tablets are enough for most patients. Day two to day four is usually the sorest stretch. Some patients also feel an ache at the tip of the shoulder. That comes from the gas used to inflate the abdomen, and it wears off in a few days.

Getting moving. Sitting up, a few steps, some deep breaths: the nurses will ask for all three on the first day. It keeps the lungs clear and the legs moving, and that matters for clots. Most patients can eat again that day or soon after.

Going home. Day one, two or three is typical. Open surgery keeps patients in a few days longer because the wound is so much bigger. The small incisions of robotic cancer surgery are the main reason the stay is shorter.

What Does Robotic Kidney Surgery Recovery Time Look Like at Home?

Weeks one and two. Tiredness catches many patients out. Even a short walk can feel like a lot. Walk a little, several times a day, and sleep when the body asks for it. Appetite returns slowly, and the bowels can take a few days to get going. Wound care is done as the surgical team advises.

Lifting and exercise. No heavy lifting for the first four to eight weeks. The exact number depends on the operation and on what the surgeon says. Gym work and running wait as well. Driving is fine once pain no longer slows the reflexes, which is usually after two to four weeks.

Back to work. Desk work can often restart at around four to six weeks. Jobs involving heavy lifting take longer. Fatigue can linger for up to two months, which is normal.

Partial or radical. Recovery after the two is broadly similar. The kidney repair in a partial nephrectomy often means the lifting limits last a little longer.

What to report. Call the surgical team if there is a fever, or if the wound turns red, swollen or starts to leak. The same goes for pain that is climbing rather than easing, and for blood in the urine that won’t clear. A calf that is swollen and tender, or any breathlessness, should be reported as well.

What Determines the Course of Recovery After Robotic Kidney Cancer Surgery?

Robotic kidney cancer surgery recovery is rarely identical for two patients. The type of operation comes first. In a partial nephrectomy only the tumour is cut out and the kidney is repaired. In a radical nephrectomy the whole kidney is taken out. A large tumour, or one sitting deep in the kidney, takes more work to remove, and that can mean a slower recovery. The patient matters as much as the tumour. A fit, non-smoking patient in his fifties and an older patient with diabetes or a weak heart rarely recover at the same pace. Kidney function before the operation also counts. The tissue that is left has to carry the load.

The tumour goes to the laboratory, and the pathology report tells the surgeon whether anything more is needed. Kidney cancer treatment and follow-up are planned around all of this. The first review happens two to four weeks after surgery. After that, expect blood tests to see how the kidneys are coping, with scans at intervals the surgeon will explain.

Key Takeaways

  • For kidney cancer, robotic surgery usually brings an easier recovery than open surgery, with less pain.
  • Most patients go home in one to three days, though full healing inside takes weeks.
  • Plan on about four to eight weeks without heavy lifting. Tiredness can last up to two months.
  • No two recoveries match. The operation, the tumour and the patient’s health all play a part.
  • The care doesn’t end at discharge, since check-ups, blood tests and scans follow.

Frequently Asked Questions

What is the usual robotic kidney surgery recovery time?

About four to six weeks before most people feel like themselves.

How many days is the hospital stay after robotic kidney surgery?

One to three days for most. Open surgery takes longer.

When can someone drive or lift heavy things again?

Driving at two to four weeks. Heavy lifting waits four to eight.

Does recovery differ between partial and radical nephrectomy?

Not much, though partial nephrectomy may mean longer lifting limits.

References

  1. Kingston and Richmond NHS Foundation Trust. Having a kidney removed (robot-assisted). https://www.kingstonandrichmond.nhs.uk/patients-and-families/patient-leaflets/kidney-removal-robot
    .
  2. The Christie NHS Foundation Trust. Robot-assisted laparoscopic partial nephrectomy. https://www.christie.nhs.uk/media/h23dtcyi/1153-robot-assisted-laparoscopic-partial-nephrectomy-uro.pdf

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Can Men Get Breast Cancer?

Can Men Get Breast Cancer?

Men can get breast cancer too. It is not common, since fewer than one in a hundred cases is in a man, but it is common enough that doctors see it. The cause is nothing mysterious. A man has a bit of breast tissue behind each nipple, the same as anyone, and cells in that tissue can turn cancerous. The difficulty is that few men think of it, so a lump is often left alone for a while. That delay is the real problem with male breast cancer. The sections below cover who is at risk, what to watch for and how a lump is tested.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in Bengaluru at MACS Clinic, the delay usually comes down to embarrassment, or to the belief that this is a women’s disease. “A man with a lump in his chest should get it looked at, the same as a woman would. Often it’s nothing serious, but you can’t know that by feeling it. It needs an examination, a scan and sometimes a biopsy.”

Have questions about male breast cancer? Speak to your surgical oncologist.

Who Gets Male Breast Cancer, and What Raises the Risk?

There isn’t one clear cause, and for many men there’s no obvious reason at all. A few things do show up more often, though.

Age. Mostly a disease of older men, with the average patient somewhere in his 60s or 70s. A man in his 40s can get it, but that’s unusual.

Family and genes. A mother, sister or father who has had breast cancer counts. Then there are the BRCA2 and BRCA1 genes. A fault in either one can come from the father’s side as well as the mother’s.

Hormones. Anything that leaves a man with more oestrogen than usual can play a part. Cirrhosis of the liver does this, and so does Klinefelter syndrome, a condition where a boy is born with an extra X chromosome. Both are linked with a higher risk.

Past radiation and extra weight. Radiotherapy to the chest earlier in life is one factor, since treatment for one cancer can rarely lead to a second cancer years later. Obesity is another, because body fat makes oestrogen.

Having a risk factor doesn’t mean cancer is coming. And plenty of men with breast cancer tick none of these boxes.

What Are the Signs of Breast Cancer in Men, and How Do Doctors Confirm It?

The lump. Hard, painless and usually just under the nipple or to one side of it. Men tend to find it by accident, in the shower or while pulling on a shirt. A separate guide covers breast cancer symptoms, screening and prevention in more detail.

The nipple. Watch for one that has started pulling inwards, any discharge (blood-streaked fluid especially), or a crusty, sore spot that won’t heal.

Skin and armpit. The skin over the chest may pucker or turn red, and a lump can show up in the armpit.

Not always cancer. Gynaecomastia is far more common than cancer, and it also causes swelling behind the nipple, sometimes on both sides. Fingers can’t tell the difference, which is why a doctor has to check.

Getting a diagnosis. First comes an examination, then usually a mammogram or ultrasound, and a needle biopsy to get a sample. The lab studies the sample under the microscope and also tests it for hormone receptors and HER2. Those two results matter a great deal once treatment is being planned.

What Determines Treatment for Male Breast Cancer?

Treatment is tailored to the man, and the stage carries the most weight. Doctors want to know whether the cancer is still within the breast, has reached the lymph nodes in the armpit, or has spread beyond. After that come the type of tumour, the receptor results and how fit he is for surgery. Male and female breast cancers are staged the same way.

Most plans start with surgery: the breast tissue comes out and the armpit nodes are checked. What follows depends on the pathology report. Radiotherapy is needed for some men, chemotherapy for others, and hormone tablets are often added when the tumour is hormone receptor positive. The surgeon looks at all these reports together when deciding on breast cancer treatment.

Key Takeaways

  • Men can get breast cancer, but it is uncommon: fewer than one in a hundred cases.
  • The tissue behind a man’s nipple is where it starts.
  • Older age, relatives with breast cancer, BRCA changes and high oestrogen raise the risk.
  • Any hard, painless lump near the nipple should be examined, even if it turns out to be harmless.
  • Biopsy and receptor results decide the treatment, which usually starts with surgery.

Frequently Asked Questions

Is it possible for men to get breast cancer?

 Yes, though it is rare, under one per cent of all cases.

What does breast cancer in men look like at first?

Usually a hard lump near the nipple that doesn’t hurt.

Is a breast lump in a man always cancer?

Not always. Harmless gynaecomastia is common, but get any lump checked.

How is male breast cancer treated?

Mostly surgery, then radiotherapy, chemotherapy or hormone tablets when the reports call for it.

References

  1. NHS. Breast cancer in men. https://www.nhs.uk/conditions/breast-cancer-in-men/
    Explains symptoms, causes, tests and treatment of breast cancer in men.
  2. National Cancer Institute (NIH). Male Breast Cancer Treatment (PDQ), Patient Version. https://www.cancer.gov/types/breast/patient/male-breast-treatment-pdq

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
How Do I Check for Oral Cancer at Home?

How Do I Check for Oral Cancer at Home?

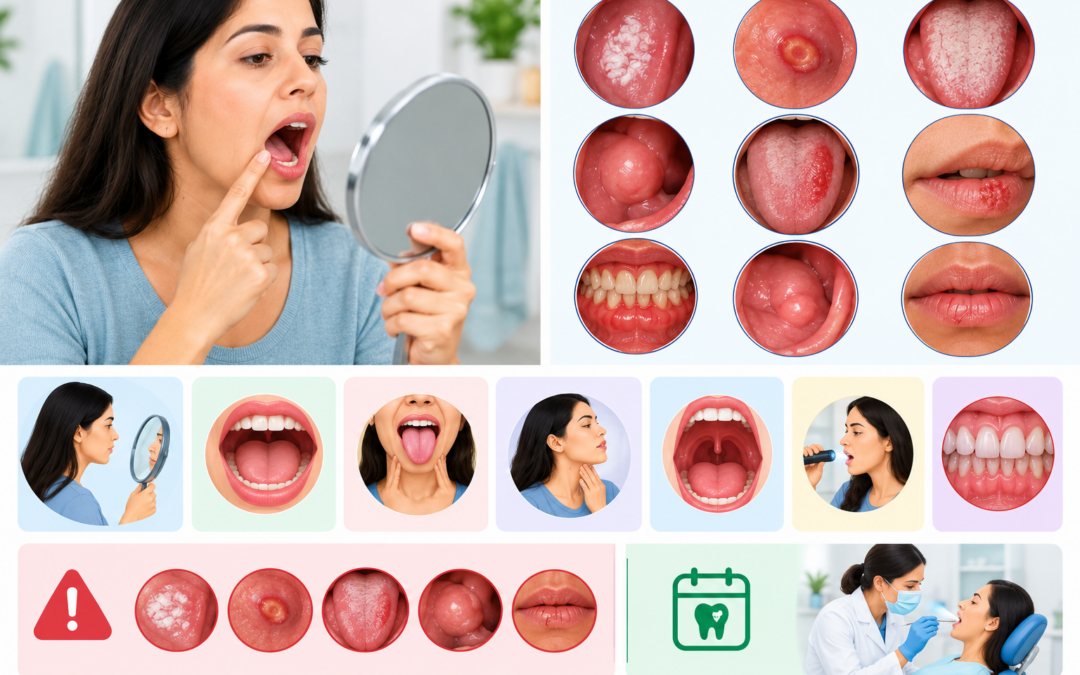
You can check for oral cancer at home once a month by looking inside your mouth in a mirror under a bright light, and by feeling for lumps. This cancer self-examination takes a few minutes. It looks for sores that don’t heal, white or red patches and lumps in the mouth or neck. It helps you notice changes early, but it can’t rule cancer out and doesn’t replace an examination by a doctor or dentist.

Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, explains where cancer self-examination of the mouth fits in. “A home check is a way to learn what is normal for your mouth. Most changes turn out to be harmless, such as a bitten cheek or a sore from a sharp tooth. A sore, patch or lump that doesn’t settle in three weeks needs a proper examination. The home check supports regular visits to a doctor or dentist and doesn’t replace them.”

Have concerns about oral and head and neck cancer checks? Discuss your questions with a surgical oncologist.

How Do You Perform a Monthly Self-Examination at Home?

It takes a few minutes in front of a mirror, in good light.

Get ready: Wash your hands and take out any dentures. Stand in front of a mirror with a bright light, such as a torch, and pick a set day each month.

Face and neck: Look at both sides of the face and neck for swelling. Press gently along the jaw and the sides of the neck for lumps.

Lips and gums: Pull down the lower lip and lift the upper lip to see the inside. Look at the gums, front and back.

Cheeks and roof of the mouth: Pull each cheek away with a finger and look for red or white patches. Tilt the head back and look at the roof of the mouth.

Tongue and floor of the mouth: Stick the tongue out to see the top and sides, then lift it to see the underside and the floor of the mouth. Feel gently for hard spots. Our page on oral cancer treatment explains the tests used if a concern is found.

What Changes Should You Look For?

Most mouth changes are harmless. These are the ones that need a doctor’s opinion.

A sore that doesn’t heal: A mouth ulcer that lasts more than three weeks. Early mouth cancer can look like an ordinary ulcer.

White or red patches: Patches that don’t go away, or a mixed red and white area. Our blog on precancerous mouth lesions explains the common ones.

A lump or thickening: A lump or hard area inside the mouth, on the lip, or in the neck or throat.

Numbness, pain or changes in function: Numbness, ongoing pain, bleeding, loose teeth, trouble chewing or swallowing, or dentures that no longer fit.

Higher risk: Chewing tobacco, gutka, betel quid or areca nut, smoking and heavy alcohol use raise the risk, so people who use them should check carefully and see a dentist or doctor regularly. Our blog on what causes oral cancer covers the causes.

How to Check for Oral Cancer at Home?

  • Once a month, in good light with a mirror, take out any dentures and look at your lips, cheeks, gums, tongue (top, sides and underneath), and the roof of your mouth.
  • Run your fingers along your jaw and both sides of your neck. A new lump, or one on only one side, needs attention.
  • Don’t ignore an ulcer that hasn’t healed in 2–3 weeks, a white or red patch, unexplained bleeding, numbness, or trouble swallowing.
  • If you chew tobacco, gutka or paan, or drink often, never skip the monthly check.
  • A home check can’t confirm cancer, and early oral cancer usually doesn’t hurt. If anything lasts past three weeks, get it seen by a specialist. Read more about Oral Cancer Treatment.

What Determines Treatment Choice?

If a doctor finds a suspicious area, a few steps follow.

Examination: A doctor or dentist examines the mouth and neck, and may refer you to a specialist for a closer look.

Biopsy: A small sample of tissue is examined under a microscope. This is the only way to confirm cancer.

Imaging: CT or MRI scans show how deep the growth is and whether the lymph nodes in the neck are involved.

Stage and site: The size, depth and position of the growth, and whether it has spread, decide whether surgery, radiation, drugs or a combination is advised. Our blog on survival in head and neck cancer explains why stage matters.

General health and habits: Fitness for treatment, and tobacco and alcohol use, shape the plan and the follow-up.

Key Takeaways

  • A monthly mouth check takes a few minutes and needs a mirror, a bright light and clean hands.
  • Look for a sore that doesn’t heal in three weeks, white or red patches, lumps in the mouth or neck, numbness and loose teeth.
  • A home check can’t rule out cancer and doesn’t replace an examination by a doctor or dentist, especially for people who use tobacco or alcohol.
  • Any change that lasts more than three weeks should be seen by a doctor, because the tests and treatment depend on the findings.

Frequently Asked Questions

How often should I check my mouth for cancer?

Once a month is advised. It takes only a few minutes.

What does early oral cancer look like?

Often an ulcer, a red or white patch, or a small lump.

When should a mouth sore be checked by a doctor

If it hasn’t healed within three weeks, or comes with a lump or numbness.

Can a home check rule out oral cancer?

No. It helps spot changes, but a doctor or dentist must examine them.

References

  1. NHS — Symptoms of mouth cancer: https://www.nhs.uk/conditions/mouth-cancer/symptoms/
  2. NHS 111 Wales — Cancer of the mouth: https://111.wales.nhs.uk/cancerofthemouth/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

What Is Partial Nephrectomy and Who Needs It?

What Is Partial Nephrectomy and Who Needs It?

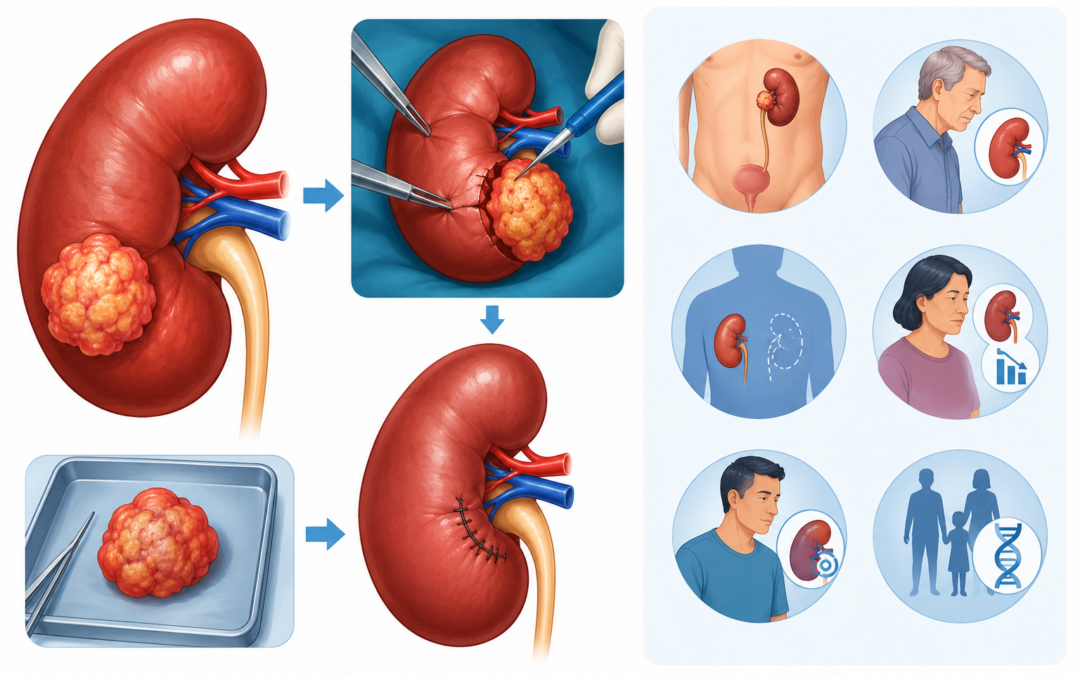
Partial nephrectomy is kidney surgery where only the tumour comes out, along with a narrow band of healthy tissue around it, and the rest of the kidney stays in the body. Once the tumour is out, the surgeon repairs the kidney with stitches so it keeps doing its job. Doctors mostly use it for small tumours, and for people who can’t afford to lose much kidney function. Surgeons can reach the kidney through an open cut, with keyhole instruments or with a robot.

Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, explains who is considered for partial nephrectomy. “Think of it this way. Your kidneys have to see you through your whole life, so if we can take the tumour out and leave you with as much working kidney as possible, that’s what we aim for. Whether we can depends mostly on how big the tumour is and where it’s sitting. The other kidney counts too, because its health decides how much kidney we can afford to lose. Not every  tumour is suitable, and removing the whole kidney is the right choice when it isn’t.”

Have questions about kidney surgery?

How Is a Partial Nephrectomy Done?

How Is a Partial Nephrectomy Done?<br />

Open, keyhole or robotic, the surgeon goes through roughly the same steps.

Planning: It starts with a CT or MRI. That scan tells the surgeon how big the tumour is, where exactly it sits, and how near it comes to the blood vessels and the part of the kidney that drains urine, so the cut can be planned before anyone picks up a knife.

Access: Some surgeons go in through one larger cut (open surgery), others through a few small keyhole cuts, and some of those use a robot to hold and steer the instruments. Our page on kidney cancer treatment covers the routes used.

Controlling blood flow: The blood supply to the kidney may be clamped for a short time, so the tumour can be removed with less bleeding. This time is kept as short as possible to protect the kidney.

Removing the tumour: The tumour is cut out together with a thin rim of healthy tissue around it, so nothing is left behind at the edge. The piece removed goes for pathology, which checks the edges.

Repair: After that comes the repair. The surgeon stitches the kidney to stop the bleeding and to close off the drainage system. Bleeding and urine leaking are the two things surgeons watch for afterwards, so nobody rushes this part.

Who Needs a Partial Nephrectomy?

Who Needs a Partial Nephrectomy?

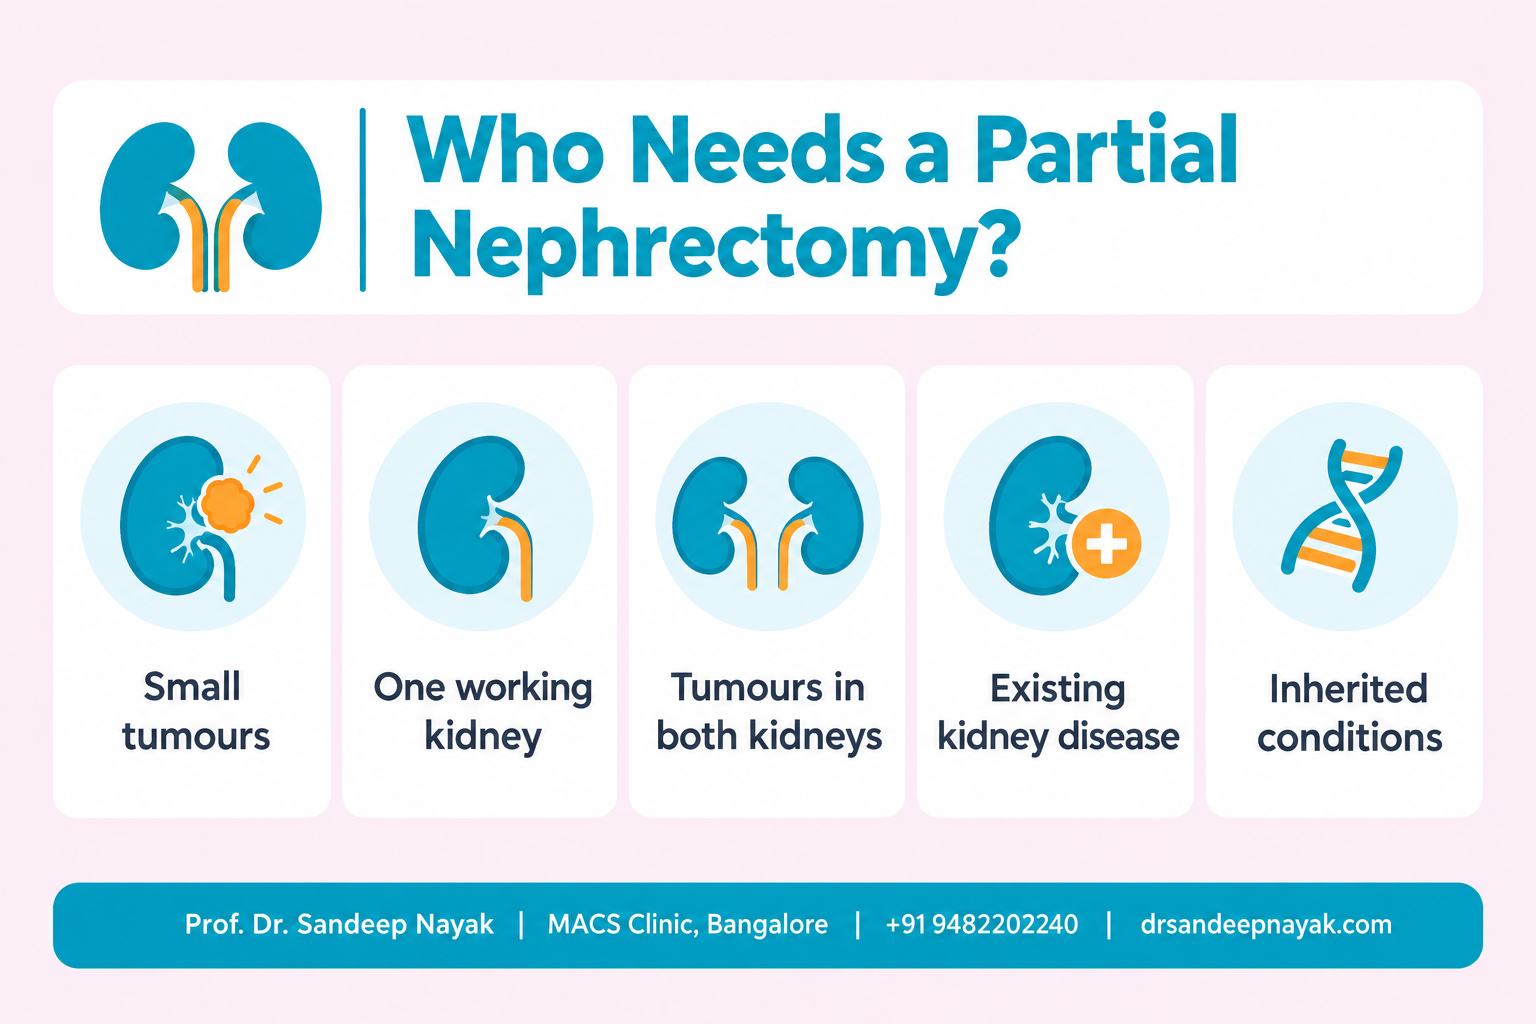
Small tumours come first on the list, and the case for it gets stronger when kidney function is at stake.

Small tumours: Mostly small ones, though a larger tumour can sometimes qualify if it’s sitting in a convenient spot.

One working kidney: With only one kidney, or a second one that barely works, there’s not much to spare, so saving tissue matters a lot.

Tumours in both kidneys: Take out each tumour separately and you can avoid losing an entire kidney. Our blog on kidney cancer in both kidneys covers this.

Existing kidney disease: If your kidneys are already weak, or you live with diabetes or high blood pressure, every bit of kidney tissue you keep is worth having.

Inherited conditions: A few people inherit a high risk of kidney tumours (von Hippel Lindau disease is one). They can end up needing surgery more than once, so each time the surgeon tries to take as little kidney as possible.

What Determines Treatment Choice?

No two cases are quite the same, so the call between a partial and a radical nephrectomy is made patient by patient.

Tumour size and position: Near the surface, a tumour usually comes out cleanly. One buried deep in the kidney, or sitting next to the main blood vessels, is trickier.

Spread: Once the cancer has pushed into the kidney vein, or gone beyond the kidney, a partial nephrectomy usually won’t be enough.

Kidney function: We check how well each kidney works, and the idea is to protect the combined total, not just one side.

General health: Fitness for surgery and anaesthesia shapes the route and the extent.

When the whole kidney comes out: If a partial nephrectomy isn’t safe, radical nephrectomy is advised. Our blog on partial vs radical nephrectomy explains the difference, and our blog on radical nephrectomy surgery covers that operation.

Key Takeaways

  • Partial nephrectomy removes the tumour along with a thin rim of healthy tissue, so most of the kidney carries on working.
  • It’s used mainly for small tumours, and when protecting kidney function matters most, for instance with one working kidney, tumours in both kidneys or existing kidney disease.
  • Open, keyhole or robotic, the surgeon repairs the kidney once the tumour is out.
  • Not every tumour suits it. What decides it is the size of the tumour, where it sits, whether it has spread and how well the kidneys work, so it’s best talked through with a specialist.

Frequently Asked Questions

What is a partial nephrectomy?

It’s surgery that takes the tumour out with a thin rim of healthy tissue around it and keeps the kidney.

Who is suitable for partial nephrectomy?

People with small tumours are the usual candidates, and so are those who have just one working kidney or tumours in both.

Is partial nephrectomy as effective as removing the whole kidney?

For tumours that suit it, yes, cancer control looks about the same in studies, and the kidney tends to work better afterwards.

Can partial nephrectomy be done by keyhole or robotic surgery?

Yes, it can be. Surgeons use open, keyhole or robotic routes, depending on the tumour.

References

 National Center for Biotechnology Information — Are we along the path for laparoscopic partial nephrectomy?: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2721544/
National Center for Biotechnology Information — Partial nephrectomy using porcine small intestinal submucosa: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3233505/


Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
What Are the Signs of Kidney Cancer in Adults?

What Are the Signs of Kidney Cancer in Adults?

Blood in the urine is among the most common signs of kidney cancer in adults, though plenty of people get no warning at all in the early stage. Tumours are often picked up by accident, on a scan ordered for something else. When kidney cancer symptoms do show up, they tend to be a pain in the side that won’t go away, a lump, tiredness and weight loss. Most of these have more common causes, so they call for a check rather than alarm.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore why kidney cancer symptoms are easy to miss. “Early kidney cancer is usually quiet. Many tumours are found by chance, on a scan done for another reason. Blood in the urine, a lasting pain in the side or a lump should be checked. Most turn out to have another cause, and a urine test and a scan can settle the question.”

If you’d like to know more about tests or treatment for kidney cancer.

What Are the Common Signs of Kidney Cancer?

Most signs only show up after the tumour has had time to grow, and plenty of them look like something else.

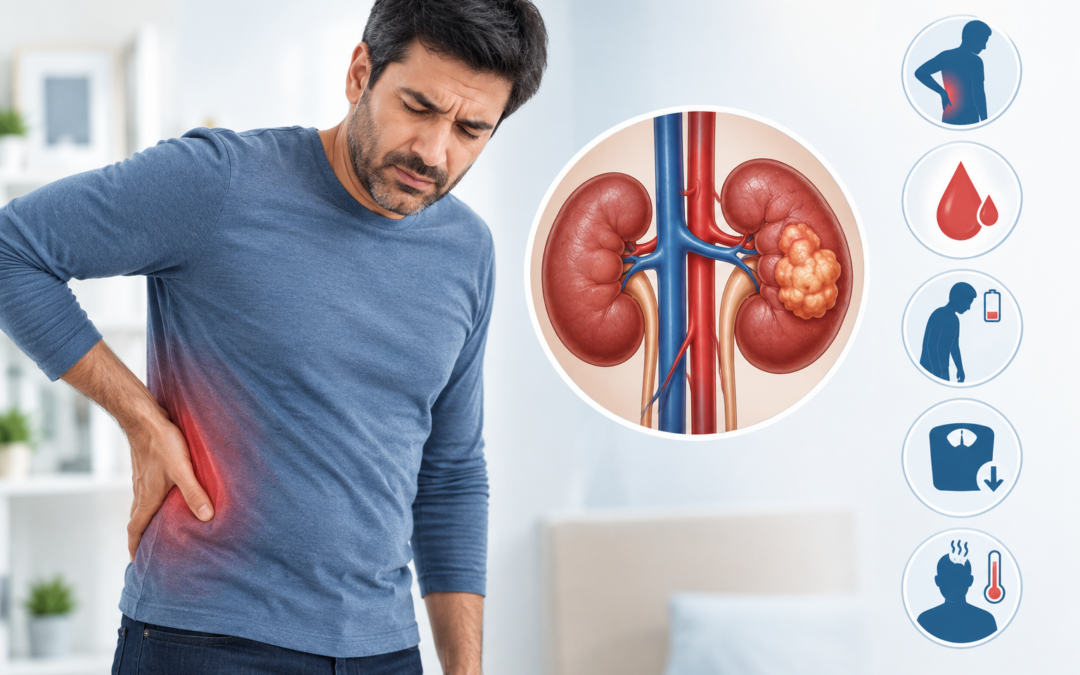
Blood in the urine: It might look pink, red or the colour of cola, then clear up for a few days, which is exactly why people ignore it. The blood can also come from the bladder, so don’t brush it off. Our blog on warning signs of bladder cancer covers that side.

Pain in the side: A dull ache somewhere between the ribs and the waist that stays put even after you’ve rested.

A lump: Something you can feel, a swelling or lump in the side or back just under the ribs.

Tiredness and weight loss: Feeling worn out for weeks, going off your food, or losing weight when you haven’t been trying to.

Fever and sweating: A high temperature that doesn’t go away, or heavy sweating, including at night. Our page on kidney cancer treatment lists the symptoms and the tests used.

Why Is Early Kidney Cancer Often Missed?

A small tumour can sit inside the kidney for a long time without bothering anything.

No early symptoms: At that size it isn’t pressing on anything, so there’s usually no pain and no change in the urine.

Found by chance: A lot of them are spotted by accident, on an ultrasound or CT done for something like back pain or kidney stones.

Look-alike causes: Stones, urine infections and a pulled back muscle can feel the same, and they’re far more common.

The classic trio is rare: Blood in the urine, side pain and a lump together are rare. Someone can have a tumour and none of the three.

Signs of spread: Once the cancer has spread, you might get bone pain, a cough or breathlessness. Our blog on metastatic renal cell carcinoma covers these signs.

Why Is Early Kidney Cancer Often Missed?

A small tumour can sit inside the kidney for a long time without bothering anything.

No early symptoms: At that size it isn’t pressing on anything, so there’s usually no pain and no change in the urine.

Found by chance: A lot of them are spotted by accident, on an ultrasound or CT done for something like back pain or kidney stones.

Look-alike causes: Stones, urine infections and a pulled back muscle can feel the same, and they’re far more common.

The classic trio is rare: Blood in the urine, side pain and a lump together are rare. Someone can have a tumour and none of the three.

Signs of spread: Once the cancer has spread, you might get bone pain, a cough or breathlessness. Our blog on metastatic renal cell carcinoma covers these signs.

What Determines Treatment Choice?

Once a scan picks up a tumour, the plan comes down to a handful of tests and findings.

Urine and blood tests: They look for blood in the urine and show how well the kidneys are working. They can’t confirm cancer on their own.

Imaging: An ultrasound usually comes first, then a CT or MRI, which show how big the tumour is, where it sits and whether it has spread.

Tumour size and position: With a smaller tumour, it may be possible to save part of the kidney. Our blog on partial vs radical nephrectomy explains the difference.

Spread: If it has spread, surgery alone may not be enough and drug treatment gets added.

General health and kidney function: How well the other kidney works and how fit you are for surgery also count towards the final call.

Key Takeaways

  • Early kidney cancer is often silent, and plenty of tumours get found by chance on scans.
  • Blood in the urine is one of the commoner signs. A lasting side pain, a lump, tiredness, weight loss or fever can show up too.
  • Most of these signs usually have everyday causes, but each one still deserves a check, and a urine test with a scan can usually sort it out.
  • Treatment depends on the size and position of the tumour, whether it has spread and how well the kidneys work, so it’s best talked through with a specialist.

Frequently Asked Questions

What is the earliest sign of kidney cancer?

Often there is none. Blood in the urine tends to be one of the first things people notice.

Does blood in the urine always mean kidney cancer?

No. Stones, infections and bladder problems are more common causes, but it still needs checking.

Can kidney cancer cause no symptoms at all?

Yes. Many early tumours turn up by chance, on scans done for some other reason.

Which tests check for kidney cancer?

Urine and blood tests first, then an ultrasound, CT or MRI to get a proper look at the kidney.

References

  1. Symptoms of kidney cancer (NHS)
    This page explains that kidney cancer often causes no obvious symptoms and is usually found while testing for something else, and lists the symptoms to watch for.
  2. Renal cell carcinoma presenting with haematuria and flank pain (PMC, NIH)
    This case report in an emergency medicine journal notes that kidney cancer in adults may show up as blood in the urine or flank pain, but more often as vague symptoms like tiredness and loss of appetite.

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Call Now Button