
This website is being reviewed and updated in line with the National Medical Commission (NMC) guidelines on ethical advertising and public communication by registered medical practitioners.
support@macsclinic.com
+91 9482202240
Total vs Subtotal Gastrectomy: How Is the Extent of Surgery Decided?

Total vs Subtotal Gastrectomy: How Is the Extent of Surgery Decided?

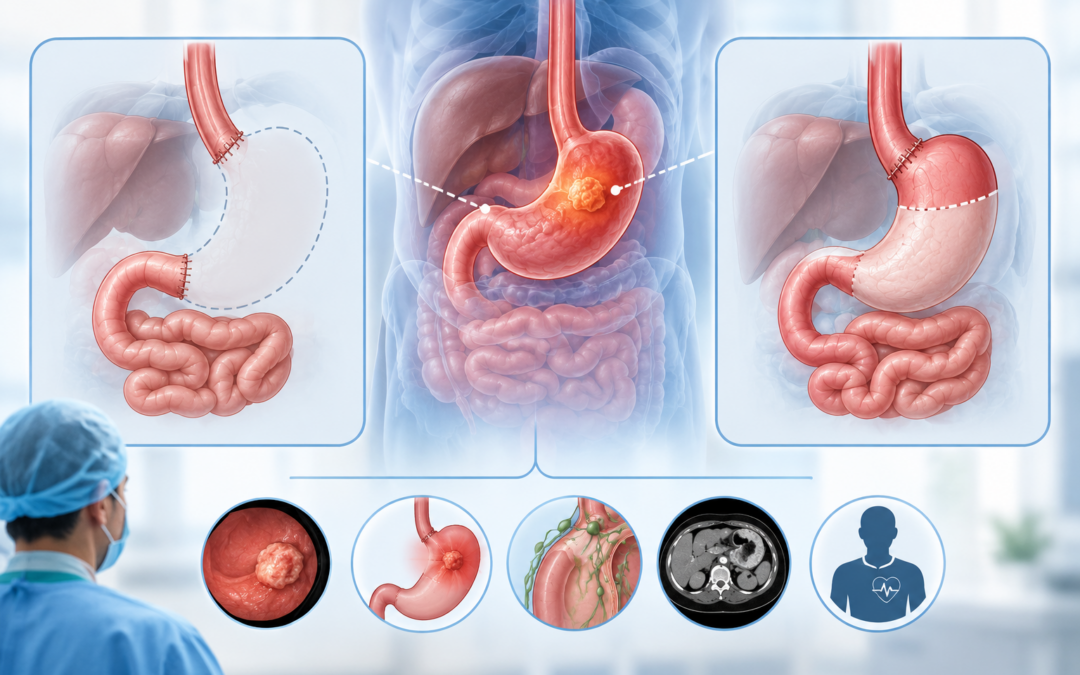
Most patients ask the same thing when surgery is advised for stomach cancer: how much of my stomach will be taken out? Put simply, there are two answers. Either all of it (total gastrectomy) or a part of it, usually the lower part (subtotal gastrectomy). Which one you get depends mostly on where the tumour is, how big it is and how it’s behaving. Doctors would rather save some stomach, because it helps with eating and nutrition later. But removing all the cancer always comes first. This is how total vs subtotal gastrectomy is decided.

According to Dr. Sandeep Nayak, a surgical oncologist in Bangalore, says you can’t name the exact operation from a diagnosis alone. The endoscopy, CT scan and biopsy come first, and even then the plan can still change during surgery, if the cut edge shows cancer.

If you have an endoscopy or biopsy report and want it explained, you may contact MACS Clinic on +91 9482202240.

What Total and Subtotal Gastrectomy Involve?

Surgery is a big part of stomach cancer treatment. Here is what each operation actually takes out.

  • Total gastrectomy: Here the whole stomach goes, top to bottom, cardia and pylorus included. The food pipe is joined directly to the small intestine.
  • Subtotal gastrectomy: A good part of the lower stomach is taken out together with the pylorus. What remains, a small upper pouch, is joined to the intestine.
  • Lymph nodes: Neither operation is only about the stomach. The glands lying along its curves are cleared as well, since that is where the disease tends to travel first.
  • Reconstruction: The intestine has to be reconnected after the stomach is out, otherwise food has nowhere to go. How? That depends on how much stomach is left.
  • Proximal gastrectomy: Ever heard of a proximal gastrectomy? Only the upper stomach is removed. It is rare. Only a few early tumours high up are suitable for it.

Total vs Subtotal Gastrectomy: What Decides the Extent?

What does the oncology team look at? A few things, and always together.

  • Tumour location: Low in the stomach? Then a subtotal gastrectomy is often possible. Middle or upper stomach? You’re more likely to need a total gastrectomy.
  • A clear margin: The cut edge must be free of cancer. If a clear margin cannot be reached by removing only the lower stomach, the surgeon moves to a total gastrectomy. A frozen section, reported while you are still on the table, is sometimes sent to check.
  • Size and depth: Big tumours need a wider cut, and so do tumours that have grown deep into the wall. Sometimes that leaves too little healthy stomach worth keeping.
  • Pattern of spread: Some cancers, the diffuse type for instance, spread along the stomach wall. What you see on the surface may not show how far they have gone. So a larger resection may be needed.
  • Nearby organs: If the tumour has reached the pancreas and surgery needs to remove part of it along with the spleen, a total gastrectomy is advised, wherever the tumour began.

What Determines Recovery and Nutritional Needs After Gastrectomy?

Recovery after gastrectomy depends on how much of the stomach is removed, the patient’s nutritional status and how well the body adapts to changes in digestion.

  • Extent of surgery: After subtotal gastrectomy, some stomach capacity remains. Total gastrectomy requires the digestive system to adapt to food passing directly from the oesophagus into the small intestine.

  • Meal planning: Small, frequent meals may help patients manage reduced food capacity and maintain adequate nutrition.

  • Vitamin and mineral levels: Vitamin B12 replacement is necessary after total gastrectomy. Iron, calcium and other nutritional levels may also need monitoring.

  • Digestive symptoms: Some patients experience dumping syndrome, cramps, sweating or diarrhoea after meals. Dietary adjustments can help manage these symptoms.

  • Follow-up care: Regular medical reviews, blood tests, weight monitoring and nutritional assessment help identify deficiencies and support recovery.

Key Takeaways

  • Total gastrectomy means the whole stomach is removed; subtotal removes only the lower part.
  • Where the tumour is, how big and deep it is, and how it spreads decide total vs subtotal gastrectomy.
  • Removing all the cancer comes before saving stomach.
  • Your surgeon may switch from subtotal to total during the operation if the margin isn’t clear.
  • Eating and vitamin B12 needs change after both operations, so follow-up matters.


Frequently Asked Questions

Is subtotal gastrectomy always safer?

Not always. A clear margin matters more than how much stomach is saved.

Can the surgeon change the plan during the operation?

Yes. If the margin isn’t clear, more is removed

Can I live without a stomach?

Yes, with small meals, diet advice and vitamin B12 replacement.

Is subtotal the same as distal gastrectomy?

Mostly. Both mean the lower stomach is removed.

References


  1. Japanese Gastric Cancer Association. Japanese gastric cancer treatment guidelines 2018 (5th edition). Gastric Cancer. 2021;24(1):1-21. https://pmc.ncbi.nlm.nih.gov/articles/PMC7790804/
  2. Impact of Surgical Margins on Overall Survival after Gastrectomy for Gastric Cancer: A Validation of Japanese Gastric Cancer Association Guidelines on a Western Series. https://pmc.ncbi.nlm.nih.gov/articles/PMC8989928/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
What Is the Peritoneal Cancer Index (PCI), and Who Qualifies for Cytoreductive Surgery with HIPEC?

What Is the Peritoneal Cancer Index (PCI), and Who Qualifies for Cytoreductive Surgery with HIPEC?

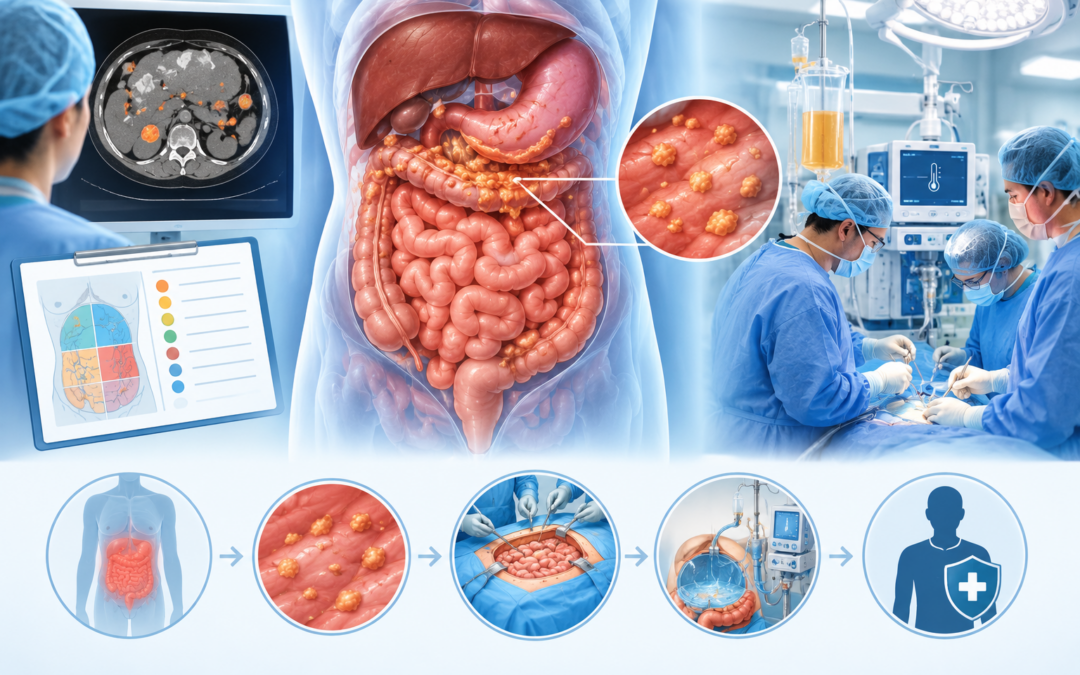
When cancer spreads to the peritoneum, the lining of the abdomen, the surgical team needs an objective way to measure it. The peritoneal cancer index (PCI) does that by scoring how much disease is present and how widely it has spread. It is one of the first things assessed when deciding whether cytoreductive surgery with HIPEC is a realistic option, though it is never the only factor.

According to Dr. Sandeep Nayak, a surgical oncologist in Bangalore, the number alone doesn’t settle anything. The scans, the type of cancer, how fit the patient is and what can actually be removed all go into the decision, and the final score is often confirmed only once the surgeon looks inside.

If you have a scan or biopsy report that shows spread in the abdomen and you’d like it explained, you can contact  Clinic on +91 9482202240.

What the Peritoneal Cancer Index Measure?

Before anyone talks about HIPEC treatment, the first question is how far the disease has gone. The PCI is how that gets answered.

Thirteen regions: The surgeon divides the abdomen into 13 areas. Nine cover the abdomen and pelvis, and four cover the small bowel.

Lesion size score: Each area gets a score from 0 to 3, based on the biggest tumour deposit in it. Zero means nothing visible. A 3 means deposits bigger than 5 cm, or disease that has joined up into one sheet.

Total score: Add the 13 scores together and you land somewhere between 0 and 39. More disease, higher number.

How it’s measured: A scan gives you an estimate. The most reliable PCI is the one the surgeon sees with their own eyes at the start of the operation.

Completeness score: Once the surgery is done, a separate CC score records how much disease was left behind. The aim is CC-0 or CC-1.

Who Qualifies for Cytoreductive Surgery with HIPEC?

No single number decides this. The oncology team looks at several things together.

Where the cancer began: Cancers of the appendix, colon, ovary and the peritoneum itself are the usual ones considered. Stomach cancer comes into it in selected cases.

The PCI range: In colon and rectal cancer, a PCI above about 20 is usually seen as too high for surgery. Other cancers use different cut-offs, and in ovarian cancer the PCI isn’t a fixed rule.

Can it all come out? This is the real question. Can the surgeon remove all the visible disease and finish with a CC-0 or CC-1 result? If not, the operation usually doesn’t go ahead.

Fitness: It’s a long, major operation. How active you are day to day matters, and so do your heart, lungs, kidneys and liver.

Spread outside the abdomen: Disease that stays within the peritoneum is the ideal. Spread to distant organs, or deposits in places that can’t be removed, can rule surgery out even when the PCI is low.

Beyond the PCI Score: Assessment and What to Expect?

Scans can miss small deposits, so the team sometimes wants a direct look inside the abdomen. A staging laparoscopy, which falls under laparoscopic cancer surgery, does exactly that.

Scans first: A CT or PET-CT of the abdomen and pelvis gives an early estimate of the PCI. Small deposits, especially on the surface of the bowel, are easy to miss.

Staging laparoscopy: A few small cuts and a camera, so the surgeon can see all 13 regions. They can score the PCI and judge whether complete removal is possible.

The plan can change: The score in the operating theatre may differ from the scan estimate, and the plan shifts with it.

The operation: Cytoreductive surgery removes all the visible disease. HIPEC follows, with heated chemotherapy circulated inside the abdomen for a set time to treat whatever can’t be seen.

Recovery: It’s a major operation, so expect a hospital stay, nutrition support and regular follow-up scans. Your team will explain what applies to you.

Key Takeaways

  • Cytoreductive surgery: Removes all visible cancer deposits where complete removal is feasible.

  • HIPEC: Heated chemotherapy is circulated inside the abdomen for a set period to treat remaining microscopic cancer cells.

  • Recovery: Recovery may involve a hospital stay, nutritional support and regular follow-up scans. The care team will guide patients based on their individual needs.

Frequently Asked Questions

Is a high PCI always a reason to avoid surgery?

Not always, since the cut-off depends on the type of cancer.

What is the range of the PCI score?

From 0, meaning no visible disease, up to 39.

Can the PCI be worked out from a scan alone?

Only roughly, because the surgeon’s direct view is more accurate.

Is HIPEC given on its own?

Usually not. It follows cytoreductive surgery that removes the visible disease.

References


Peritoneal Cancer Index and Patient Selection for CRS and HIPEC Explains how PCI measures the extent and distribution of peritoneal disease and how it helps assess suitability for cytoreductive surgery. Read the reference – PubMed Central

 Indications for Cytoreductive Surgery and HIPEC: Clinical Practice Guideline Reviews evidence and recommendations for CRS with HIPEC across ovarian, colorectal, gastric and other peritoneal cancers. Read the reference – Current Oncology / PMC

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
VATS vs RATS vs Open Thoracotomy: What Are the Differences?

VATS vs RATS vs Open Thoracotomy: What Are the Differences?

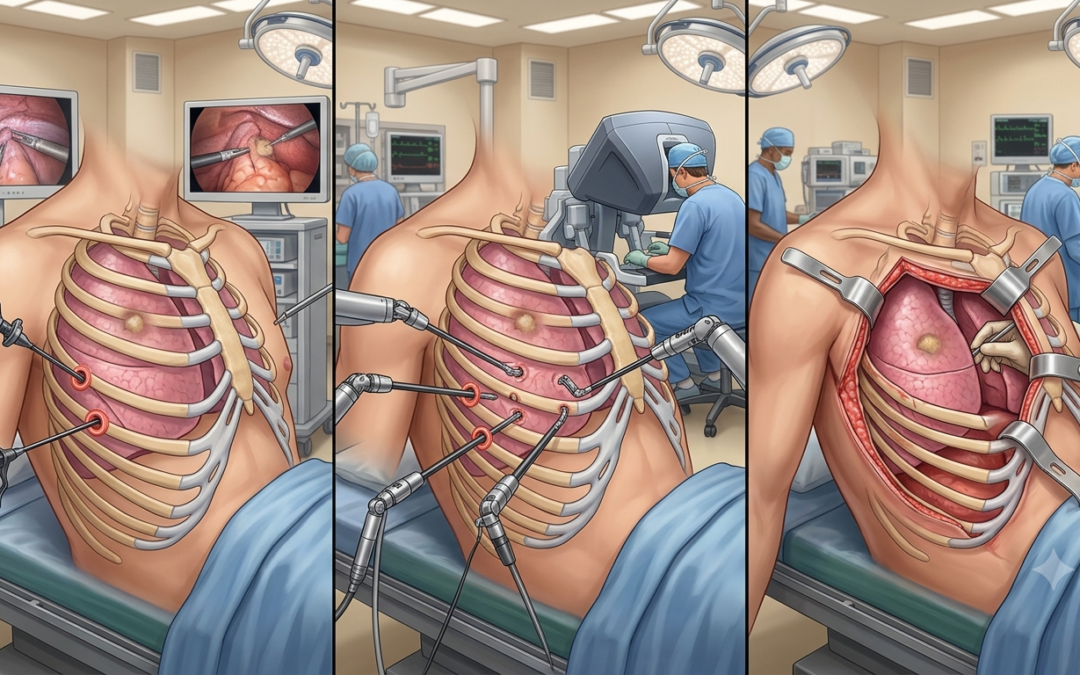
The three approaches differ mainly in the size of the cut and in how the surgeon sees and works inside the chest. Open thoracotomy uses one larger incision. VATS uses small cuts, a camera and long instruments, and RATS adds a robotic console with a three dimensional view. All three are used for lung cancer resections, including lobectomy. The right choice depends on the tumour, the patient’s health and the team’s experience.

According to Dr. Sandeep Nayak, a surgical oncologist in India, the choice between VATS vs RATS and open thoracotomy for lung cancer surgery depends on the tumour. “The approach is chosen to suit the tumour. Each one can remove a lung cancer completely when it is used in the right patient. Smaller cuts usually mean less pain and a quicker recovery. Some tumours still need an open operation to be removed safely. The route is only a means to the goal, and the goal is complete removal 

For information about lung surgery options, you can contact the clinic at +91 9482202240.

What Are Open Thoracotomy, VATS and RATS?

All three reach the lung through the chest wall, but the access and the tools differ.

Open thoracotomy: One larger incision between the ribs, with the ribs spread for access. The surgeon works looking directly at the lung.

VATS: A few small cuts between the ribs. A camera and long instruments are used, and the surgeon works from a screen. The full name is video-assisted thoracoscopic surgery.

RATS: Small cuts again, this time with a robotic console. The surgeon controls the instruments from the console and sees a magnified three dimensional view. The instruments bend and rotate more freely than straight VATS tools.

What they can treat: All three can be used for lobectomy, segmentectomy and wedge resection, depending on the tumour.

The same operation by a different route: In principle the tumour and the lymph nodes are removed in each case. Only the way in changes. Our page on lung cancer treatment covers the operations used.

How Do the Three Approaches Compare?

The table sets out the main differences side by side.

Feature

Open thoracotomy

VATS

RATS

Incision

One larger incision

A few small incisions

A few small incisions

View

Direct view

Camera view on a screen

Magnified three dimensional view

Instruments

Handheld

Long handheld instruments

Robotic arms with bending wrists

Pain and recovery

More pain, slower recovery

Less pain, quicker recovery than open surgery

Similar to VATS

Lymph nodes removed

Standard

Standard

Slightly more in some studies

VATS vs open: Trials found less pain and better quality of life after VATS, and long term survival wasn’t significantly different. Our blog on VATS surgery for lung cancer explains how it works.

RATS vs VATS: A pooled analysis of randomised trials found equivalent cancer and complication outcomes. RATS showed less blood loss and more lymph nodes removed, but that hasn’t translated into better survival.

Cost: Robotic systems generally cost more to buy and run, so RATS usually costs more.

Switching during surgery: Any keyhole operation can be changed to open surgery if it isn’t safe to continue. It’s a safety step, not a failure.

What Determines Treatment Choice?

The choice is made case by case, using a few clear points.

Tumour size and position: Small tumours away from the main blood vessels suit keyhole surgery. Large tumours, or those close to the main vessels or airway, can make open surgery safer.

Spread: Tumours growing into the chest wall or nearby structures, or heavily involved lymph nodes, may need an open operation.

Earlier chest surgery or infection: Heavy scarring inside the chest can make keyhole access difficult.

Lung function and general health: Fitness for anaesthesia and surgery shapes how much lung can be removed and by which route. Our blog on whether lung cancer surgery removes the whole lung explains how much may come out.

Team experience and availability: Results depend on how often the team performs the chosen approach. Robotic surgery is available only at some centres.

Key Takeaways

  • Open thoracotomy uses one larger incision. VATS and RATS use small cuts with a camera, and RATS adds a robotic console.
  • Compared with open surgery, VATS usually means less pain and a quicker recovery, without worse cancer outcomes in suitable patients.
  • Pooled randomised trials found RATS and VATS to be equivalent for cancer and complication outcomes, and RATS usually costs more.
  • Some tumours still need open surgery. The right approach depends on the tumour, the patient’s health and the team’s experience, and is best discussed with a specialist.

Frequently Asked Questions

What is the main difference between VATS and RATS?

RATS uses a robotic console with a three dimensional view. VATS uses handheld instruments.

Is VATS as effective as open surgery for lung cancer?

Trials show similar cancer outcomes in suitable patients, with less pain and quicker recovery.

Does robotic surgery give better results than VATS?

Not clearly. Pooled randomised trials found equivalent cancer outcomes and complication rates.

When is open thoracotomy still needed?

For some large, central or advanced tumours, or when keyhole surgery isn’t safe.

References


  1. PubMed — Long-term survival from a randomized controlled trial of lobectomy by video-assisted thoracoscopic surgery versus thoracotomy for early-stage lung cancer: https://pubmed.ncbi.nlm.nih.gov/39873729/
  2. National Center for Biotechnology Information — Robotic vs. video-assisted thoracoscopic surgery for resectable non-small cell lung cancer: a systematic review and meta-analysis of randomized controlled trials: https://pmc.ncbi.nlm.nih.gov/articles/PMC13460117/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
Lobectomy vs Segmentectomy vs Wedge Resection for Lung Cancer: How the Surgical Options Differ

Lobectomy vs Segmentectomy vs Wedge Resection for Lung Cancer: How the Surgical Options Differ

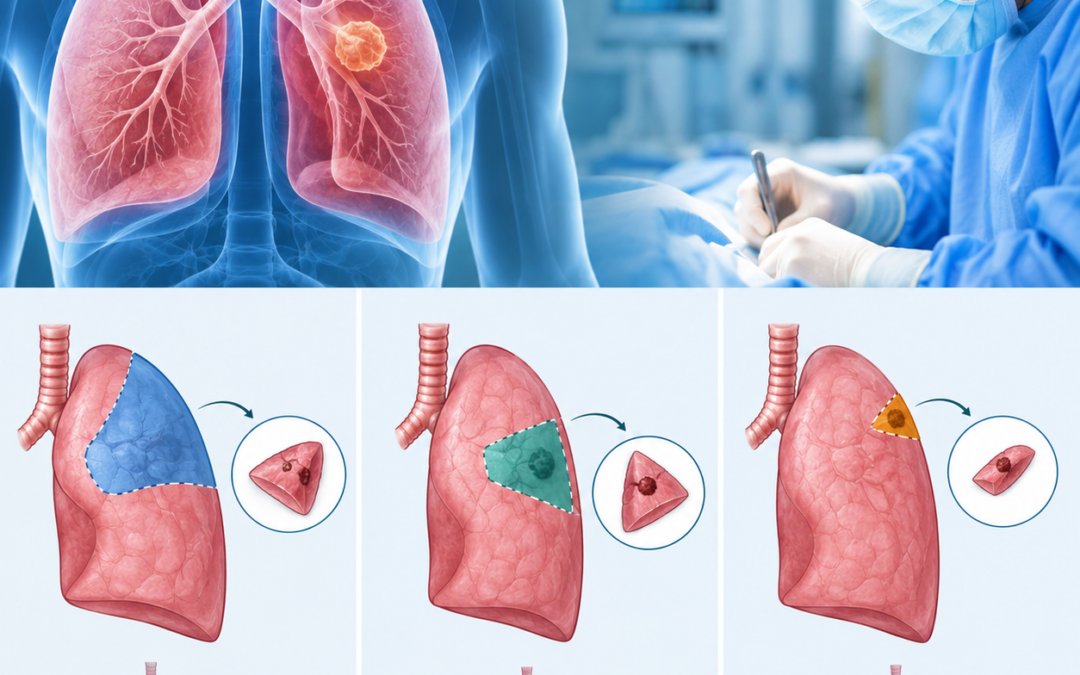
Most people hear “lung cancer surgery” and picture one operation. There are really three common ones, and what separates them is simple: how much lung leaves the body. A lobectomy takes a whole lobe. A segmentectomy takes a smaller piece of a lobe, a self-contained section with its own airway and blood supply. A wedge resection takes a small chunk around the tumour and doesn’t follow any of the lung’s natural lines.

Dr. Sandeep Nayak, a surgical oncologist in India, puts it this way: the operation should be cut to fit the tumour and the lungs, not the other way round. He won’t suggest a plan until the scans, the lymph node findings and the breathing tests are all on the table together.”

Confused by your scan or biopsy report? Call  Clinic on +91 9482202240.

What Lobectomy, Segmentectomy and Wedge Resection Remove?

When the cancer hasn’t left the lung, surgery is usually the first option on the table in lung cancer treatment. Think of the lung as a tree. A lobectomy takes off a whole major branch. A segmentectomy prunes a smaller limb at the point where it joins. A wedge resection just cuts out the damaged part without worrying about where the branches split.

A lobectomy is the long-standing standard. The right lung has three lobes and the left has two, and the surgeon removes the one that holds the tumour. It’s the biggest of the three, and for years it was the default for any operable early cancer.

A segmentectomy is trickier to perform. The surgeon has to find that segment’s own bronchus, artery and vein, divide them one by one, and lift the segment out cleanly. The reward is that more healthy lung stays behind.

A wedge resection is the quickest and smallest. A stapling device cuts a wedge out and seals the edge as it goes. The catch is that nothing guarantees a generous rim of healthy tissue, so it depends heavily on where the tumour sits.

In all three, nearby lymph nodes are usually sampled or removed. What they show can change what happens next, so the surgeon doesn’t skip them.

And the technique is a separate question from the extent. Open surgery, VATS keyhole surgery or a robot can be used for any of the three.

Lobectomy vs Segmentectomy: What Guides the Choice?

Picture a typical case. A patient in their sixties has a 1.5 cm nodule near the outer edge of one lung, the lymph nodes look clear, and breathing tests are on the weak side after years of smoking. For that person, a segmentectomy often makes more sense than a lobectomy. Change one detail, say the nodule is 3.5 cm and close to the main airway, and the answer flips.

So what actually tips the decision?

Size and position matter most. Small tumours of around 2 cm or less in the outer lung are the best candidates for a smaller operation. Large ones, or ones near the centre of the chest, usually aren’t.

Lymph nodes come next. If they look involved on a scan, or turn out to be involved during surgery, the surgeon will often move to a lobectomy and clear the nodes more thoroughly.

The look of the tumour on CT counts too. A hazy “ground glass” appearance often means slow growth, which can justify taking less lung.

Then there’s the patient. Weak breathing reserve, heart trouble or other illness can make a smaller operation the safer choice, even when a lobectomy would otherwise be on the cards.

The research backs this up for carefully chosen cases. A large randomised trial looked at tumours up to 2 cm in the outer lung with clear nodes, and patients who had a smaller resection did about as well on disease-free survival as those who had a lobectomy.

Whether surgery can cure the cancer at all depends on stage, which our guide on whether lung cancer can be cured explains.

Where Wedge Resection Fits and What to Expect After Surgery?

How you recover depends on two things: how much lung came out, and how it was done. Robotic surgery and other keyhole methods mean smaller cuts and usually an easier few weeks than an open chest operation.

Wedge resection has a narrow but real role. It works for very small nodules near the edge of the lung, for cases where the surgeon needs tissue to confirm what the nodule actually is, and for patients too frail for anything bigger.

The margin is the whole story here. Take less tissue and you need a clear rim of healthy lung around the tumour. If that rim comes back too thin, the surgeon may extend the operation to a segmentectomy or lobectomy on the spot, which is why you’ll be asked to consent to that possibility beforehand.

When researchers went back to the data from the same North American trial, wedge resection came out worse on survival than either segmentectomy or lobectomy. The two bigger operations weren’t meaningfully different from each other. That’s a big reason surgeons lean toward segmentectomy over a wedge when a smaller operation is on the table and the patient can handle it.

Key Takeaways

  • Lobectomy takes a whole lobe, segmentectomy takes one defined section of it, and wedge resection cuts out a small piece without following the lung’s structure.
  • Size, position, lymph nodes and breathing ability do most of the work when choosing between lobectomy vs segmentectomy.
  • For small tumours in the outer lung with clear nodes, smaller operations have held up well in trials.
  • Wedge resection is only as good as its margin, so it’s reserved for carefully chosen patients.
  • No one decides this from a single scan. The oncology team looks at the scans, the biopsy and the breathing tests together.

Frequently Asked Questions

Is segmentectomy as effective as lobectomy for lung cancer?

For the right patient, yes. That means a small tumour in the outer lung with clear lymph nodes. Outside that group, lobectomy is still usually the safer bet.

When is wedge resection used for lung cancer?

Mostly for very small nodules near the edge of the lung, or when a bigger operation simply wouldn’t be safe for the patient.

Does segmentectomy also remove lymph nodes?

Usually it does. The surgeon samples or removes the nearby nodes during the operation, since what they show helps decide the next step.

Can the planned lung surgery change during the operation?

It can. If the margin turns out too close, or the nodes look involved once the surgeon is inside, the operation may be extended. You’ll normally discuss this before you go in.

References


  1. NHS. Treatment for lung cancer (NHS Health A to Z). https://www.nhs.uk/conditions/lung-cancer/treatment
  2. Altorki N, Wang X, Kozono D, et al. Lobar or Sublobar Resection for Peripheral Stage IA Non-Small-Cell Lung Cancer. N Engl J Med. 2023;388(6):489-498. https://pubmed.ncbi.nlm.nih.gov/36780674/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Oral Cancer: Should Treatment Start with Surgery or Radiation?

Oral Cancer: Should Treatment Start with Surgery or Radiation?

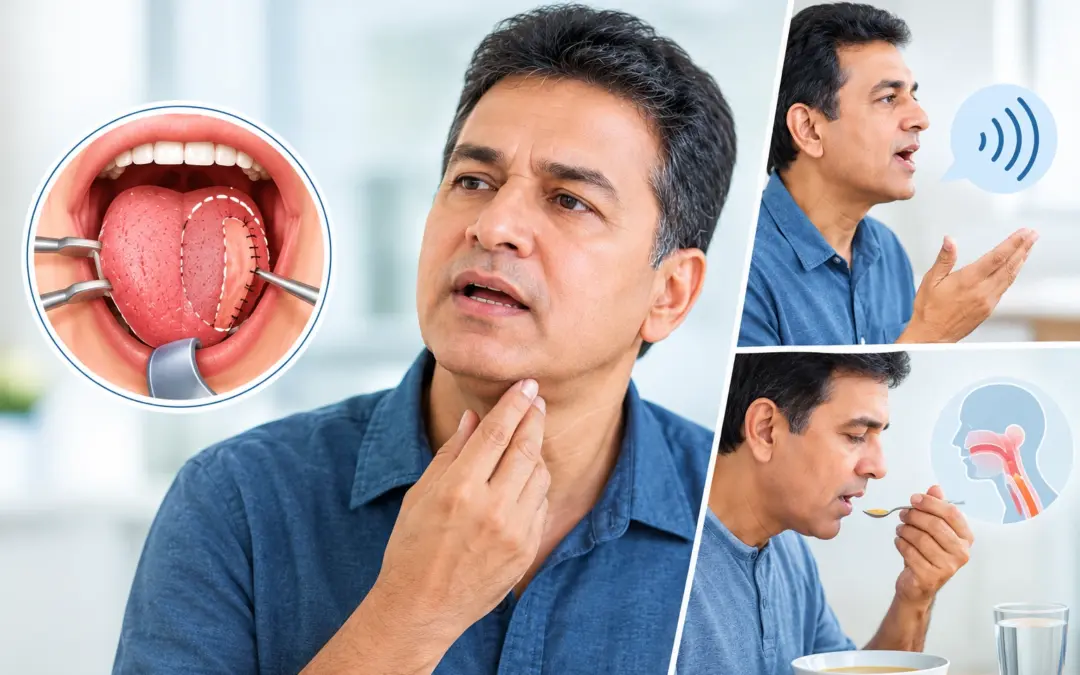
Surgery is the first and main treatment for most oral cavity cancers, including cancer of the tongue. Radiation usually comes later, after the operation, if the pathology report points to a higher risk, and it takes the lead only when surgery isn’t an option. Speech and swallowing are affected because the tongue is central to both. How much changes depends on how much of it is removed, which part, and whether it’s rebuilt.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist at MACS Clinic, Bangalore, talks patients through what to expect after a glossectomy. “The first question I get before tongue surgery is almost always the same: will I be able to talk and eat afterwards? With a small tumour, usually yes, with only a mild and brief change. If a bigger part has to go, the road is longer and rehab matters a lot. We plan the surgery and the recovery together.”


If you’d like to know more about tongue cancer surgery, call the clinic on +91 9482202240.

How Much of the Tongue Is Removed in Tongue Cancer Surgery?

That depends on the tumour: how big it is, how deep, and where it sits. The surgeon takes the cancer plus a small rim of healthy tissue around it, and tries not to take more than that.

Partial glossectomy: Most people with a small tumour on the side of the tongue need only this. A piece comes out and the rest of the tongue stays. Some of these small tumours can be reached through the mouth with robotic help, and our page on trans oral robotic surgery covers where that’s used.

Hemiglossectomy: Half the tongue. This is for larger or deeper tumours.

Total glossectomy: The whole tongue, or nearly all of it. Rare, and kept for advanced cancers.

The neck: Tongue cancer often spreads to the lymph nodes in the neck, so the surgeon usually clears those during the same operation.

Rebuilding: If a big part is taken, skin and tissue from the forearm or thigh can be used to build the tongue back up.

How Does Tongue Cancer Surgery Affect Speech?

Almost every sound you make involves the tongue. So yes, speech changes. How much is the real question.

Small removals: Many people notice very little. Some are a bit slurred for a short while, and then it settles.

Bigger removals: Clarity can drop. Sounds like t, d, l and s need the tip of the tongue to touch the roof of the mouth, so those suffer first.

Straight after surgery: Swelling makes everyone sound muffled for the first few days. It passes.

A rebuilt tongue: The tissue used to rebuild it gives the tongue enough bulk to reach the palate, and that helps with clearer sounds.

Speech therapy: This starts early. Exercises, practice, patience. Over weeks and months most people get clearer, even if it doesn’t sound exactly as it once did. Speech is a large part of head and neck cancer care, and our page on head and neck cancer treatment covers that.

What Determines Speech and Swallowing Outcomes After Tongue Cancer Surgery?

No two people recover alike. These are the things that shape it.

How big the tumour was: The more tongue that has to come out, the bigger the change.

Where it was: The tip and front mostly change how clearly you speak. The back mostly changes swallowing.

Whether it was rebuilt: And how.

Radiation afterwards: If you need it, it can leave you with a dry mouth and some stiffness, and that makes both speaking and swallowing harder.

The neck operation: In suitable cases, Dr. Nayak’s RIA-MIND approach to neck dissection is designed to cut complications and help function. You can read more on our expertise page.

Rehab: Early therapy and daily practice at home count for a great deal, and they’re as much your job as the surgeon’s.

Where you started from: Your age, your general health, and how you were speaking and eating before.

Key Takeaways

  • The tongue plays a vital role in both speech and swallowing, so surgery can affect these functions.

  • Smaller tissue removals usually cause milder changes, while larger surgeries may require longer recovery and therapy.

  • Surgical planning, reconstruction and rehabilitation help improve speech and swallowing after surgery.

  • Ask your care team what to expect based on your tumour and planned surgery.

  • To discuss your treatment options, book an appointment or call the clinic at +91 9482202240.

Frequently Asked Questions

How does tongue cancer surgery affect speech?

A small removal often changes little, while a bigger one can leave speech less clear for a time.

Can you swallow normally after tongue cancer surgery?

Many people do, though after bigger surgery you may need therapy and softer food at first.

Do you need speech therapy after a glossectomy?

Often, especially after bigger removals, and the earlier it starts the better.

Will I need a feeding tube after tongue cancer surgery?

Sometimes, briefly, after larger operations while the mouth heals.

References


National Cancer Institute (NCI) – Head and Neck Cancers: Side Effects and Rehabilitation https://www.cancer.gov/types/head-and-neck/head-neck-fact-sheet

 PubMed – Voice Rehabilitation After Tongue Cancer Surgery: A Cohort Study in Indian Population https://pubmed.ncbi.nlm.nih.gov/39559020/

Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

Call Now Button