
support@macsclinic.com
+91 9482202240
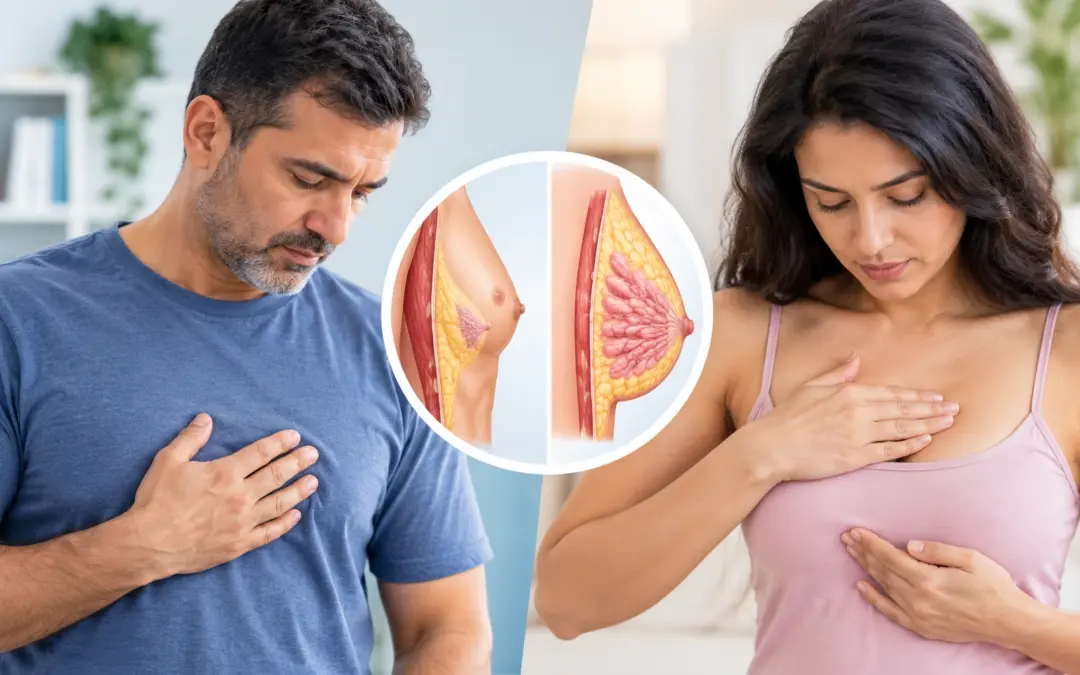
Is Male Breast Cancer Different From Female?

Is Male Breast Cancer Different From Female?

Yes, male breast cancer is biologically and clinically different from female breast cancer in several meaningful ways, even though the basic treatment approach, surgery, hormone therapy, chemotherapy where needed, shares a lot of common ground. The differences show up more in hormone receptor patterns, typical age at diagnosis, genetic risk factors, and often the stage at which it’s caught.

According to Dr. Sandeep Nayak, surgical oncologist in Bangalore with over 24 years of experience treating solid tumors, “Male breast cancer gets treated too much like a rare footnote of the female disease, and that’s genuinely a problem. It behaves differently in real ways, hormone receptor status especially, and men are often diagnosed later simply because nobody’s watching for it. That delay alone changes outcomes more than biology does in a lot of cases.”

Noticed a change in the chest area and unsure what it means?

Male vs. Female Breast Cancer, Key Differences?

Male Breast Cancer

Female Breast Cancer

Hormone receptor status

Nearly always hormone receptor-positive (ER/PR-positive)

More varied, includes hormone-negative and triple-negative types

Typical age at diagnosis

Often older, commonly 60s to 70s

Wider age range, diagnosed earlier on average

Genetic link

Strongly associated with BRCA2 mutations

Associated with both BRCA1 and BRCA2

Stage at diagnosis

Frequently caught later, less breast tissue to mask a lump

More often caught earlier through routine screening

Awareness and screening

Minimal, no routine screening programs exist

Established, structured screening guidelines

If a lump or change is what brought you here, our Breast Cancer treatment page covers the diagnostic and treatment pathway that applies regardless of gender.

Why These Differences Actually Matter?

  • Because male breast cancer is so consistently hormone receptor-positive, hormone therapy plays an even more central role in treatment than it sometimes does for women.
  • BRCA2 mutations show up disproportionately often in male breast cancer, which makes genetic counselling and family testing a bigger part of the conversation.
  • Later-stage diagnosis in men isn’t due to a more aggressive disease, it largely comes down to lower awareness and no routine screening prompting an earlier look.
  • Treatment protocols, surgery, radiation, hormone therapy, largely mirror female breast cancer treatment, adapted where male-specific biology calls for it.

We covered the basic awareness side of this question separately in Can Men Get Breast Cancer?, worth reading first if this is a new area for you.

Why Choose Prof. Dr. Sandeep Nayak?

Dr. Sandeep Nayakhas spent more than two decades in surgical oncology, and breast cancer, including the far less commonly discussed male presentation, has been a consistent part of that work throughout. He currently serves as Chairman of Oncology Services for Karnataka and heads Surgical Oncology and Robotic Surgery at KIMS Hospital, Bangalore. What tends to matter most to patients isn’t the title though, it’s that male breast cancer gets taken as seriously and diagnosed as promptly as it would be in a woman, not dismissed or delayed because it’s rare. That seriousness is often where things get missed elsewhere.

Noticed something unusual and unsure if it’s worth getting checked? It is. Call +91 9482202240 and get someone to actually walk you through it.

Frequently Asked Questions

Is male breast cancer more aggressive than female breast cancer?

Not inherently more aggressive, no. The later stage at diagnosis, driven by lower awareness, is usually what affects outcomes more than the biology itself.

Should male relatives get genetic testing if a family member has BRCA2?

After, at present, and only for people whose pathology shows a higher risk of recurrence. Using it before surgery is still being studied.

Is treatment the same for men and women?

Largely similar in approach, surgery, hormone therapy, radiation where needed, though hormone therapy plays a slightly larger role given how consistently hormone receptor-positive male breast cancer tends to be.

Why is male breast cancer usually caught later?

Mainly due to low awareness and no routine screening, not because the disease itself grows faster or behaves more aggressively.

References


    Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
    Immunotherapy vs Surgery for Kidney Cancer?

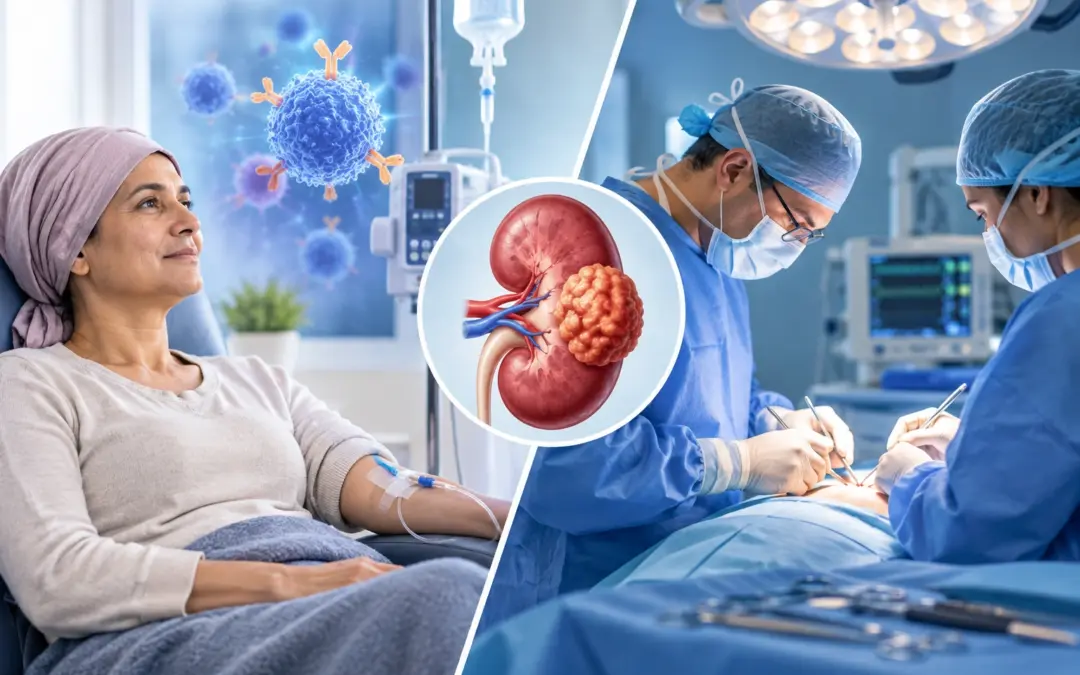
    Immunotherapy vs Surgery for Kidney Cancer?

    If the tumour is still confined to the kidney, surgery is what cures it, and no drug regimen has taken that job over outside clinical trials. Where immunotherapy does matter is around the operation: after it, for people whose pathology looks high risk, and as the main treatment once the cancer has spread.

    According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India, “The question I hear most is whether a drug can save the operation. For a tumour still inside the kidney, no. Immunotherapy earns its place when the risk of the cancer coming back is high, or when it has already left the kidney.” 

    Not sure whether your scan points to an operation or a drug?

    When Is Surgery Still the First Choice?

    • If the cancer hasn’t left the kidney, taking it out is the treatment with a cure in mind. That hasn’t changed. This is what kidney cancer surgery is built around at this stage.
    • Smaller tumours in a good position can often be removed with a partial nephrectomy, so the rest of the kidney keeps working. That matters more than people expect, especially years later.
    • Big tumours, or ones that have grown into the renal vein, may need the whole kidney out. Robotic or laparoscopic routes are used when the anatomy allows, our robotic cancer surgery approach covers how that access actually works.
    • Very small masses in older or frail patients? Sometimes we watch, or use ablation. But only after the imaging has been looked at properly.

    Where Does Immunotherapy Fit In?

    • After surgery, for selected high-risk patients. A year of pembrolizumab has been shown to lower the chance of recurrence, with longer follow-up suggesting a survival benefit too.
    • When the cancer has spread, it has become the backbone of treatment, usually as a combination of two immunotherapy drugs or one paired with a targeted tablet. 
    • Do these patients still need surgery? Sometimes, but not automatically. Removing the kidney in advanced disease is decided case by case, and many people start with drugs first. This is where a surgical oncologist’s judgement counts.
    • Side effects deserve respect. Immunotherapy can inflame the thyroid, gut, liver, skin or lungs, so a new symptom should be reported early rather than at the next visit.

    Why Choose Prof. Dr. Sandeep Nayak?

    Prof. Dr. Sandeep Nayak has performed over 10,200 cancer surgeries across 24 years , including robotic and laparoscopic work where saving kidney tissue matters. Treatment plans are reviewed at a tumour board, so the choice between surgery, immunotherapy or both isn’t one person’s hunch.Bring your CT report and any biopsy or pathology report to the first visit. Staging answers most of this question before we discuss anything else.

    Frequently Asked Questions

    Can immunotherapy get rid of kidney cancer without an operation?

    For a tumour still inside the kidney, not reliably. Surgery remains the standard, and skipping it for drugs alone is something to consider only within a clinical trial.

    Is immunotherapy given before or after the operation?

    After, at present, and only for people whose pathology shows a higher risk of recurrence. Using it before surgery is still being studied.

    If my cancer has spread, is surgery off the table?

    Not necessarily. It depends on how much disease there is and how you respond to drug treatment, so the decision is usually made jointly with a medical oncologist.

    Are the side effects worse than surgery?

    They’re different, not milder. Rashes, thyroid changes, diarrhoea and inflammation of the liver or lungs can happen, and most are manageable when caught early.

    References

    Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
    Can Stomach Cancer Be Treated Without Full Removal? | Dr. Nayak

    Can Stomach Cancer Be Treated Without Full Removal? | Dr. Nayak

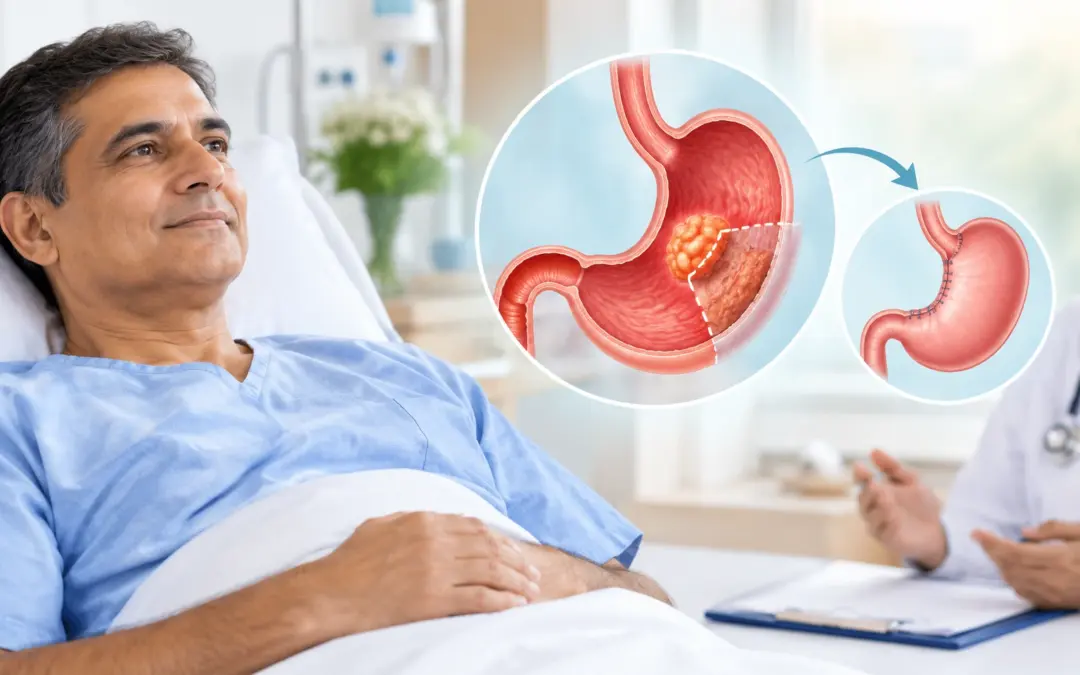
    Yes, stomach cancer treatment without full stomach removal may be possible in some cases, but it depends largely on how early the cancer is detected and how deeply it has grown into the stomach wall. Early-stage cancers confined to the lower or upper portion of the stomach can often be treated with a partial gastrectomy, which removes only the affected section rather than the entire stomach.

    According to Dr. Sandeep Nayak, surgical oncologist in Bangalore with over 24 years of experience treating solid tumors, “Patients assume a stomach cancer diagnosis automatically means losing the whole stomach, and that fear stops some of them from even getting evaluated properly. Location and depth decide this, not the diagnosis itself. A tumour confined to one part of the stomach, caught early, often doesn’t need total removal at all.”

    Diagnosed with stomach cancer and unsure if full removal is really necessary? Book Appointment

    Partial vs. Total Gastrectomy, What Decides Which?

    Partial Gastrectomy

    Total Gastrectomy

    When it’s used

    Tumour confined to lower or upper stomach

    Tumour spans a large portion or is centrally located

    How much is removed

    Affected portion only, rest reconnected

    Entire stomach, oesophagus connected to small intestine

    Eating afterward

    Smaller meals, largely normal digestion over time

    Bigger adjustment, smaller frequent meals become essential

    Best candidates

    Early-stage, localised disease

    Larger, more advanced, or multi-site tumours

    Recovery

    Generally shorter

    Longer adjustment period, ongoing nutritional monitoring

    This decision runs through the same Stomach and Oesophageal Cancer treatment pathway, where imaging and staging determine which approach actually applies to a given case.

    What Actually Gets Assessed Before Deciding?

    • Tumour location matters most, cancers in the lower stomach are far more likely to be candidates for partial removal than ones in the middle or spanning multiple regions.
    • Depth of invasion into the stomach wall changes the calculation significantly, deeper invasion generally pushes toward more extensive removal.
    • Lymph node involvement, checked during staging, factors heavily into how much surrounding tissue needs to come out along with the tumour.
    • Overall health and nutritional status also weigh into what a patient can safely tolerate and recover well from.

    This staging and decision process ties closely into how laparoscopic and minimally invasive approaches are increasingly used for early and locally advanced gastric cancer, worth reading if you’re weighing surgical approach as well as extent of removal.

    Why Choose Dr. Sandeep Nayak for Cancer Care in Bangalore??

    Dr. Sandeep Nayak has spent more than two decades in surgical oncology, and stomach cancer cases, from early localised disease to more extensive tumours, have been part of that work throughout. He currently serves as Chairman of Oncology Services for Karnataka and heads Surgical Oncology and Robotic Surgery at KIMS Hospital, Bangalore. What tends to matter most to patients isn’t the title though, it’s that the extent of surgery gets decided by what the disease actually requires, not by defaulting to the most extensive option out of caution. That precision is often where things get missed elsewhere.

    Not sure if your case allows for partial removal instead of the whole stomach? Get clarity before assuming the worst. Call +91 9482202240 and get someone to actually walk you through it.

    Frequently Asked Questions

    Can I eat normally after a partial gastrectomy?

    Largely yes, over time. Smaller, more frequent meals become the norm initially, but most patients adjust well within a few months.

    Does a smaller surgery mean a lower chance of cure?

    Not if it’s the right fit for the case. Partial gastrectomy for appropriately staged, localised disease achieves similar outcomes to total removal in the right candidates.

    How is the decision between partial and total gastrectomy made?

    Through imaging, endoscopic evaluation, and often confirmed further during surgery itself, tumour location and depth are the main deciding factors.

    Is nutritional support needed after either type of surgery?

    Yes, though total gastrectomy typically needs more structured long-term nutritional monitoring compared to partial removal.

    References

    Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.
    What Are Leukoplakia and Other Pre-Cancerous Mouth Lesions?

    What Are Leukoplakia and Other Pre-Cancerous Mouth Lesions?

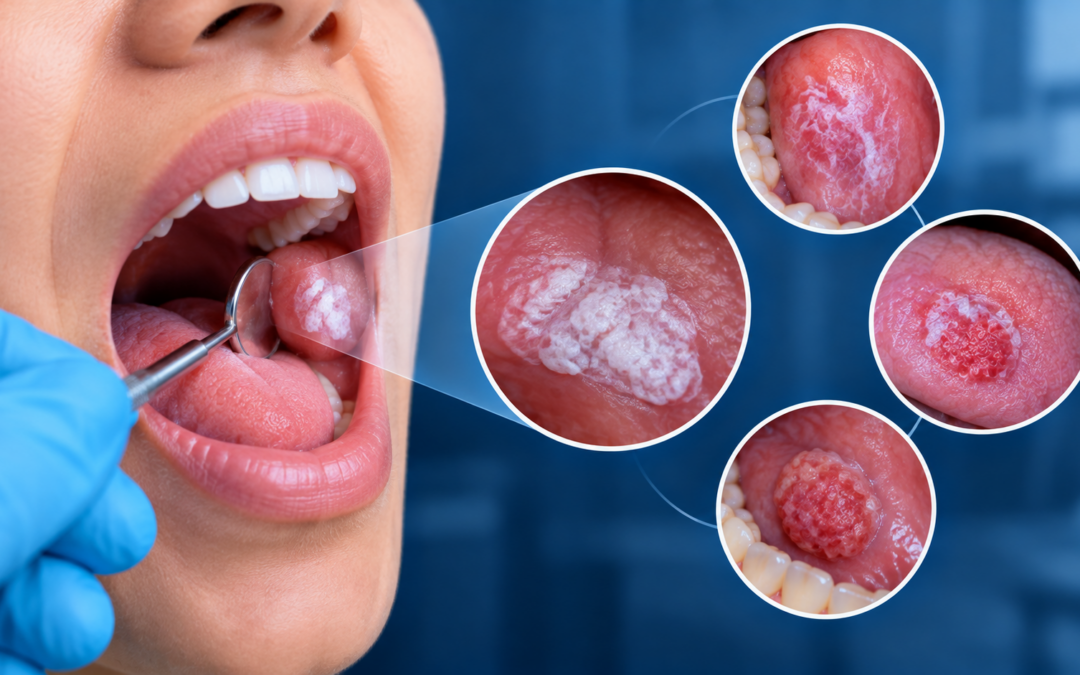
    Leukoplakia isn’t the precancerous patch worth worrying about. There’s a family of these called oral potentially malignant disorders and some carry far more risk than leukoplakia ever does. Erythroplakia, the version transforms into cancer in roughly 20 to 33 percent of cases. Oral submucous fibrosis, tied closely to gutka and areca nut chewing sits around 6 to 8 percent in populations. Lichen planus is milder usually. Still needs watching. Different lesions. Different risk. Same underlying message: get it checked.

    According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India “erythroplakia gets less attention than leukoplakia and thats backwards it’s actually the more dangerous lesion of the two and its exactly the kind of thing patients dismiss as just a red patch.”

    Noticed a patch stiffness in your cheek or lacy white lines that won’t go away?

    What Are the Other Precancerous Lesions Besides Leukoplakia?

    Leukoplakia gets most of the attention. It’s not actually the dangerous one.

    • Erythroplakia : A red patch, not white on the soft palate or floor of the mouth. Malignant transformation runs 20 to 33 percent, times higher than leukoplakia.
    • Oral Submucous Fibrosis : Tied entirely to gutka and areca nut chewing. Mouth opening gets progressively tighter. It doesn’t reverse even after quitting.
    • Oral Lichen Planus : Lacy lines sometimes painful an autoimmune condition rather than a tobacco-driven one. Lower risk still needs monitoring.
    • Actinic Cheilitis : Sun-damaged lips, dry and scaly the lower lip. Common in workers easy to miss for years.

    Getting any of these properly assessed is a job for oral cancer specialists, not a wait-and-see approach at home.

    Which of These Lesions Actually Needs the Concern?

    Risk isn’t equal across these four. Not even close.

    • Highest Risk : Erythroplakia. One in three eventually becomes cancer. It’s the one most likely to already be cancer at biopsy.
    • India-Specific Risk : Oral submucous fibrosis, because of how common gutka and areca nut use actually is here. Some regional data pushes transformation risk higher than the global average.
    • Lower But Real Risk : Lichen planus sits lowest of the group, around 1 to 2 percent but zero risk it is not.
    • The Overlap Problem : Having than one of these at once say fibrosis alongside leukoplakia pushes risk higher than either alone.

    Leukoplakia itself the common of these is covered in detail separately alongside the other causes of white patches worth ruling out first.

    Why Choose Dr. Sandeep Nayak for Oral Cancer Treatment?

    Prof. Dr. Sandeep Nayak treats the spectrum of oral and head and neck cancers including cases that start as precancerous lesions like these. Trans-oral robotic surgery available for base of tongue and oropharyngeal tumours. Neck dissection built into the plan when needed not added later. Heads Oncology Services across Karnataka.

    Catching erythroplakia or fibrosis before it turns is a different conversation than treating it after. Call +91-9482202240 to book your consultation.

    Frequently Asked Questions

    Is Erythroplakia more dangerous than Leukoplakia?

    Yes, its malignant transformation rate runs higher around 20 to 33 percent.

    What causes submucous fibrosis?

    Chewing Gutka, Areca nut or Betel quid over a period.

    Can oral submucous fibrosis be reversed by quitting?

    No the fibrosis itself doesn’t reverse, though quitting still lowers risk.

    Is lichen planus caused by tobacco?

    No it’s a condition unrelated, to tobacco or alcohol use.

    References

    1. PubMed, Malignant Transformation Rates of Oral Potentially Malignant Disorders
    2. PMC, Malignant Transformation Rate of Oral Submucous Fibrosis: A Systematic Review and Meta-Analysis

    Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

    Does Hepatitis B or C Increase Liver Cancer Risk?

    Does Hepatitis B or C Increase Liver Cancer Risk?

    Yes, and the numbers are hard to ignore. Hepatitis B accounts for roughly 40 to 50 percent of liver cancer cases in India, hepatitis C for another 12 to 32 percent. Together, these two viruses sit behind the majority of hepatocellular carcinoma diagnosed in the country. One hospital-based study found the risk of liver cancer jumped more than fourteen-fold in hepatitis B positive men compared to the general population. Cirrhosis usually comes first. Cancer, for a lot of these patients, comes after.

    According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India, “hepatitis doesn’t just damage the liver quietly for years, it rewires the risk entirely, which is why every hepatitis B or C patient needs liver cancer screening built into their routine care, not an afterthought.”

    Living with hepatitis B or C and never been screened for liver cancer?

    How Much Does Hepatitis Actually Raise Liver Cancer Risk?

    Big numbers. Bigger than most people realize until they see them written down.

    • Hepatitis B : Close to half of all liver cancer cases in India trace back to hepatitis B, somewhere between 40 and 50 percent depending on the study.
    • Hepatitis C : Smaller share, still huge. 12 to 32 percent of cases, and that range keeps shifting as more data comes in.
    • The Multiplier : One Tata Memorial study found hepatitis B positive men were over fourteen times more likely to get liver cancer. Fourteen times.
    • Cirrhosis First : Most of these cancers don’t appear out of nowhere. Roughly 80 percent show up in a liver that’s already cirrhotic.

    Regular liver cancer screening with AFP blood tests and ultrasound is what actually catches this early, while surgery is still on the table.

    What Should Someone With Hepatitis Actually Do About This?

    Knowing the risk is one thing. Acting on it is the part that saves lives.

    • Six-Monthly Screening : AFP testing and liver ultrasound every six months, that’s the global standard for anyone with chronic hepatitis B or C.
    • Antiviral Treatment : Suppressing the virus itself lowers cancer risk over time. It doesn’t erase it, but it helps, meaningfully.
    • Family Screening : Hepatitis B spreads within families. So relatives of a known carrier should get tested too, not just the patient.
    • Don’t Wait for Symptoms : By the time hepatitis-related liver cancer causes symptoms, it’s often already advanced. Screening exists precisely for that gap.

    That screening gap is exactly what gets closed with structured surveillance, covered in more detail in early detection of liver cancer.

    Why Choose Dr. Sandeep Nayak for Liver Cancer Treatment?

    Prof. Dr. Sandeep Nayak brings over 24 years of surgical oncology experience to liver cancer, including laparoscopic and robotic-assisted hepatic resection at KIMS Hospital, Bangalore. Heads Oncology Services across Karnataka. Every hepatitis-positive patient gets AFP testing and imaging built into their care from the start, not added later. Every case reviewed through tumour board.

    Patients with known hepatitis B or C get watched closely here, because waiting is exactly what this disease counts on. Call +91-9482202240 to book your consultation.

    Frequently Asked Questions

    Does hepatitis B cause liver cancer?

    It’s linked to roughly 40 to 50 percent of liver cancer cases in India.

    Does hepatitis C also increase liver cancer risk?

    Yes, hepatitis C accounts for another 12 to 32 percent of cases in India.

    How often should hepatitis patients be screened for liver cancer?

    Every six months, using AFP blood tests and liver ultrasound imaging.

    Can treating hepatitis lower liver cancer risk?

    Yes, antiviral treatment meaningfully reduces risk, though it doesn’t eliminate it.

    References

    1. Spectrum of Hepatitis B and Hepatitis C-Related Cancers in India, PubMed
    2. World Health Organization, Hepatitis B Fact Sheet

    Disclaimer: This blog is for informational and educational purposes only and is not a substitute for professional medical advice or diagnosis.

    Call Now Button