
support@macsclinic.com
+91 9482202240
Is Esophageal Cancer Operable After Chemo?

Is Esophageal Cancer Operable After Chemo?

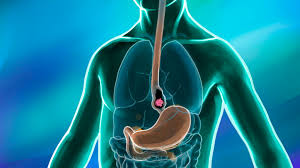
For locally advanced esophageal cancer, chemo isn’t just given before surgery. It’s given to make surgery possible. The standard approach for operable esophageal cancer is neoadjuvant chemoradiotherapy first, then esophagectomy 6 to 12 weeks later. Chemo shrinks the tumour, downgrades the stage, clears microscopic spread, and turns an operation that couldn’t be done safely into one that can. The operability question gets reassessed after chemo, not decided before it.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India, “Neoadjuvant chemoradiotherapy before esophagectomy isn’t a delay in treatment. It is the treatment. We’re not waiting to see what happens. We’re actively shrinking the tumour, clearing the margins, improving the chances that the operation will achieve what we need it to achieve. The surgery after chemo is often a better, cleaner operation than surgery without it would have been.”

Chemo before esophageal surgery isn’t a detour. It’s part of the plan.

How Does Chemo Make Esophageal Cancer More Operable?

Several things shift during the neoadjuvant window. All of them matter.

  • Tumour downstaging: Chemoradiotherapy shrinks the primary tumour and reduces lymph node involvement. A T3 tumour invading adjacent tissue can become a T2 confined to the oesophageal wall. That changes the operation entirely.
  • Margin improvement: Smaller tumour means the surgeon has more room to achieve R0 resection, clear margins all round. Positive margins in oesophageal surgery are a major driver of recurrence.
  • Pathological complete response: Around 25 to 30 percent of patients who complete neoadjuvant chemoradiotherapy show no remaining cancer on the surgical specimen. No viable cells at all. Surgery still usually goes ahead to confirm it.
  • Fitness window: The 6 to 12 week gap between finishing chemoradiotherapy and operating also gives the patient time to recover nutritionally and physically. Oesophagectomy is a major operation. Going in stronger improves outcomes.

For patients whose oesophageal cancer requires minimally invasive resection, robotic cancer surgery brings thoracoscopic and laparoscopic precision to oesophagectomy, reducing blood loss and recovery time compared to open surgery.

What Determines Operability After Chemo Is Completed?

Re-staging drives the decision. Several assessments run together.

  • PET-CT re-staging: Shows metabolic activity in the tumour and lymph nodes after chemo. Significant reduction in uptake signals good response. Persistent high uptake raises the question of whether surgery is still the right next step.
  • CT scan reassessment: Measures change in tumour size, local invasion and lymph node status. Compared directly against the pre-chemo staging scans to quantify response.
  • Endoscopy and biopsy: Visual assessment of the oesophagus after chemoradiotherapy, with biopsies to check for residual cancer in the mucosa. Helps the surgeon plan the extent of resection.
  • Patient fitness reassessment: Pulmonary function, nutritional status, weight, performance score all get reviewed before the surgical date is confirmed. Chemo takes a toll. Not everyone bounces back at the same rate.

For patients wanting to understand overall prognosis and what treatment response means for long-term outcomes, our blog on whether esophageal cancer curable covers the honest picture across stages.

Why Choose Dr. Sandeep Nayak for Esophageal Cancer Surgery?

Dr. Sandeep Nayak has spent 24 years in surgical oncology. He holds DNB qualifications in Surgical Oncology and General Surgery, plus a fellowship in Laparoscopic and Robotic Onco Surgery. He performs minimally invasive oesophagectomy using thoracoscopic and laparoscopic approaches, coordinates the neoadjuvant chemoradiotherapy plan with medical and radiation oncology, and re-stages every patient before confirming the surgical date. Every oesophageal cancer case goes through tumour board review before treatment begins.

That end-to-end coordination from neoadjuvant planning through to surgical recovery is what gives oesophageal cancer patients the best chance at an R0 resection and the strongest recovery from one of oncology’s most demanding operations. Call +91 8104310753 to book your consultation.

Frequently Asked Questions

Is esophageal cancer operable after chemo?

Yes, neoadjuvant chemo is specifically given to make esophagectomy safer.

How long after chemo is esophageal surgery done?

Usually 6 to 12 weeks after completing chemoradiotherapy.

What if cancer disappears completely after chemo?

Surgery is still usually recommended as residual cells may remain.

Who assesses operability after chemo?

PET-CT, CT scan, endoscopy and the multidisciplinary tumour board together.

Disclaimer: This blog is for informational purposes only and is not a substitute for professional medical advice.
 When Is Colostomy Bag Avoidable in Colon Surgery?

 When Is Colostomy Bag Avoidable in Colon Surgery?

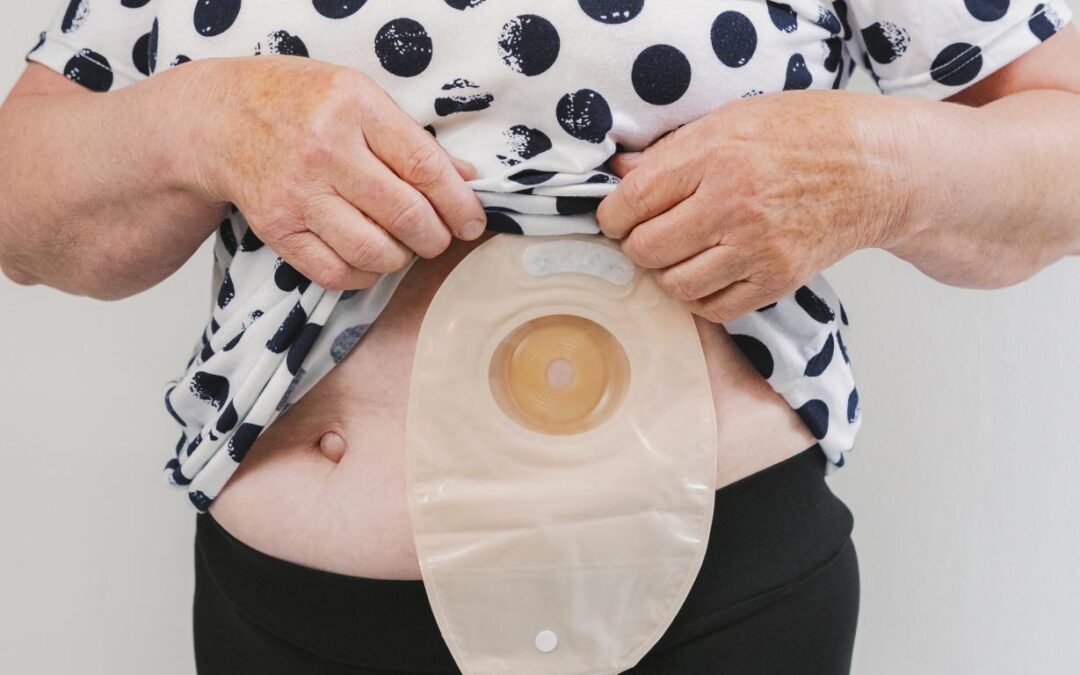
Most planned colon cancer surgeries don’t result in a permanent colostomy bag. For right hemicolectomy, left hemicolectomy and sigmoid colectomy in elective settings, the surgeon removes the diseased segment and rejoins the two ends directly. That’s called primary anastomosis and it avoids a bag entirely. Emergency situations change the picture. Perforation, obstruction, gross contamination or poor bowel preparation all raise the risk that a safe join isn’t possible and a temporary stoma becomes the safer option.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India, “For colon cancer, the bag question worries patients far more than the data warrants. Most elective right and left colon resections end with a direct join and no stoma. The cases where we create a stoma are the emergency presentations, the perforations, the unprepared bowels. When a patient comes in electively, staged properly, bowel prepared, that bag conversation usually doesn’t happen.”

For most elective colon surgeries, no bag is the expected outcome, not the exception.

When Can a Colostomy Bag Be Avoided in Colon Surgery?

Elective, prepared and uncomplicated. Those three conditions make avoidance realistic.

  • Right hemicolectomy: Removes the right colon for cancers in the cecum, ascending colon or hepatic flexure. Small bowel joins to the remaining colon directly. No stoma in the vast majority of planned cases.
  • Left hemicolectomy and sigmoid resection: Removes the left colon or sigmoid segment. Both ends of the remaining colon are joined. Stoma avoidable in elective settings with adequate bowel preparation and no gross contamination.
  • Minimally invasive approach: Robotic and laparoscopic colon surgery reduces tissue trauma, blood loss and anastomosis tension. Better visualisation means a more precise join and fewer reasons to divert.
  • Good patient selection: Well nourished, non-emergency patients with no sepsis and no prior pelvic radiation are the best candidates for primary anastomosis. These patients consistently avoid a bag.

For patients choosing minimally invasive colon surgery to reduce stoma risk, robotic cancer surgery offers the precision and tissue handling that supports safe anastomosis in even complex colonic resections.

When Is a Colostomy Bag Unavoidable in Colon Surgery?

Emergency and complicated cases shift the calculation sharply.

  • Emergency surgery: Obstruction or perforation presenting as emergency colon surgery. The bowel is unprepared, often contaminated, and the anastomosis failure risk is too high to join safely. A Hartmann’s procedure, removing the diseased segment and creating a temporary end colostomy, is the safer call.
  • Perforation with contamination: Free faecal contamination in the abdomen raises infection risk to a level where a new bowel join can’t be trusted to heal. Stoma protects the patient’s life. Reversal comes later once things are clean.
  • Extensive or multifocal disease: Very advanced local disease involving adjacent organs or requiring wide resection may not leave enough bowel length for a safe tension-free join.
  • Defunctioning loop: Sometimes the bowel join is technically done but the surgeon adds a temporary upstream loop ileostomy to divert stool while the anastomosis heals. Not a permanent bag. Reversed in 8 to 12 weeks.

For patients with rectal cancer where the colostomy question is even more loaded because of tumour proximity to the sphincter, our blog on rectal cancer colostomy walks through that specific decision in detail.

Why Choose Dr. Sandeep Nayak for Colon Surgery?

Dr. Sandeep Nayak has spent 24 years in surgical oncology. He holds DNB qualifications in Surgical Oncology and General Surgery, plus a fellowship in Laparoscopic and Robotic Onco Surgery. He performs robotic and laparoscopic colon resections with primary anastomosis as the standard goal in elective cases, and discusses the stoma question honestly with every patient before they go into theatre. Every colon cancer case is reviewed by the tumour board before the surgical plan is finalised.

That transparency before surgery, not just after, is what lets patients make genuinely informed decisions about their care. Getting to theatre knowing the stoma plan and the reversal plan if needed is a completely different experience from finding out in recovery. Call +91 8104310753 to book your consultation.

Frequently Asked Questions

When is a colostomy bag avoidable in colon surgery?

Most elective colon cancer surgeries avoid a bag with primary anastomosis.

When is a colostomy bag unavoidable?

Emergency surgery, perforation, extensive disease or poor bowel preparation.

Is a temporary colostomy bag the same as permanent?

No, temporary bags are reversed in a second operation weeks later.

Does robotic surgery reduce colostomy risk?

Yes, precision dissection improves anastomosis success and lowers stoma rates.

Disclaimer: This blog is for informational purposes only and is not a substitute for professional medical advice.
 Is Prostate Cancer Surgery Always Necessary?

 Is Prostate Cancer Surgery Always Necessary?

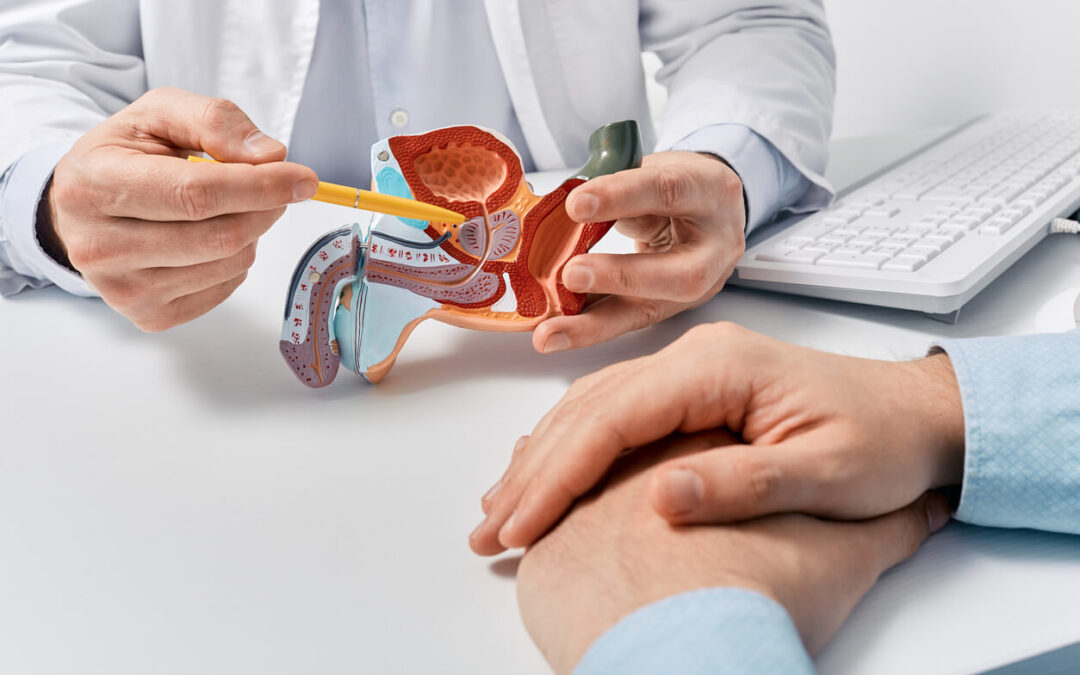
Prostate cancer surgery is not always necessary. Many prostate cancers are slow growing, low grade, and confined to the gland, and for these, active surveillance is a clinically accepted approach that avoids surgery entirely. Surgery becomes the right call when the cancer is localised, the patient is fit, and the goal is cure rather than long-term control. The decision is never automatic. It depends on PSA levels, Gleason score, staging, age and patient preference.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India, “Prostate cancer is one of the few cancers where doing nothing immediately is sometimes the most evidence-based choice. Many men are diagnosed with low-risk prostate cancer and live their entire lives without it becoming a problem. The surgical decision has to weigh the realistic risk from the cancer against the real side effects of the operation, and that’s a conversation the tumour board needs to have with each patient individually.”

Not every prostate cancer diagnosis leads to surgery. Understanding the options changes the conversation.

When Is Surgery Recommended for Prostate Cancer?

Surgery suits specific patients in specific situations. Not every case.

  • Localised disease: Cancer confined within the prostate capsule with no spread to lymph nodes or beyond. This is where radical prostatectomy has its strongest evidence base and curative intent.
  • Younger, fit patients: Surgery is more suitable for men under 70 in good health who can tolerate general anaesthesia and recovery. Older men with significant comorbidities often do better with radiation or surveillance.
  • Intermediate to high risk: Gleason score 7 or above, PSA between 10 and 20, or clinical stage T2. These features suggest the cancer is unlikely to stay slow and controlled without definitive treatment.
  • Patient preference for removal: Some patients want the prostate out. Psychologically, removing the organ provides certainty that radiation or surveillance doesn’t. That’s a valid input into the decision.

For patients who choose surgery, robotic cancer surgery brings nerve-sparing precision that improves continence and erectile function recovery compared to open prostatectomy.

What Are the Alternatives to Surgery?

Three strong non-surgical options exist. Each has its own place.

  • Active surveillance: Regular PSA testing, repeat biopsies and MRI monitoring without treatment. Standard for very low or low-risk disease. The cancer is watched, not ignored. Treatment begins only if it progresses.
  • Radiation therapy: External beam radiation or brachytherapy. Equivalent survival outcomes to surgery in localised prostate cancer across multiple studies. Different side effect profile, not a lesser option.
  • Hormone therapy: Used for advanced or metastatic disease, or alongside radiation for high-risk cases. Lowers testosterone that drives cancer growth. Not curative, but controls disease for years.
  • Focal therapy: Emerging option for selected patients. Treats only the tumour within the gland using HIFU or cryotherapy. Preserves more function than full prostatectomy. Evidence is still growing.

For patients who do have surgery and want to understand what radiation after prostatectomy involves, our blog on prostate cancer radiation after robotic surgery walks through when it’s needed and why.

Why Choose Dr. Sandeep Nayak for Prostate Cancer Treatment?

Dr. Sandeep Nayak has spent 24 years in surgical oncology. He holds DNB qualifications in Surgical Oncology and General Surgery, plus a fellowship in Laparoscopic and Robotic Onco Surgery. He performs nerve-sparing robotic radical prostatectomy for patients who need surgery, while actively supporting active surveillance for those who don’t. Every prostate cancer case is presented to the tumour board before any recommendation is made. That means no patient goes into surgery, surveillance or radiation without a collective clinical assessment behind the decision.

That approach matters in prostate cancer more than almost any other. The difference between overtreatment and undertreatment in this disease is real, and getting the recommendation right from the start saves patients from side effects they didn’t need and from delays they couldn’t afford. Call +91 8104310753 to book your consultation.

Frequently Asked Questions

Is surgery always needed for prostate cancer?

No, low risk prostate cancers often need surveillance not surgery.

What is active surveillance for prostate cancer?

Close monitoring with PSA tests and biopsies without immediate treatment.

When is prostate cancer surgery recommended?

Localised disease in fit patients where cure rather than control is the goal.

What are alternatives to prostate surgery?

Radiation therapy, hormone therapy, active surveillance and focal therapy.

Disclaimer: This blog is for informational purposes only and is not a substitute for professional medical advice.
 Can You Donate Blood After Cancer Treatment?

 Can You Donate Blood After Cancer Treatment?

Many cancer survivors can donate blood, but not all. The answer splits cleanly by cancer type. Solid tumour survivors of breast, colon, lung, thyroid, and stomach can generally donate 12 months after treatment ends, provided remission is confirmed. Blood cancer survivors cannot. Leukaemia, lymphoma and myeloma permanently disqualify a donor. During active treatment, nobody donates. That window stays closed until the cancer is gone.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India, “Cancer survivors who want to donate blood are making a generous choice, and most solid tumour survivors can do exactly that after the right waiting period. The 12-month gap exists to confirm remission, not to punish the survivor. Blood cancers are a different matter entirely because the disease affects the blood itself, and that’s a permanent exclusion.”

Finished treatment and want to give back? Here’s what you need to know first.

Who Can and Who Cannot Donate Blood After Cancer?

The split comes down to where the cancer originated.

  • Solid tumour survivors: Breast, colon, colorectal, lung, thyroid, stomach, cervical and prostate cancer survivors are generally eligible 12 months after completing treatment with no signs of recurrence. The blood itself wasn’t the problem.
  • Blood cancer survivors: Leukaemia, lymphoma, multiple myeloma. Permanently ineligible. These cancers originate in blood cells and bone marrow, and that changes the donation equation entirely. No waiting period fixes it.
  • Low risk skin cancers: Basal cell and squamous cell carcinoma survivors can donate once the cancer is removed and the wound healed. No 12-month wait needed for these.
  • During treatment: No. Not during chemotherapy. Not during radiation. Not on hormone therapy. Any active cancer treatment closes the donation window completely.

For patients who receive blood products as part of their own cancer treatment, robotic cancer surgery reduces intraoperative blood loss, often lowering the need for transfusions during and after surgery.

Common Questions Cancer Survivors Have About Blood Donation

The fears and the facts, side by side.

  • Can cancer spread through blood donation? No confirmed cases exist worldwide. Studies consistently show solid tumour cells don’t survive transfusion conditions. The 12-month wait is about confirming the donor’s own health, not protecting the recipient from cancer transmission.
  • What if my blood still has chemo drugs? Drug clearance happens well before the 12-month waiting period ends. By the time a survivor is eligible to donate, chemotherapy residues aren’t a concern.
  • Will the blood bank know? Yes. Every donor fills a detailed medical history form. Being honest matters, not just for the recipient’s safety but for the donor’s own health. Donation after recent treatment can strain a recovering body.
  • What if I want to donate but can’t? Encourage family or friends to donate in your name. Register as a bone marrow donor if eligible. Donate to cancer care organisations. Giving back takes more than one form.

For patients curious about why cancer doesn’t spread person to person through blood contact or casual exposure, our blog on whether cancer is a cancer communicable disease addresses this question directly.

Why Choose Dr. Sandeep Nayak for Your Cancer Care?

Dr. Sandeep Nayak has spent 24 years in surgical oncology. He holds DNB qualifications in Surgical Oncology and General Surgery, plus a fellowship in Laparoscopic and Robotic Onco Surgery. He guides cancer survivors through survivorship decisions including what the recovery period means for everyday life choices, working closely with medical oncologists to give patients the clearest possible picture of where they stand.

Every case at MACS Clinic is reviewed by the multidisciplinary tumour board before treatment planning. Call +91 8104310753 to book your consultation.

Frequently Asked Questions

Can cancer survivors donate blood?

Most solid tumour survivors can after 12 months in confirmed remission.

Can blood cancer survivors donate blood?

No, leukaemia, lymphoma and myeloma survivors are permanently ineligible.

Can cancer spread through blood donation?

No reported cases of cancer spreading through blood transfusion exist.

Can you donate blood during cancer treatment?

No, donation is not allowed during active cancer treatment.

Disclaimer: This blog is for informational purposes only and is not a substitute for professional medical advice.

What Is Adjuvant Therapy After Cancer Surgery?

What Is Adjuvant Therapy After Cancer Surgery?

Adjuvant therapy is everything that happens after surgery to stop the cancer coming back. The tumour is out. The margins may be clear. But microscopic cells too small for any scan to catch can still sit in lymph nodes, tissue or circulation. Adjuvant therapy, whether that’s chemo, radiation, hormone therapy or targeted drugs, is what goes after those cells. Surgery removes what the eye can see. Adjuvant therapy deals with what it can’t.

According to Prof. Dr. Sandeep Nayak, Surgical Oncologist in India, “Surgery removes the tumour you can see and the margins around it. But cancer doesn’t always confine itself neatly to what’s visible. Microscopic cells can sit in lymph nodes, surrounding tissue or circulation before surgery even starts. Adjuvant therapy is what we give to deal with that residual risk, and the decision is never one doctor’s call. It goes to the tumour board.”

 Surgery is the start. Adjuvant therapy is what protects the result.

What Types of Adjuvant Therapy Exist After Surgery?

Several options. Different cancers need different combinations.

  • Chemotherapy: Drugs go everywhere. The whole body. That’s the point. Microscopic cells hiding anywhere get targeted, not just at the surgery site. Given in cycles. Usually 4 to 8, depending on cancer type and stage.
  • Radiation: Targeted, not systemic. Hits a defined area, usually the surgical bed or regional lymph nodes. Lumpectomy patients almost always need it. Some mastectomy patients too, depending on nodal status and margins.
  • Hormone therapy: For cancers driven by oestrogen or testosterone. Breast and prostate mainly. Tamoxifen. Aromatase inhibitors. Doesn’t run for months. Runs for 5 to 10 years, because late recurrence is the real risk in these cancers.
  • Targeted therapy and immunotherapy: Specific to cancer biology. HER2 positive breast, certain lung and colorectal subtypes, melanoma. More precise than chemo. Side effect profile is different, often gentler, though not always.

For patients who need a second surgical step as part of their plan, like re-excision before starting adjuvant treatment, robotic cancer surgery keeps recovery fast and gets patients to adjuvant therapy sooner.

Who Needs Adjuvant Therapy and Who Doesn't?

Not everyone. The risk calculation decides.

  • Stage and spread: Positive lymph nodes, close or positive margins, later stage disease all push the calculation toward adjuvant therapy. The higher the recurrence risk, the clearer the benefit.
  • Tumour biology: Grade, hormone receptor status, HER2 status, genomic tests like Oncotype DX for breast cancer. Aggressive biology pushes toward adjuvant. Favourable biology sometimes means patients can skip it safely.
  • Tumour board decides: Not one doctor’s call. Surgical oncologist, medical oncologist, radiation oncologist and pathologist all review the case together. The recommendation comes out of that conversation.
  • Patient factors: Age, fitness, other health conditions, personal preference. Adjuvant therapy always has side effects. That trade off is part of the discussion, not an afterthought.

For a deeper look at how chemotherapy fits into cancer treatment at each stage, our blog on cancer chemotherapy explains the decision framework clearly.

Why Choose Dr. Sandeep Nayak for Your Cancer Care?

Dr. Sandeep Nayak has spent 24 years in surgical oncology. He holds DNB qualifications in Surgical Oncology and General Surgery, plus a fellowship in Laparoscopic and Robotic Onco Surgery. He builds adjuvant therapy into the conversation before surgery starts, not as a surprise afterwards, so patients go into the operation knowing what the full plan looks like.

Every case at MACS Clinic is reviewed by the multidisciplinary tumour board before treatment planning. Call +91 8104310753 to book your consultation.

Frequently Asked Questions

What is adjuvant therapy in cancer?

Treatment given after surgery to destroy residual cancer cells.

Why is adjuvant therapy needed?

Surgery removes visible cancer but microscopic cells can remain undetected.

How long does adjuvant therapy last?

Weeks to years depending on cancer type and the treatment used.

Does everyone need adjuvant therapy?

No, it depends on stage, grade, margins and recurrence risk.

Disclaimer: This blog is for informational purposes only and is not a substitute for professional medical advice.

Call Now Button